This variant was interpreted by pipeline
7.1.0.
The current version is
8.0.0.
Re-running queues a fresh interpretation; the result replaces this page when complete.
Re-runs are not free. Blank = draws on today's public interpretation allowance.
With a code = uses 1 of that code's uses.
ATRX encodes a chromatin-remodeling protein in the SWI/SNF family that regulates gene expression, DNA methylation, and chromosome structure, including the incorporation of histone H3.3 during telomere replication. Germline mutations in ATRX cause an X-linked syndrome characterized by intellectual disability and alpha-thalassemia. In cancer, ATRX acts as a tumor suppressor: its loss promotes an alternative lengthening of telomeres (ALT) pathway, chromosomal instability, and epigenetic remodeling in a variety of tumors, and tumors with ATRX mutations may be more sensitive to agents that target DNA repair.
This variant
Predicted to eliminate ATRX function entirely, this variant is classified Likely Pathogenic, matching the germline loss-of-function mechanism that causes ATR-X syndrome (intellectual disability with alpha-thalassemia). In cancer, the same loss of ATRX function promotes the alternative lengthening of telomeres (ALT) pathway and chromosomal instability, although this germline variant's relevance to tumor risk is not established.
Transcript
NM_000489.5
HGVS · transcript:coding
NM_000489.5:c.4699+2T>C
GRCh38
chrX:77635913 A>G
GRCh37
chrX:76891404 A>G
Likely Pathogenic: one very strong (PVS1) plus one supporting (PM2) criterion maps to Likely Pathogenic, posterior probability 0.988, under the SVI 2020 PM2-downgrade combination rule.
Classification rationale
PVS1PM2Likely Pathogenic
ATRX c.4699+2T>Ccanonical splice
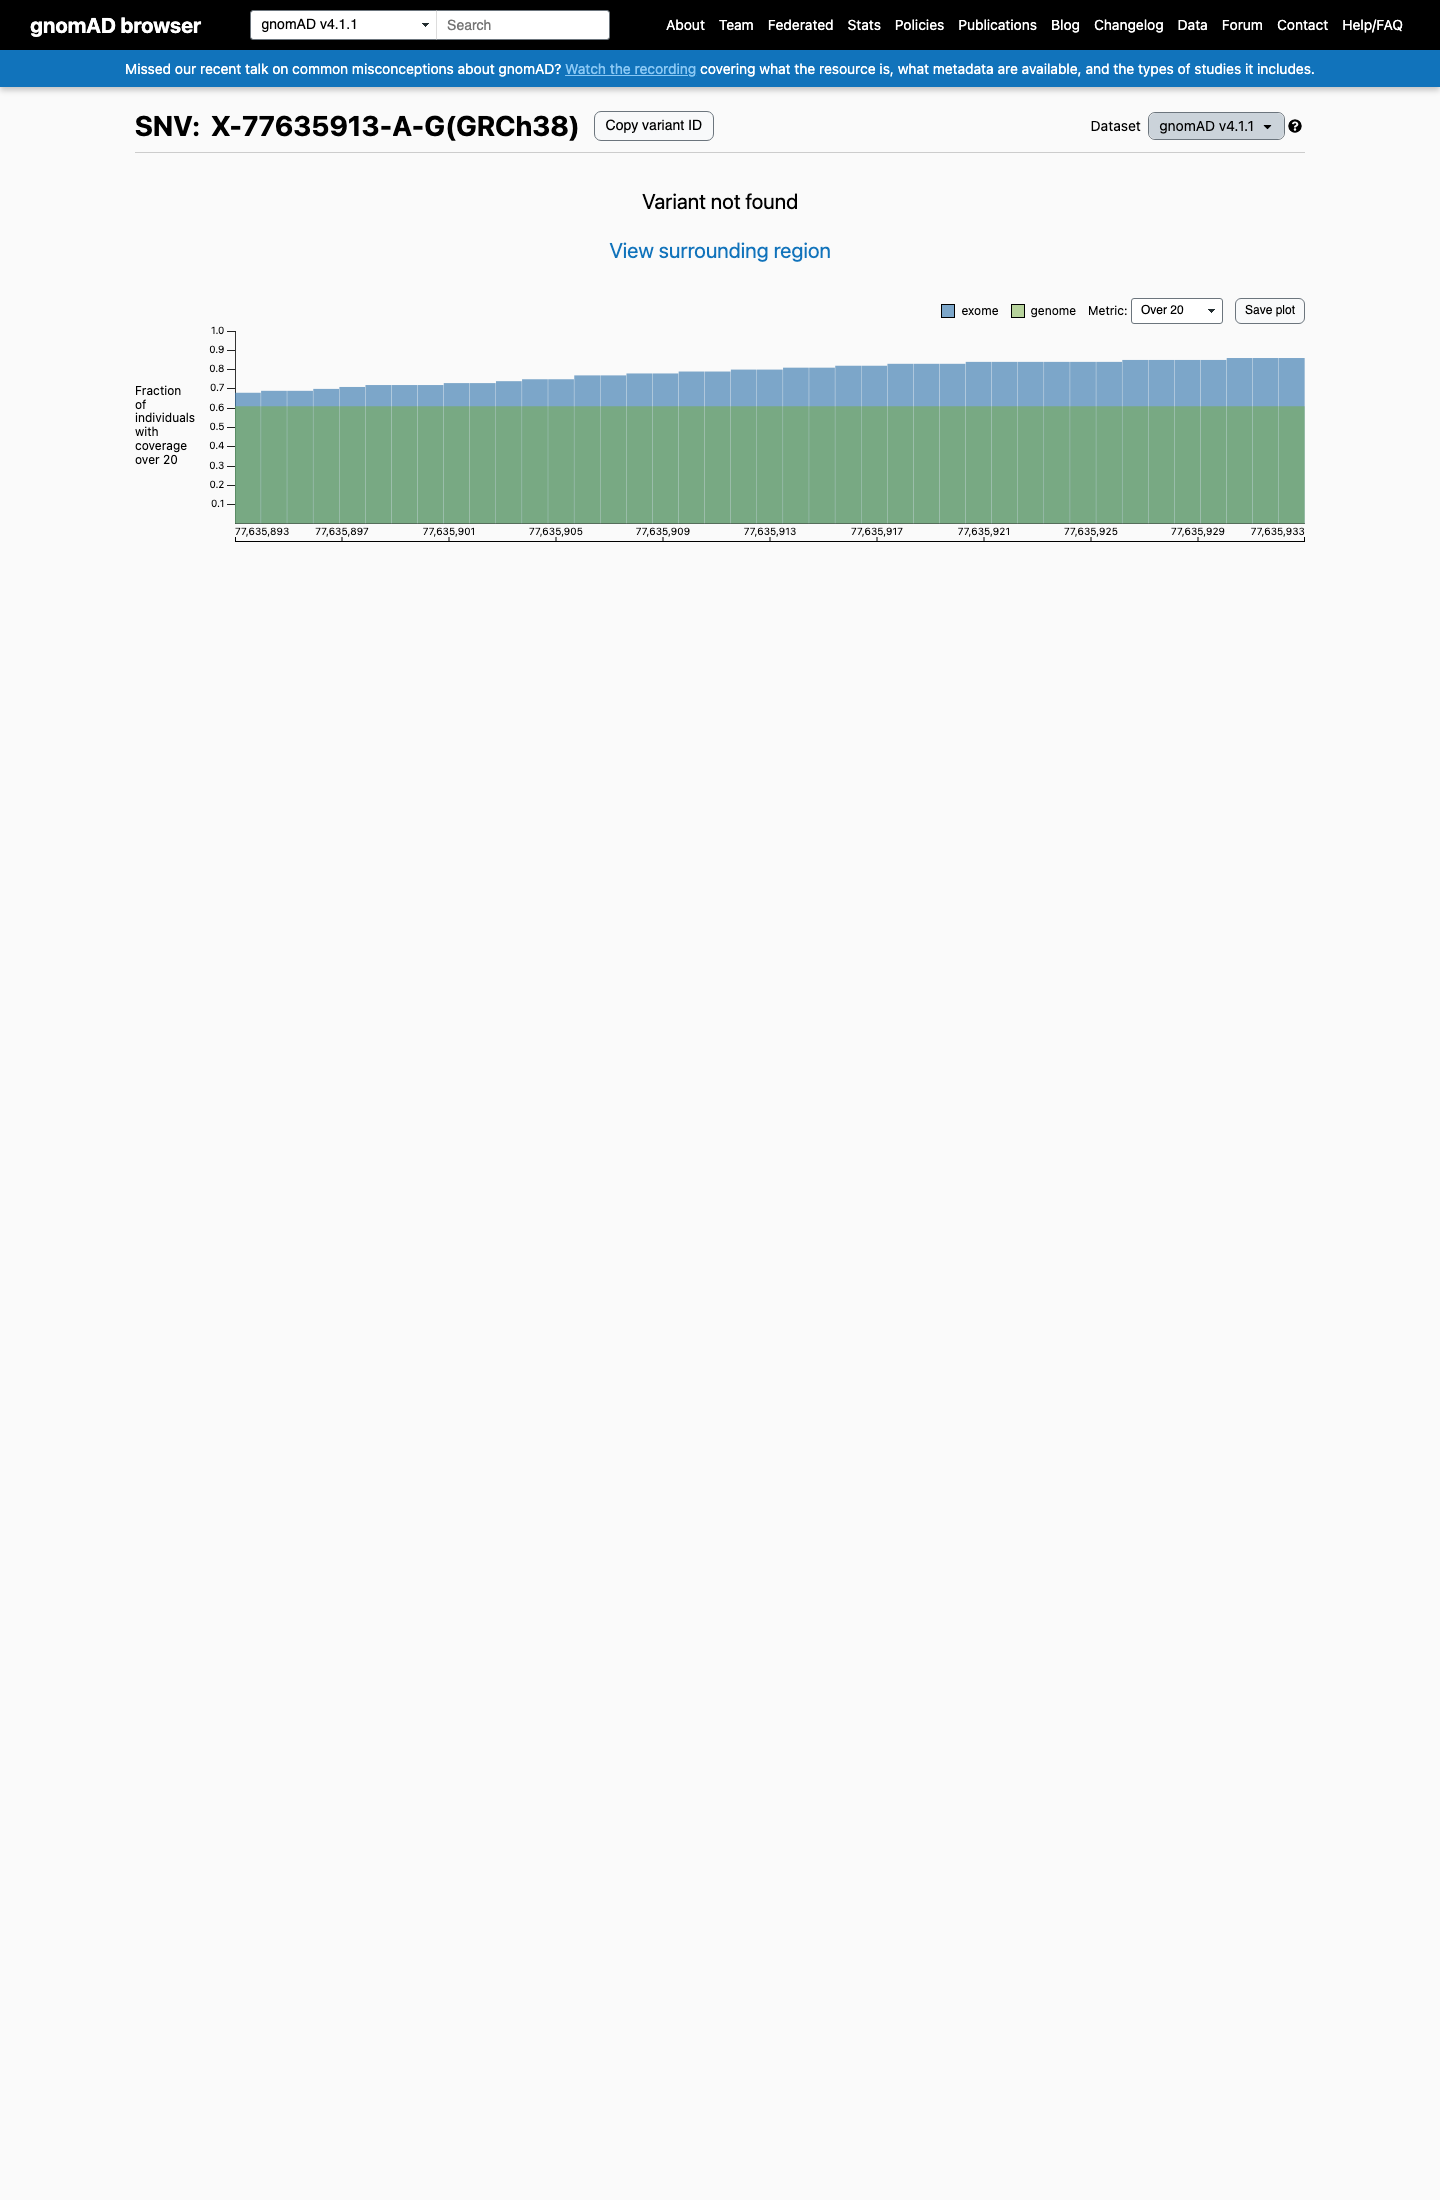
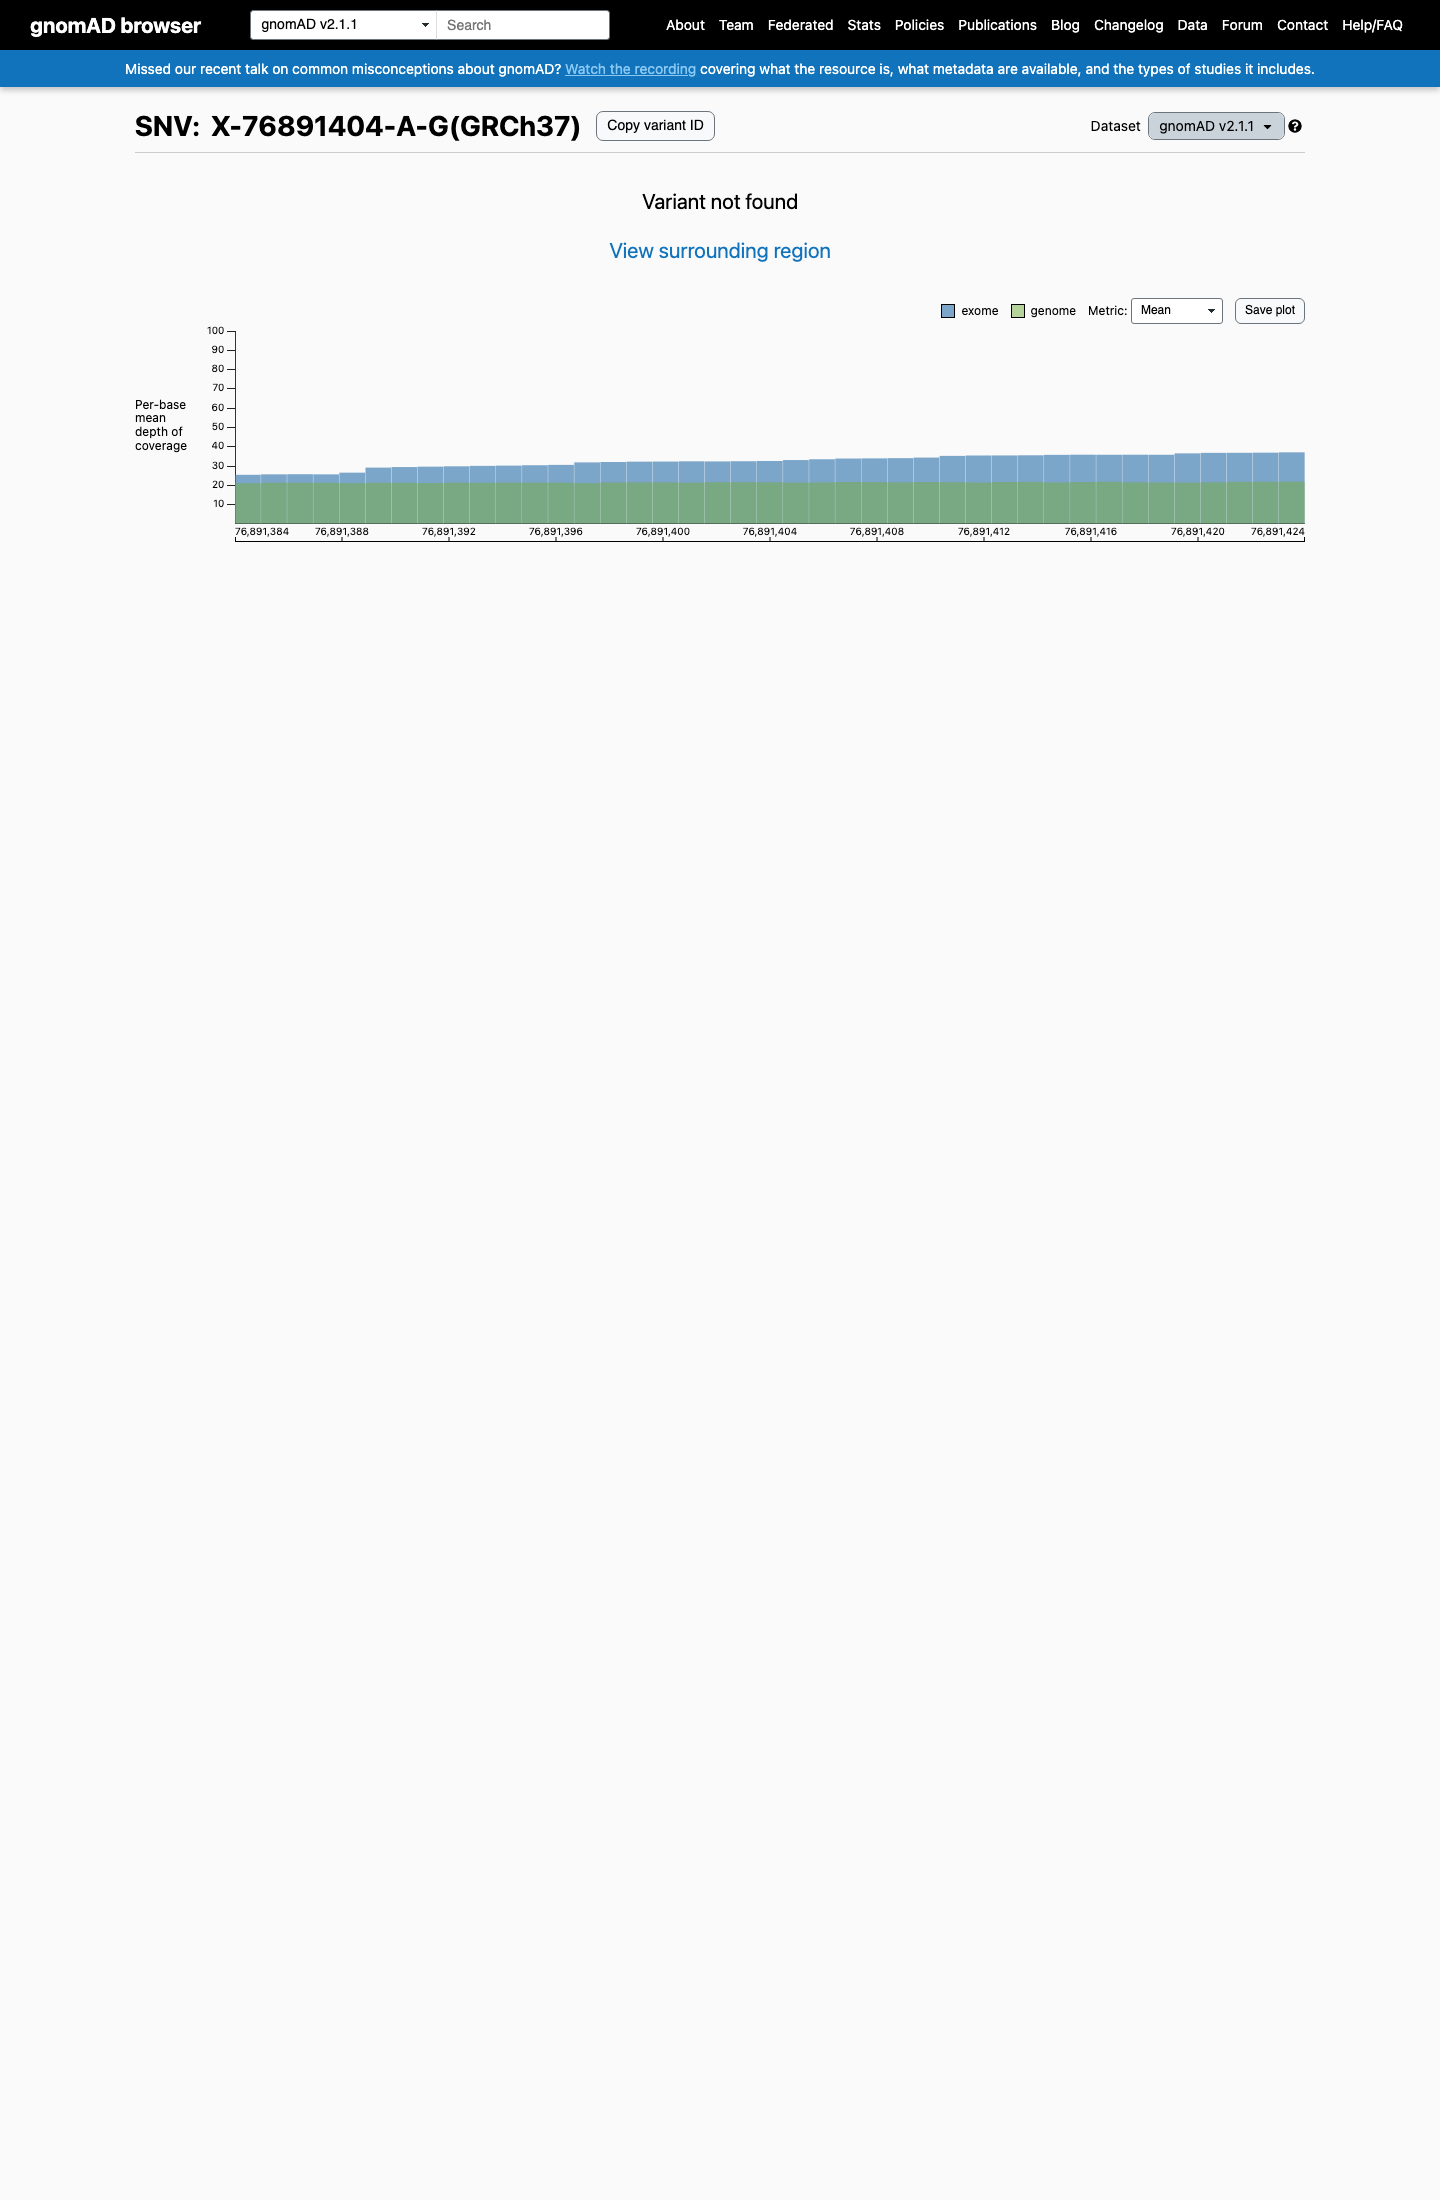
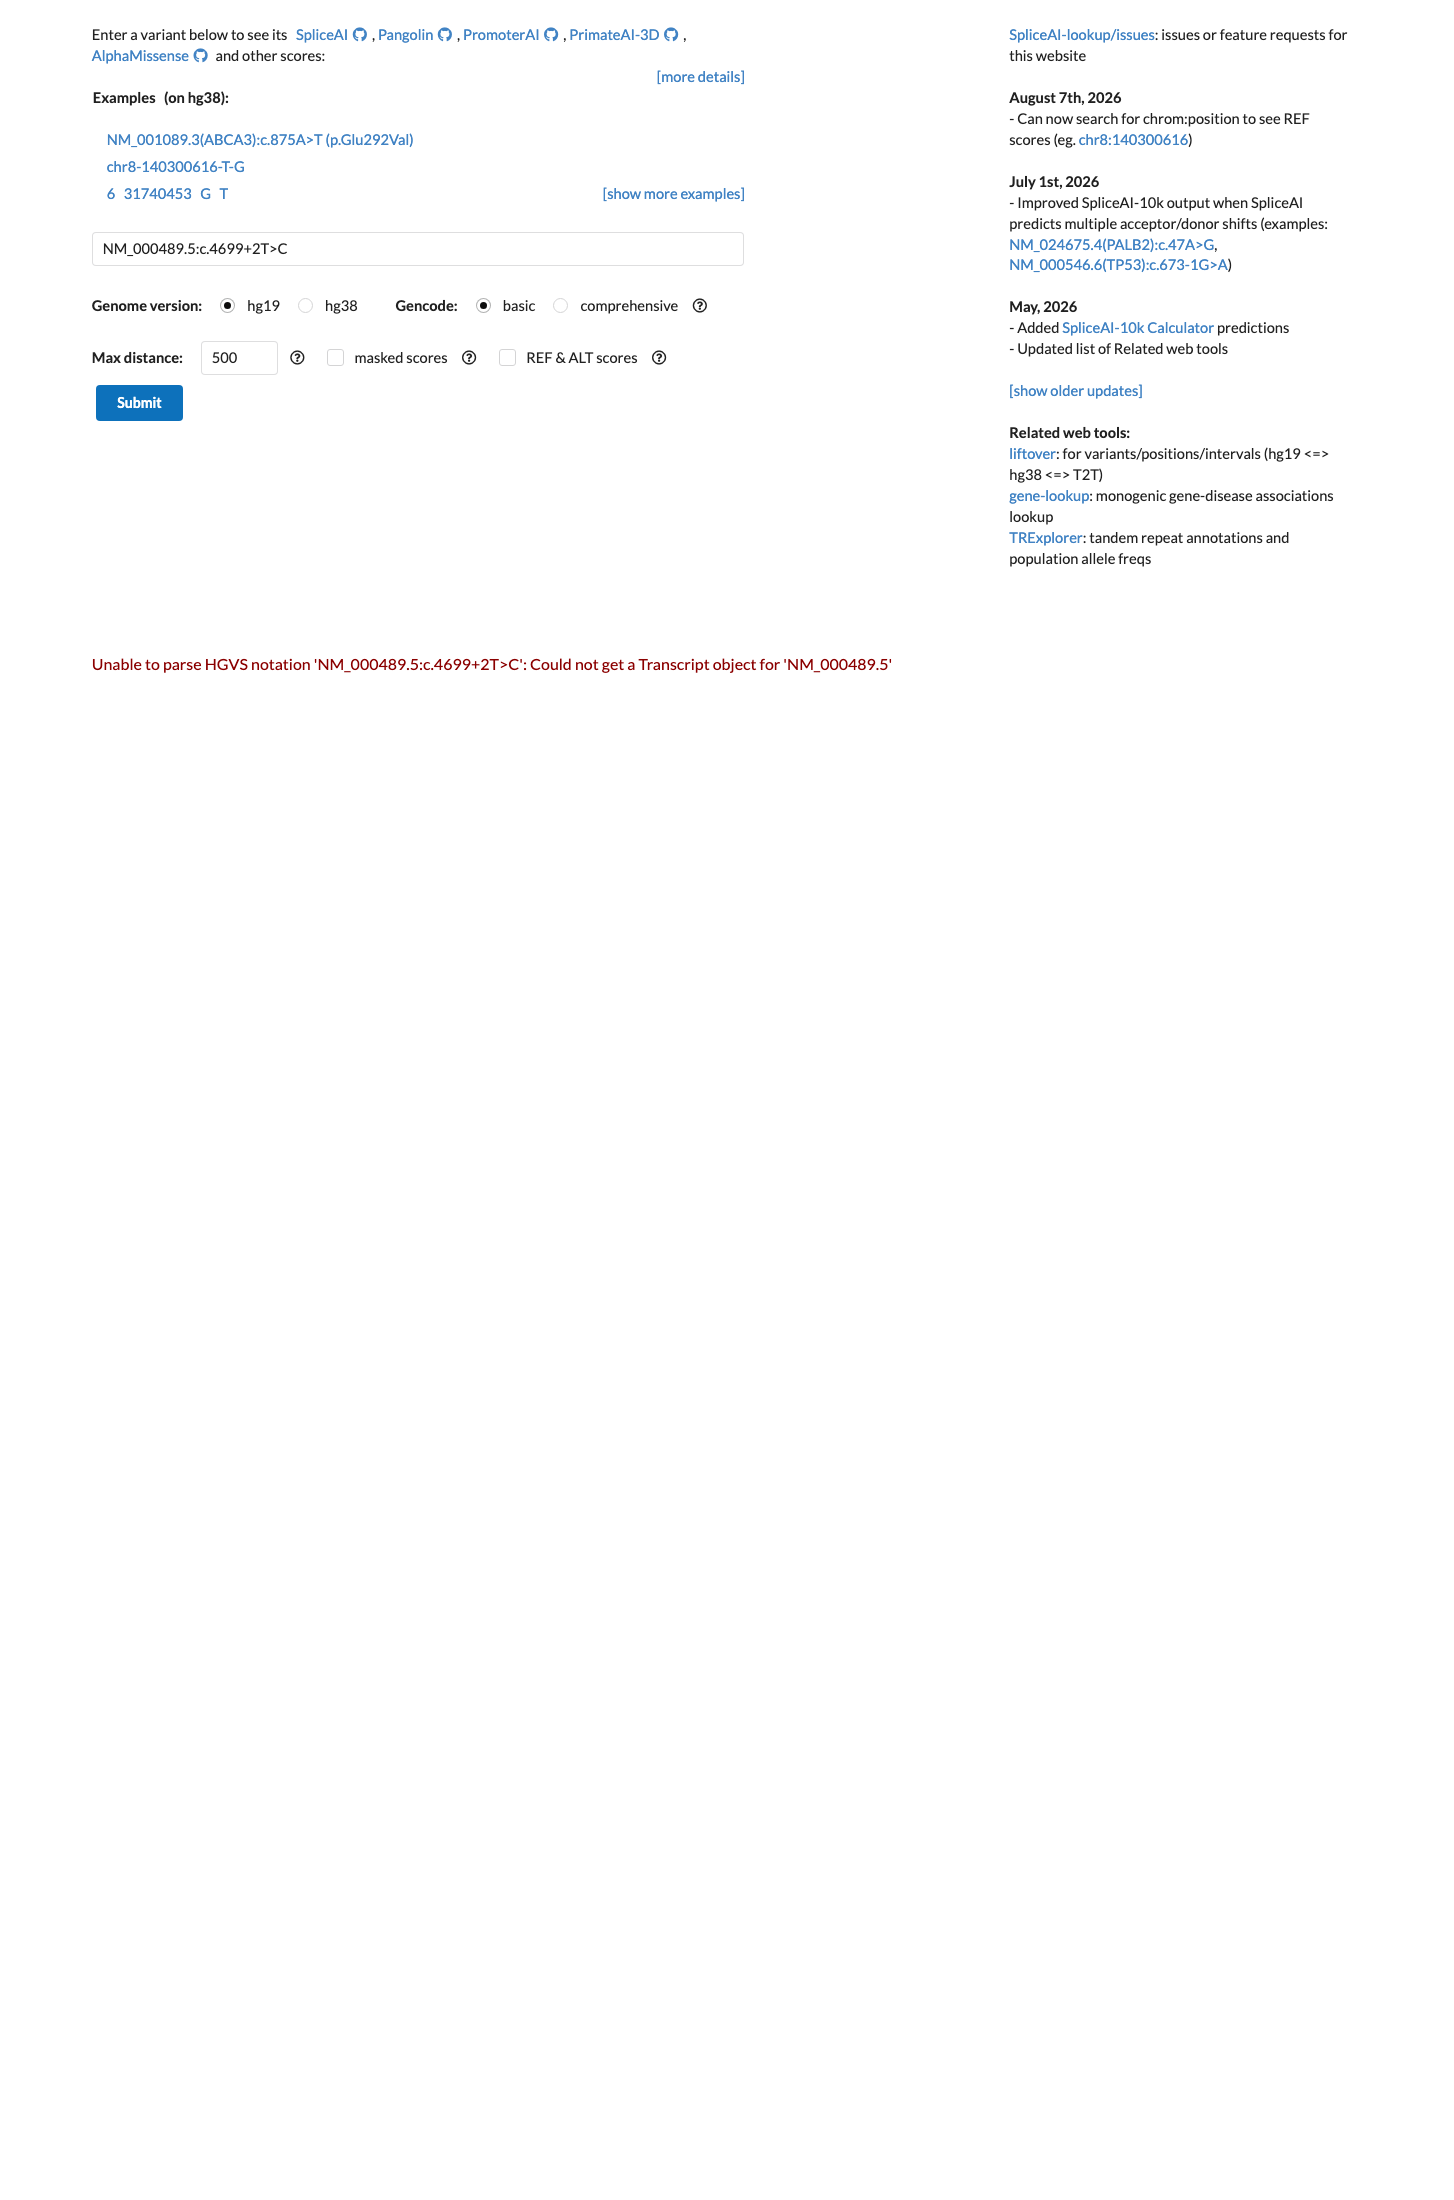
PVS1 (Very Strong): canonical +2 donor splice-site disruption in intron 16 predicted to cause loss of function via nonsense-mediated decay (SpliceAI max delta 0.99). PM2 (Supporting): absent from gnomAD v2.1, v4.1, and gnomAD-Canada (AF 0, below the 0.1% threshold). Combined, PVS1 + PM2 (one very strong plus one supporting) yields Likely Pathogenic under the SVI 2020 PM2-downgrade rule (posterior probability 0.988).
PVS1 + PM2→Likely Pathogenic
LYFE Sciences is an AI system, and it can make mistakes. Criteria
may be applied incorrectly, sources may be misread, and a confident-looking
classification can still be wrong. Double-check every criterion and
its underlying evidence before relying on any call.
Gene diagram
· NM_000489.5 · variants mapped to exon structure
ATRXNM_000489.5
Fetching transcript structure from UCSC…
Exons
—
Transcript span
—
Strand
—
Variants mapped
—
Source
UCSC ncbiRefSeqCurated
All variants in ATRX—click a row to locate it on the plot · use the link column to open its page
Protein
Location
Classification
Link
Applied criteria · 2 applied · 17 assessed
MetEvidence satisfies this criterion.
Not metEvaluated against available evidence; threshold not reached.
Not assessedApplies in principle, but no evidence was found to evaluate it.
N/ADoesn't apply to this variant type.
Applied · 2
Strength Supporting Moderate Strong Very strong
✓
PVS1very strongPathogenic
Met (Very Strong): disruption of the canonical +2 donor splice site of intron 16 is predicted to cause loss of function via nonsense-mediated decay (SpliceAI max delta 0.99).
pvs1_variant_assessment: variant classified canonical_splice, canonical_splice_consensus=true, variant_bucket='canonical_splice', apply_generic_pvs1_framework=true, suggested_default_strength='PVS1'pvs1_gene_context: germline LoF mechanism supported for ATRX (ATR-X syndrome), pvs1_gene_gate='eligible'VariantValidator normalization (prefetch.json): c.4699+2T>C maps to intron 16 ('16i') of the 36-exon NM_000489.5 transcript; RefSeq Select transcript (refseq_select=true)
Assessed · not applied
· 7 not met · 10 not assessed
Pathogenic
PS2Not assessed: no de novo occurrence is documented; no parental testing or parentage confirmation is available, and the variant is absent from ClinVar.
PS3Not assessed: no functional assay evidence (RNA or protein studies) exists for this variant.
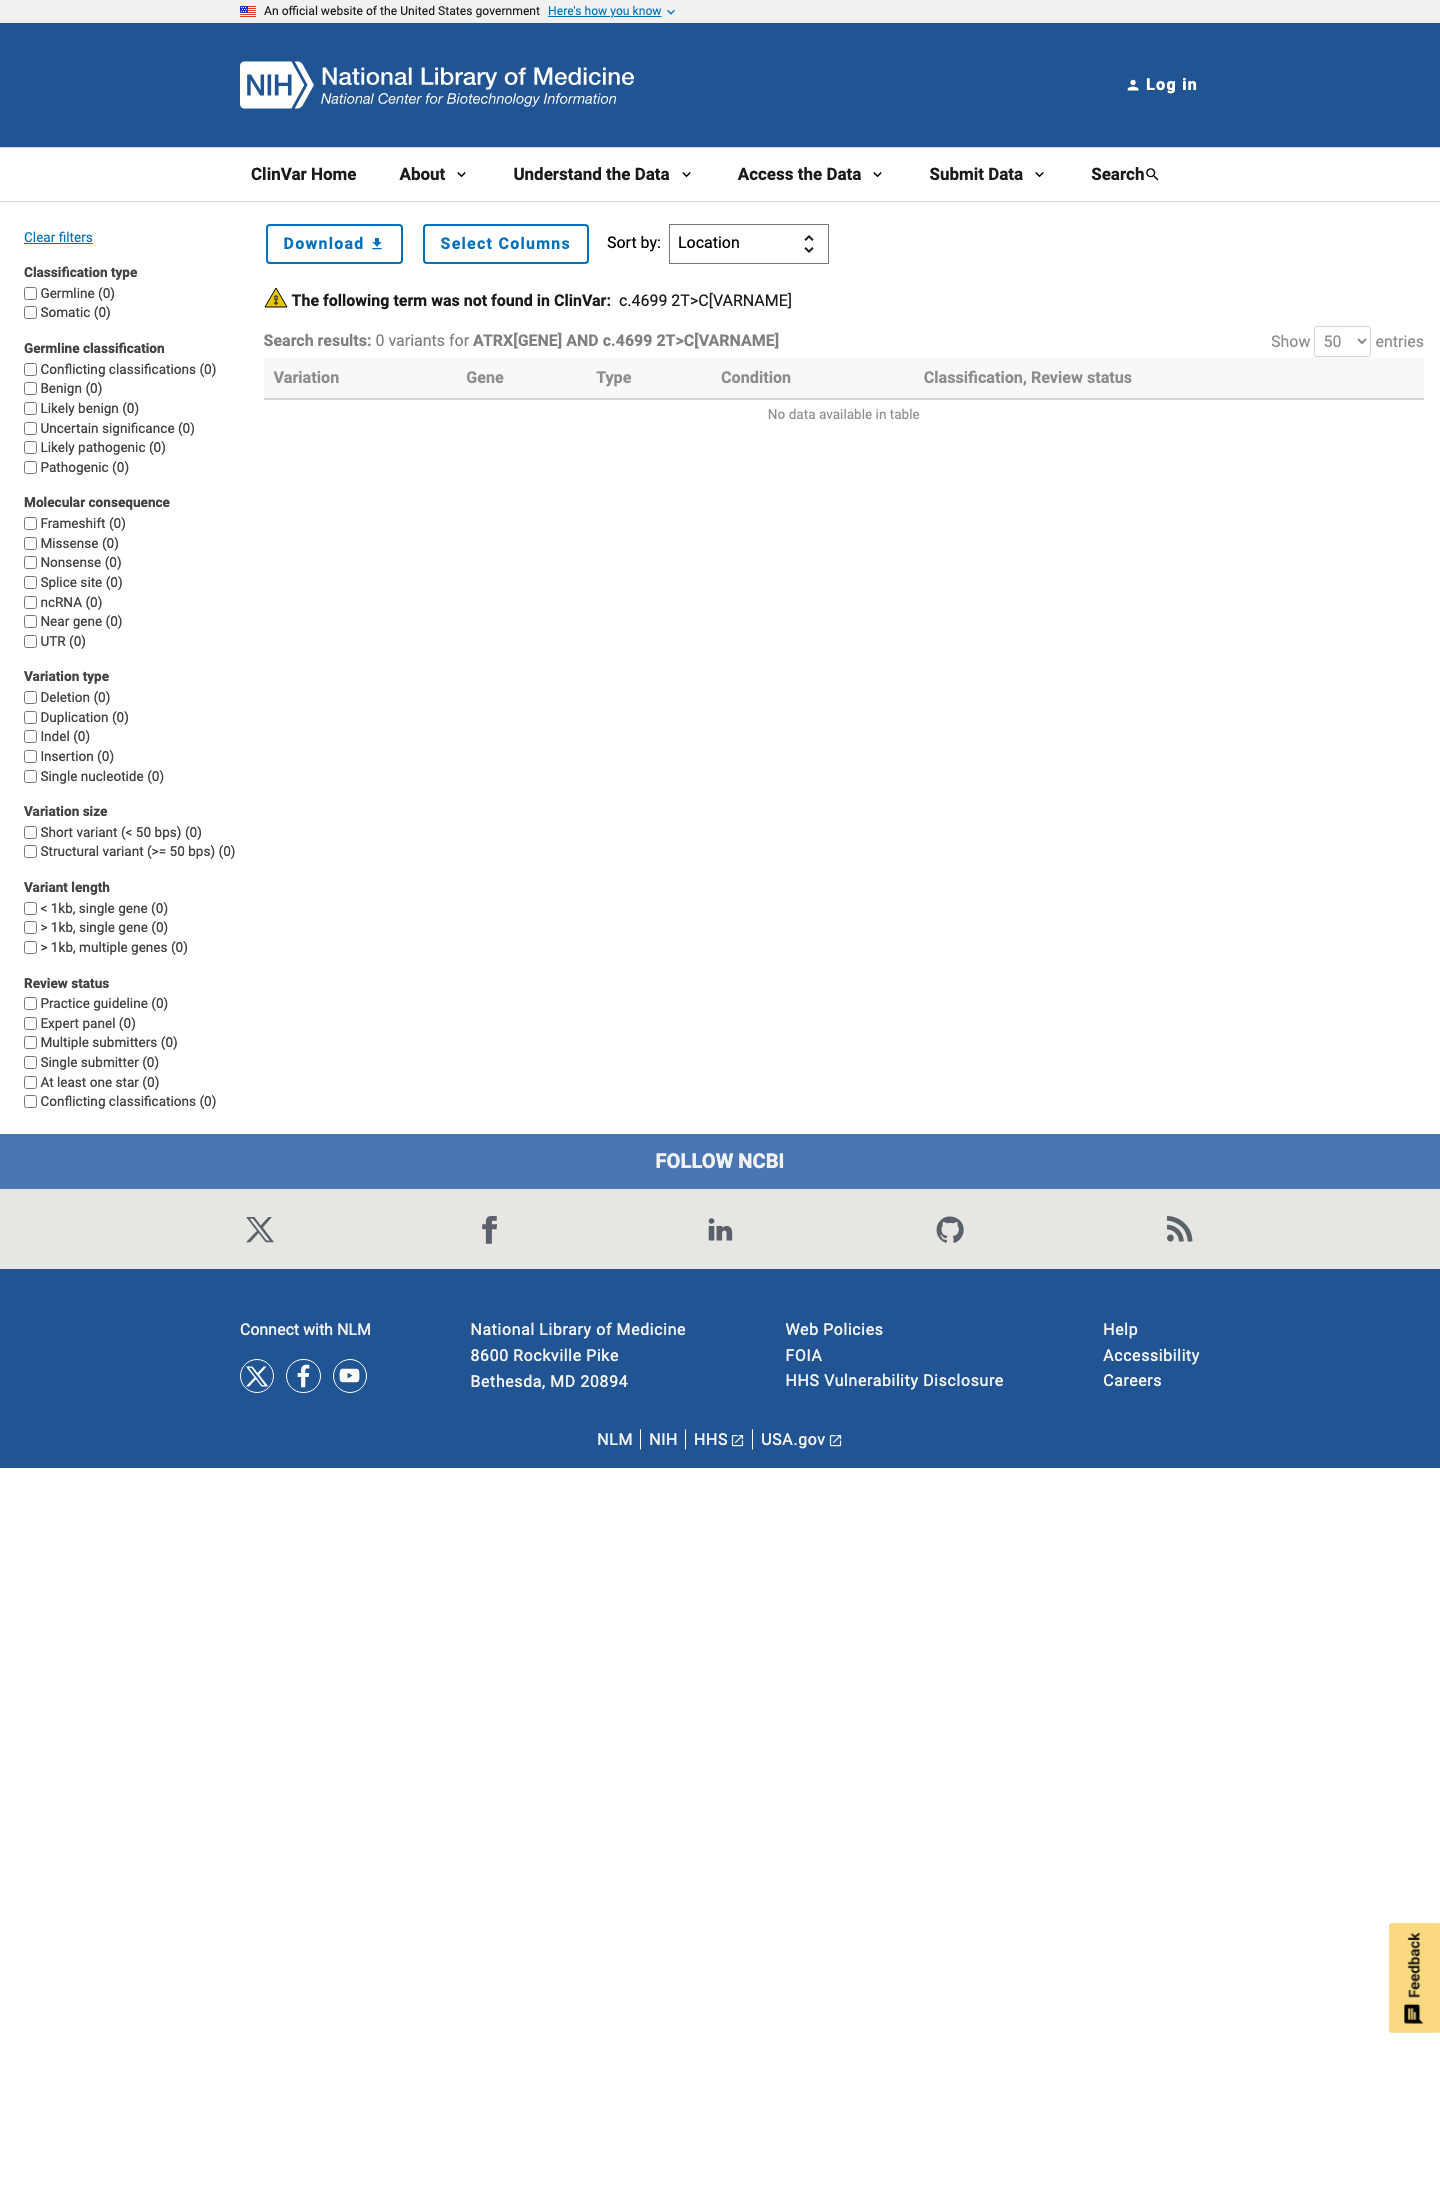
PS4Not assessed: no case-control, cohort, or proband reports of this variant exist in ClinVar or the literature.
PM6Not assessed: no de novo observation of this variant is documented in any individual or source.
PP1Not assessed: no pedigree or family genotyping data exist, so segregation with disease in affected relatives cannot be evaluated.
PP3Not met: SpliceAI predicts near-certain splice disruption (max delta 0.99), but this same prediction already underlies PVS1 and is not double-counted.
PP4Not assessed: no proband phenotype or family-history information is available, so phenotype specificity cannot be evaluated.
PP5Not met: no ClinVar record exists for this variant, so no expert-panel pathogenic classification is available.
Benign
BA1Not met: allele frequency is 0 across gnomAD v2.1, v4.1, and gnomAD-Canada, far below the >1% threshold.
BS1Not met: allele frequency is 0 across gnomAD v2.1, v4.1, and gnomAD-Canada, far below the >0.3% threshold.
BS2Not met: absent from gnomAD v2.1, v4.1, and gnomAD-Canada, with no hemizygous males or homozygous females observed.
BS3Not assessed: no functional studies exist to show a lack of damaging effect, and the available in silico predictions (SpliceAI 0.99) point away from benign.
BS4Not assessed: no family genotyping or non-segregation data exist, so absence of segregation cannot be established.
BP2Not assessed: no phase data exist to establish cis or trans arrangement, and the X-linked inheritance makes the trans prong inapplicable.
BP4Not met: all computational lines predict an impact (SpliceAI max delta 0.99), and no benign-direction prediction exists.
BP5Not assessed: no proband molecular data exist, so an alternative genetic cause of disease cannot be evaluated.
BP6Not met: no ClinVar record exists for this variant, so no expert-panel benign classification is available.