This variant was interpreted by pipeline
7.1.0.
The current version is
8.0.0.
Re-running queues a fresh interpretation; the result replaces this page when complete.
Re-runs are not free. Blank = draws on today's public interpretation allowance.
With a code = uses 1 of that code's uses.
FGFR2 encodes a receptor tyrosine kinase in the fibroblast growth factor receptor family that binds fibroblast growth factors and activates signaling pathways (including PI3K/AKT and MAPK) that promote cell growth, division, and differentiation. Germline mutations in FGFR2 cause several inherited craniosynostosis syndromes — including Apert, Crouzon, Pfeiffer, Jackson-Weiss, Beare-Stevenson, and Saethre-Chotzen syndromes — in which the bones of the skull fuse prematurely. FGFR2 also plays an oncogenic role in cancer: somatic mutations, fusions, and amplifications of the gene have been found in endometrial, gastric, and breast cancers and ameloblastomas, and FGFR inhibitors are used as cancer therapies.
This variant
FGFR2 germline missense variants cause autosomal dominant craniosynostosis syndromes (Apert, Crouzon, Pfeiffer) through activating effects, and p.Glu116Lys falls in the extracellular ligand-binding region where such variants act. Because no established pathogenic record exists and the evidence is conflicting - ultra-rare population frequency but uniformly benign computational predictions - this variant remains a VUS, neither demonstrated to cause FGFR2-related disease nor shown to be benign.
Transcript
NM_000141.4
HGVS · transcript:coding
NM_000141.4:c.346G>A
GRCh38
chr10:121565468 C>T
GRCh37
chr10:123324982 C>T
VUS: only PM2 (supporting, pathogenic) and BP4 (supporting, benign) are met, and this conflicting one-plus-one combination satisfies no ACMG/AMP 2015 rule.
Classification rationale
PM2BP4VUS
FGFR2 c.346G>Amissense
PM2 (Supporting): allele frequency 1.24e-06 (2/1,614,194 alleles) is far below the 0.1% threshold, and the variant is absent from gnomAD v2.1. BP4 (Supporting): REVEL 0.26, BayesDel -0.24425, and SpliceAI max delta 0.09 all predict no impact on the gene product. VUS: one supporting pathogenic criterion (PM2) and one supporting benign criterion (BP4) conflict and satisfy no ACMG/AMP 2015 combination rule.
PM2 + BP4→VUS
LYFE Sciences is an AI system, and it can make mistakes. Criteria
may be applied incorrectly, sources may be misread, and a confident-looking
classification can still be wrong. Double-check every criterion and
its underlying evidence before relying on any call.
Gene diagram
· NM_000141.4 · variants mapped to exon structure
FGFR2NM_000141.4
Fetching transcript structure from UCSC…
Exons
—
Transcript span
—
Strand
—
Variants mapped
—
Source
UCSC ncbiRefSeqCurated
All variants in FGFR2—click a row to locate it on the plot · use the link column to open its page
Protein
Location
Classification
Link
Applied criteria · 2 applied · 19 assessed
MetEvidence satisfies this criterion.
Not metEvaluated against available evidence; threshold not reached.
Not assessedApplies in principle, but no evidence was found to evaluate it.
N/ADoesn't apply to this variant type.
Applied · 2
Strength Supporting Moderate Strong Very strong
✓
PM2supportingPathogenic
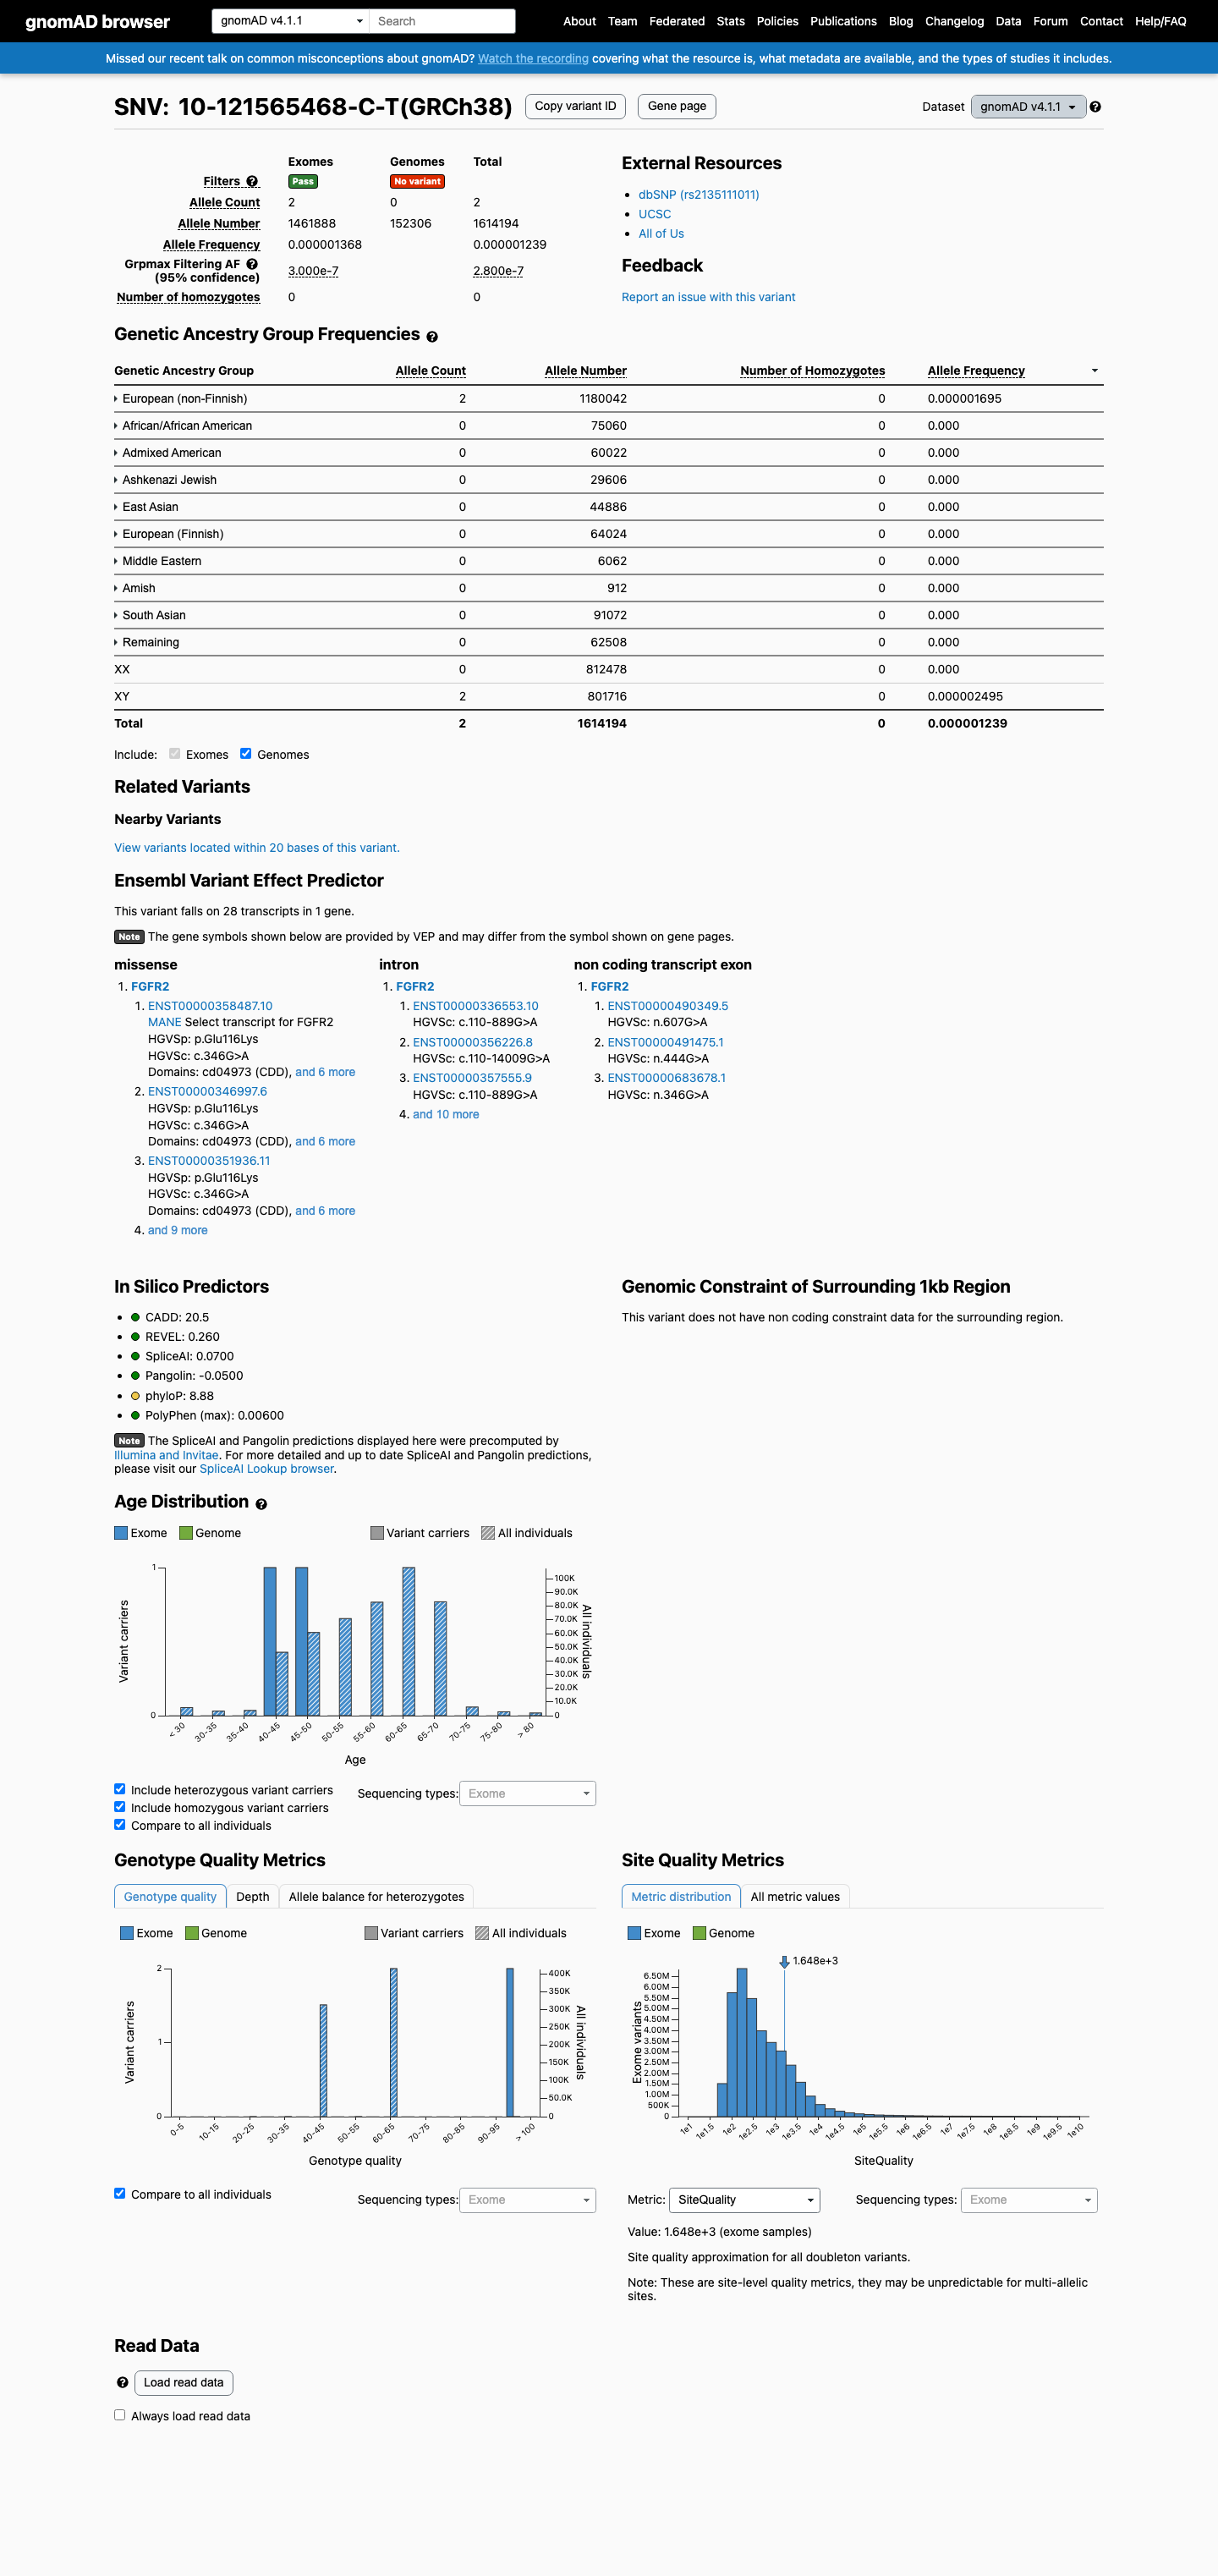
Met (supporting): allele frequency 1.24e-06 (2/1,614,194 alleles, 0.00012%) is far below the 0.1% threshold, and the variant is absent from gnomAD v2.1.
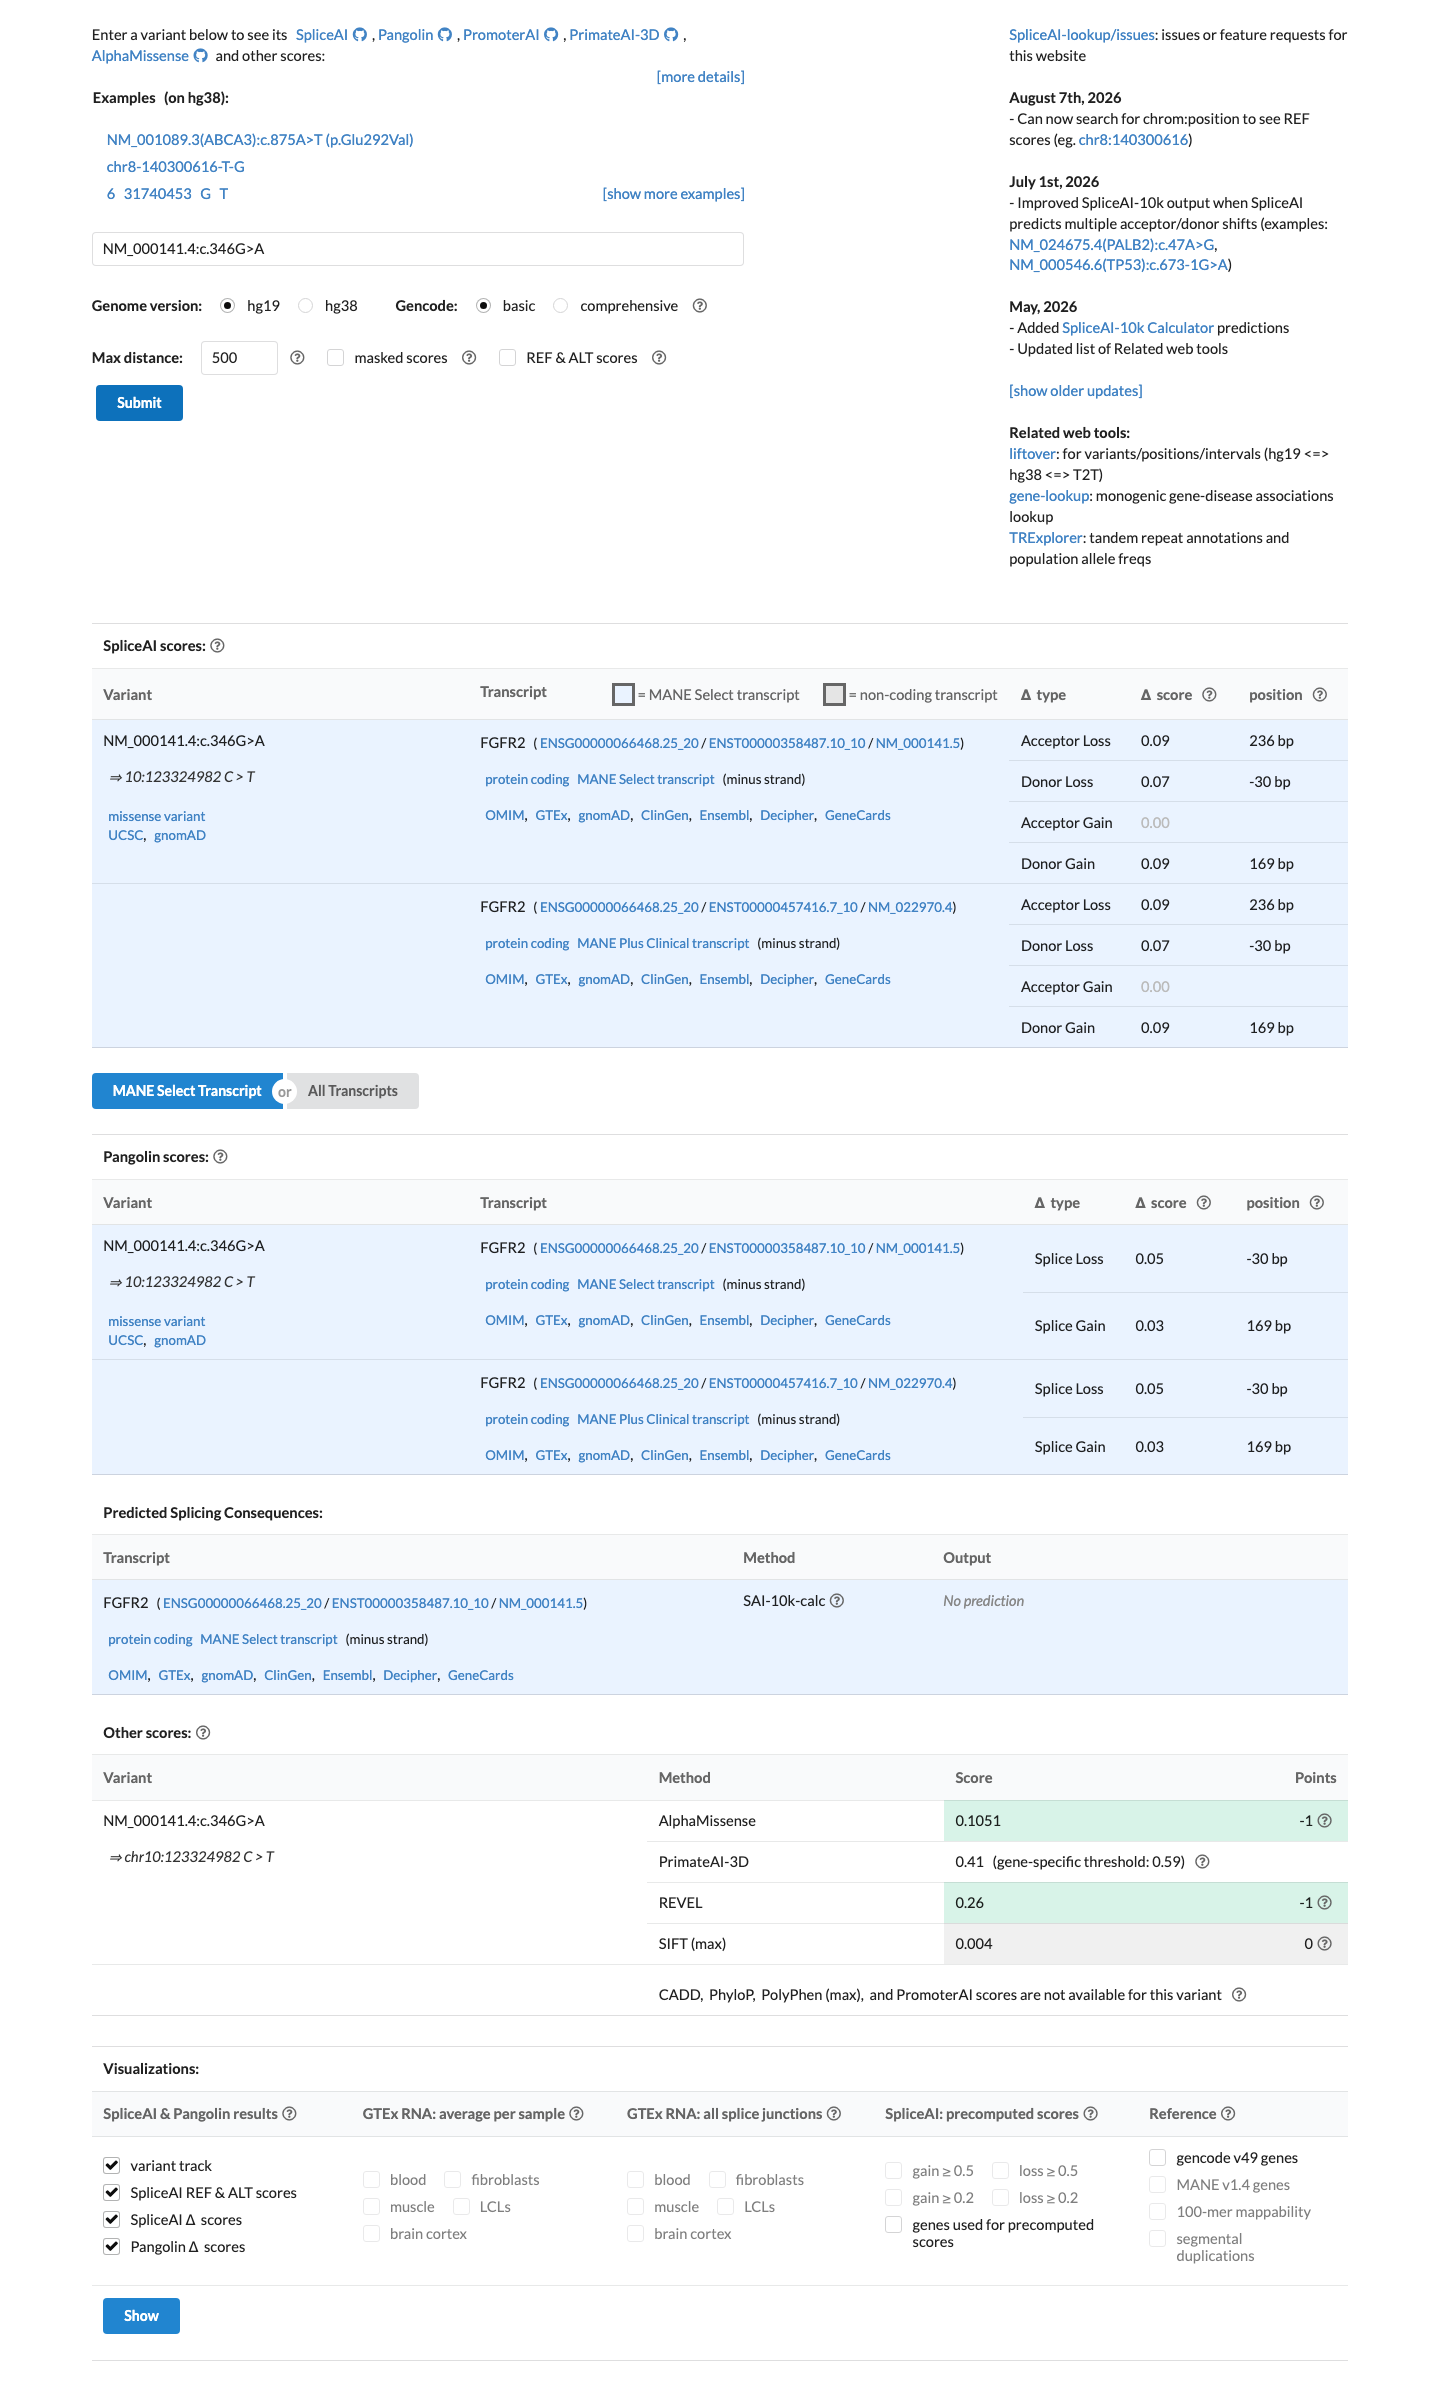
Met (supporting): REVEL 0.26 (benign-supporting band 0.183-0.290), BayesDel -0.24425, and SpliceAI max delta 0.09 (below 0.2) all predict no impact.
REVEL score 0.26 (local lookup, revel-v1.3) - benign-supporting band (0.183-0.290) per ClinGen SVI calibration verified against PMID 36413997; supports no impact on FGFR2BayesDel noAF score -0.24425 (local lookup, BayesDel_170824_noAF_chr10) - benign-supporting tier (-0.36 to -0.18) per pipeline SVCv4 ladder (placeholder calibration); supports no impact, concordant with REVELSpliceAI max delta score 0.09 (DS_AG 0.0, DS_AL 0.09, DS_DG 0.09, DS_DL 0.07; variant_consequence=sequence_variant) - below the 0.2 splice-impact threshold; no predicted splice impact for this exonic missense
Assessed · not applied
· 6 not met · 13 not assessed
Pathogenic
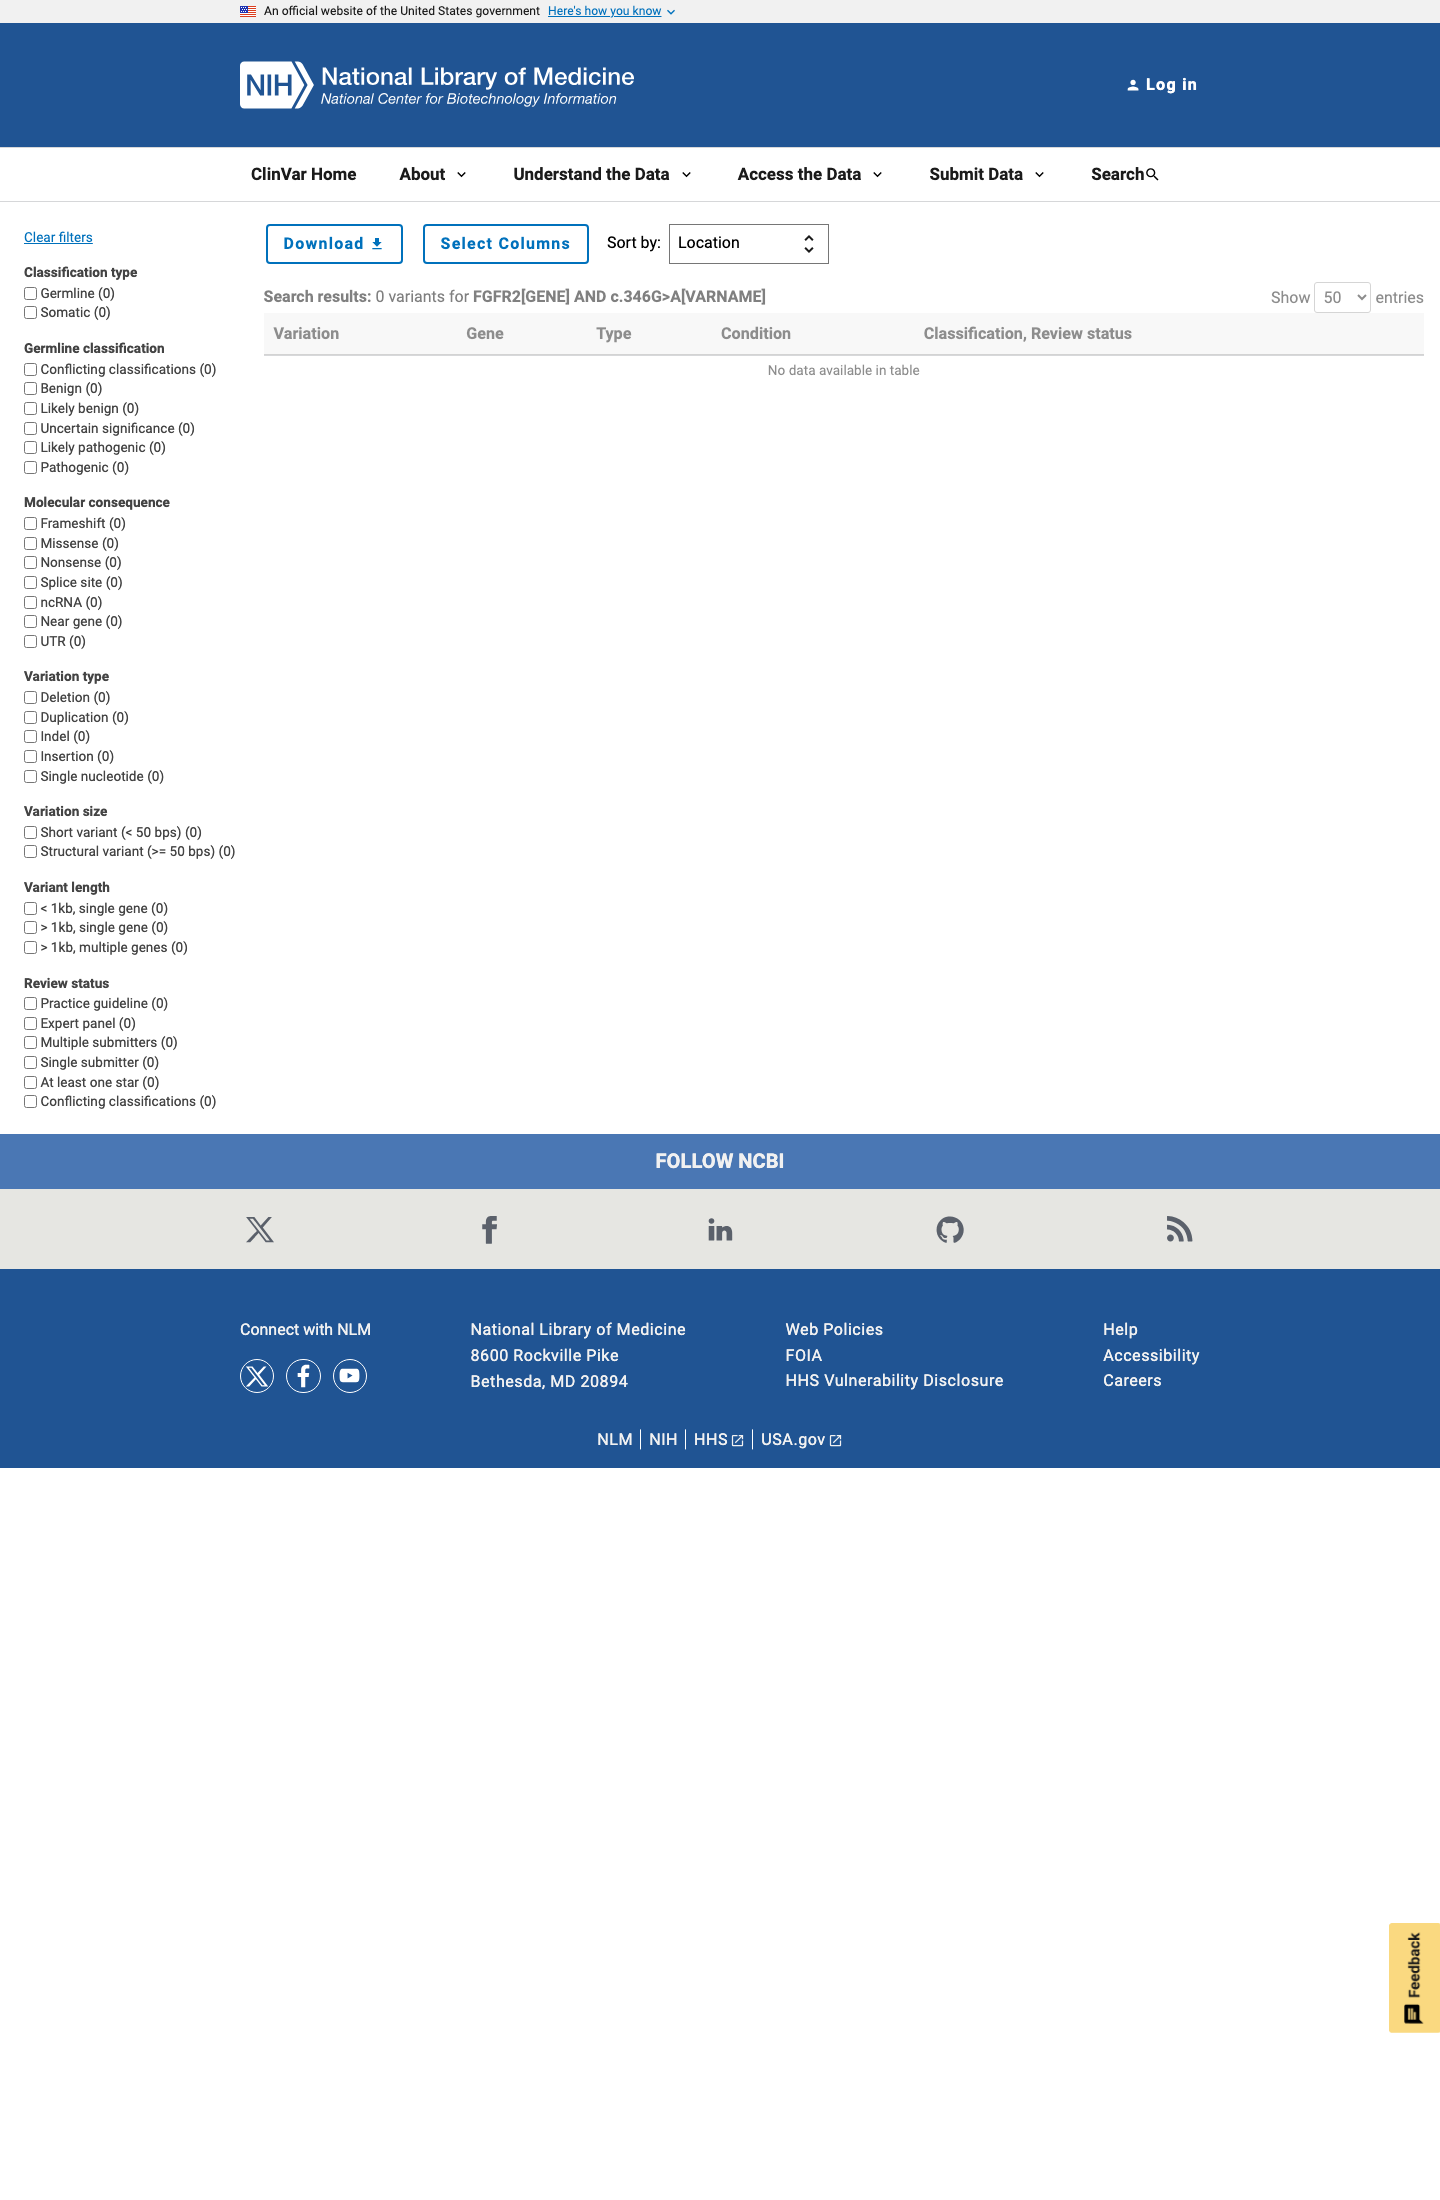
PS1Not assessed: no established pathogenic variant producing p.Glu116Lys is documented in ClinVar or the literature.
PS2Not assessed: no proband genotype, parental testing, or de novo evidence is available for this variant.
PS3Not assessed: no well-established functional study of p.Glu116Lys was available.
PS4Not assessed: no case-control or affected-cohort data exist; the only occurrence is 3 somatic cancer entries in COSMIC.
PM1Not met: p.Glu116 is not a statistically significant mutation hotspot, and no source places it in a critical functional domain.
PM5Not assessed: no different pathogenic missense at p.Glu116 (e.g., p.Glu116Val) is documented in ClinVar or the literature.
PM6Not assessed: no de novo occurrence of c.346G>A is documented in any proband.
PP1Not assessed: no family or pedigree data exist to evaluate co-segregation of c.346G>A with disease.
PP2Not assessed: FGFR2 missense variants are a known disease mechanism, but missense constraint metrics needed for the second prong are unavailable.
PP3Not met: all computational lines are neutral - SpliceAI max delta 0.09 vs 0.2, REVEL 0.26 vs 0.644, BayesDel -0.24425 - so no deleterious effect is predicted.
PP4Not assessed: no proband phenotype or family history is available to evaluate phenotype specificity.
Benign
BA1Not met: highest observed allele frequency is 1.69e-06 (0.00017%), roughly 4 orders of magnitude below the 1% BA1 threshold.
BS1Not met: observed allele frequency 1.24e-06 (0.00012%) is over 3 orders of magnitude below the 0.3% BS1 threshold.
BS2Not met: only 2 heterozygous carriers (0 homozygotes) among 1,614,194 alleles, far short of the multiple healthy-adult observations BS2 requires.
BS3Not assessed: no functional study showing absence of a damaging effect is available; in silico predictions do not qualify.
BS4Not assessed: no family data exist to evaluate non-segregation of the variant.
BP1Not met: FGFR2 disease is caused by activating missense variants, not truncating variants, so BP1's premise does not apply.
BP2Not assessed: no proband observation with phase information relative to a pathogenic FGFR2 variant is available.
BP5Not assessed: no proband molecular workup exists to establish an alternate molecular basis for disease.
N/A · 7PVS1 · PM3 · PM4 · PP5 · BP3 · BP6 · BP7
Research & evidence
Population frequency
gnomAD v4.1
gnomAD v2.1
v4.1
This variant is present in gnomAD v4.1 (AF= 1.23901e-06; MAF= 0.00012%, 2/1614194 alleles, homozygotes = 0) and has highest observed frequency in the European (non-Finnish) population (AF= 1.69485e-06; MAF= 0.00017%, 2/1180042 alleles, homozygotes = 0); grpmax FAF= 2.8e-07.
v2.1
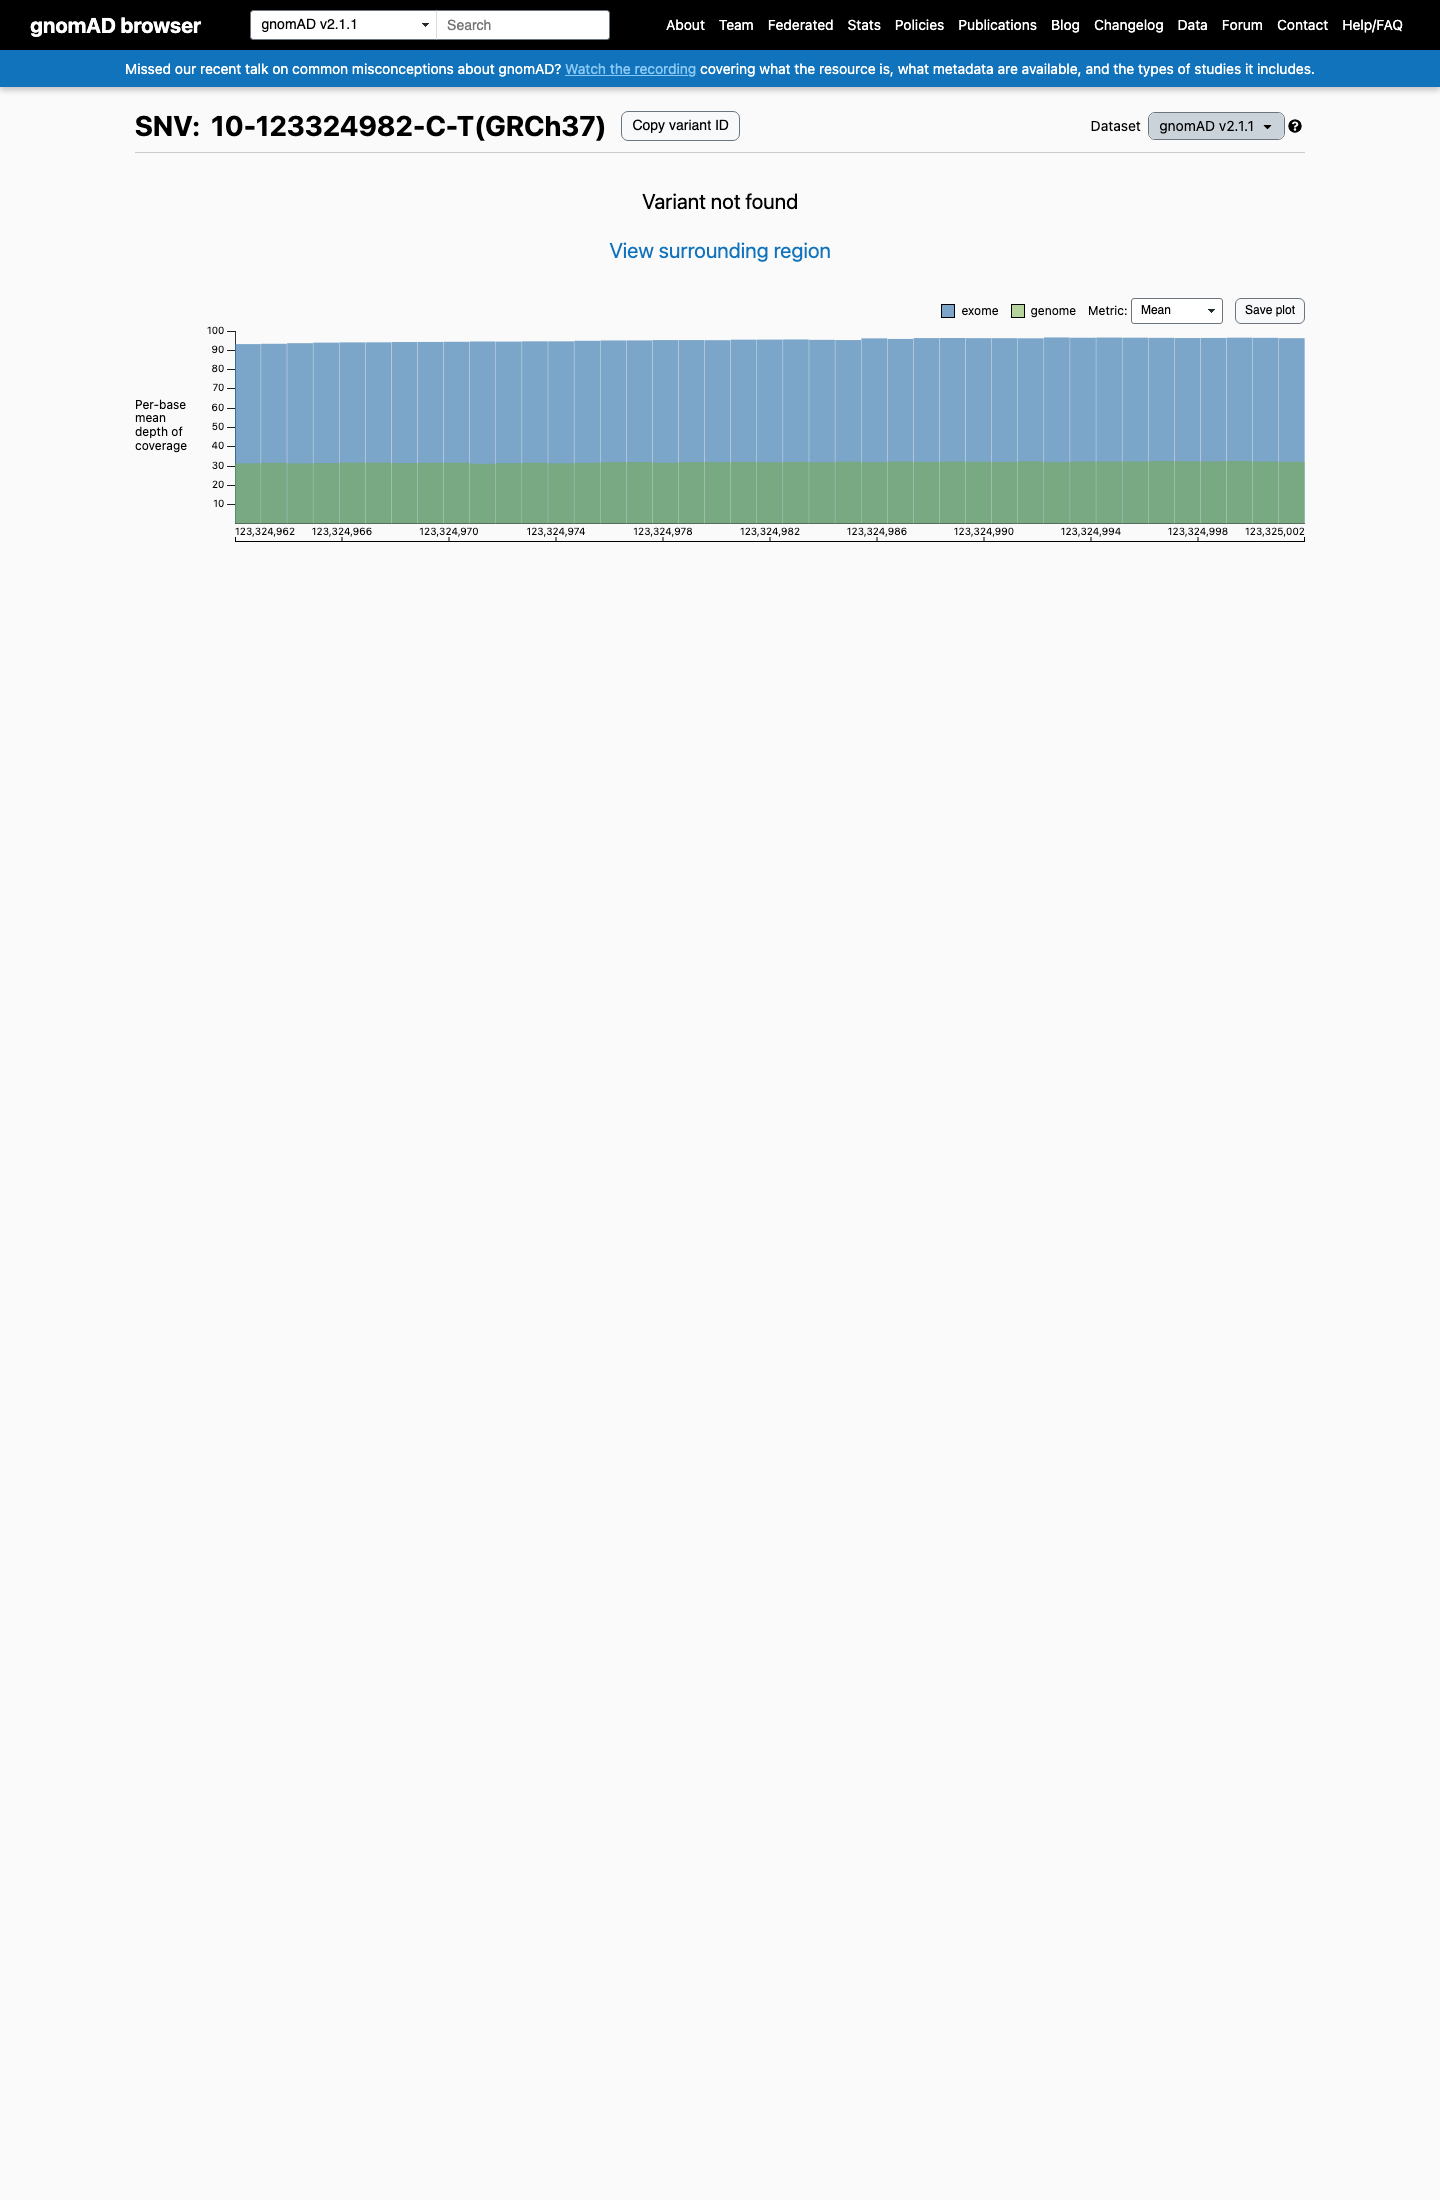
Absent from gnomAD v2.1.
🇨🇦 CA
Absent from gnomAD-Canada v1.0.
Allele frequency by ancestry
three datasets · side by side
gnomAD v4.1
0.00012%
· 2 / 1,614,194
0 hom · FAF 2.8e-05%
European (non-Finnish)
2 / 1,180,042
0.00017%
+ 9 not observed (Remaining individuals, Admixed American, European (Finnish), Amish, East Asian, Middle Eastern, South Asian, Ashkenazi Jewish, African/African American)
OncoKB did not identify variant-specific reviewed functional evidence for this variant; gene-level curated context is available for reviewer follow-up. FGFR2, a receptor tyrosine kinase, is altered by mutation, chromosomal rearrangement or amplification in various cancer types.
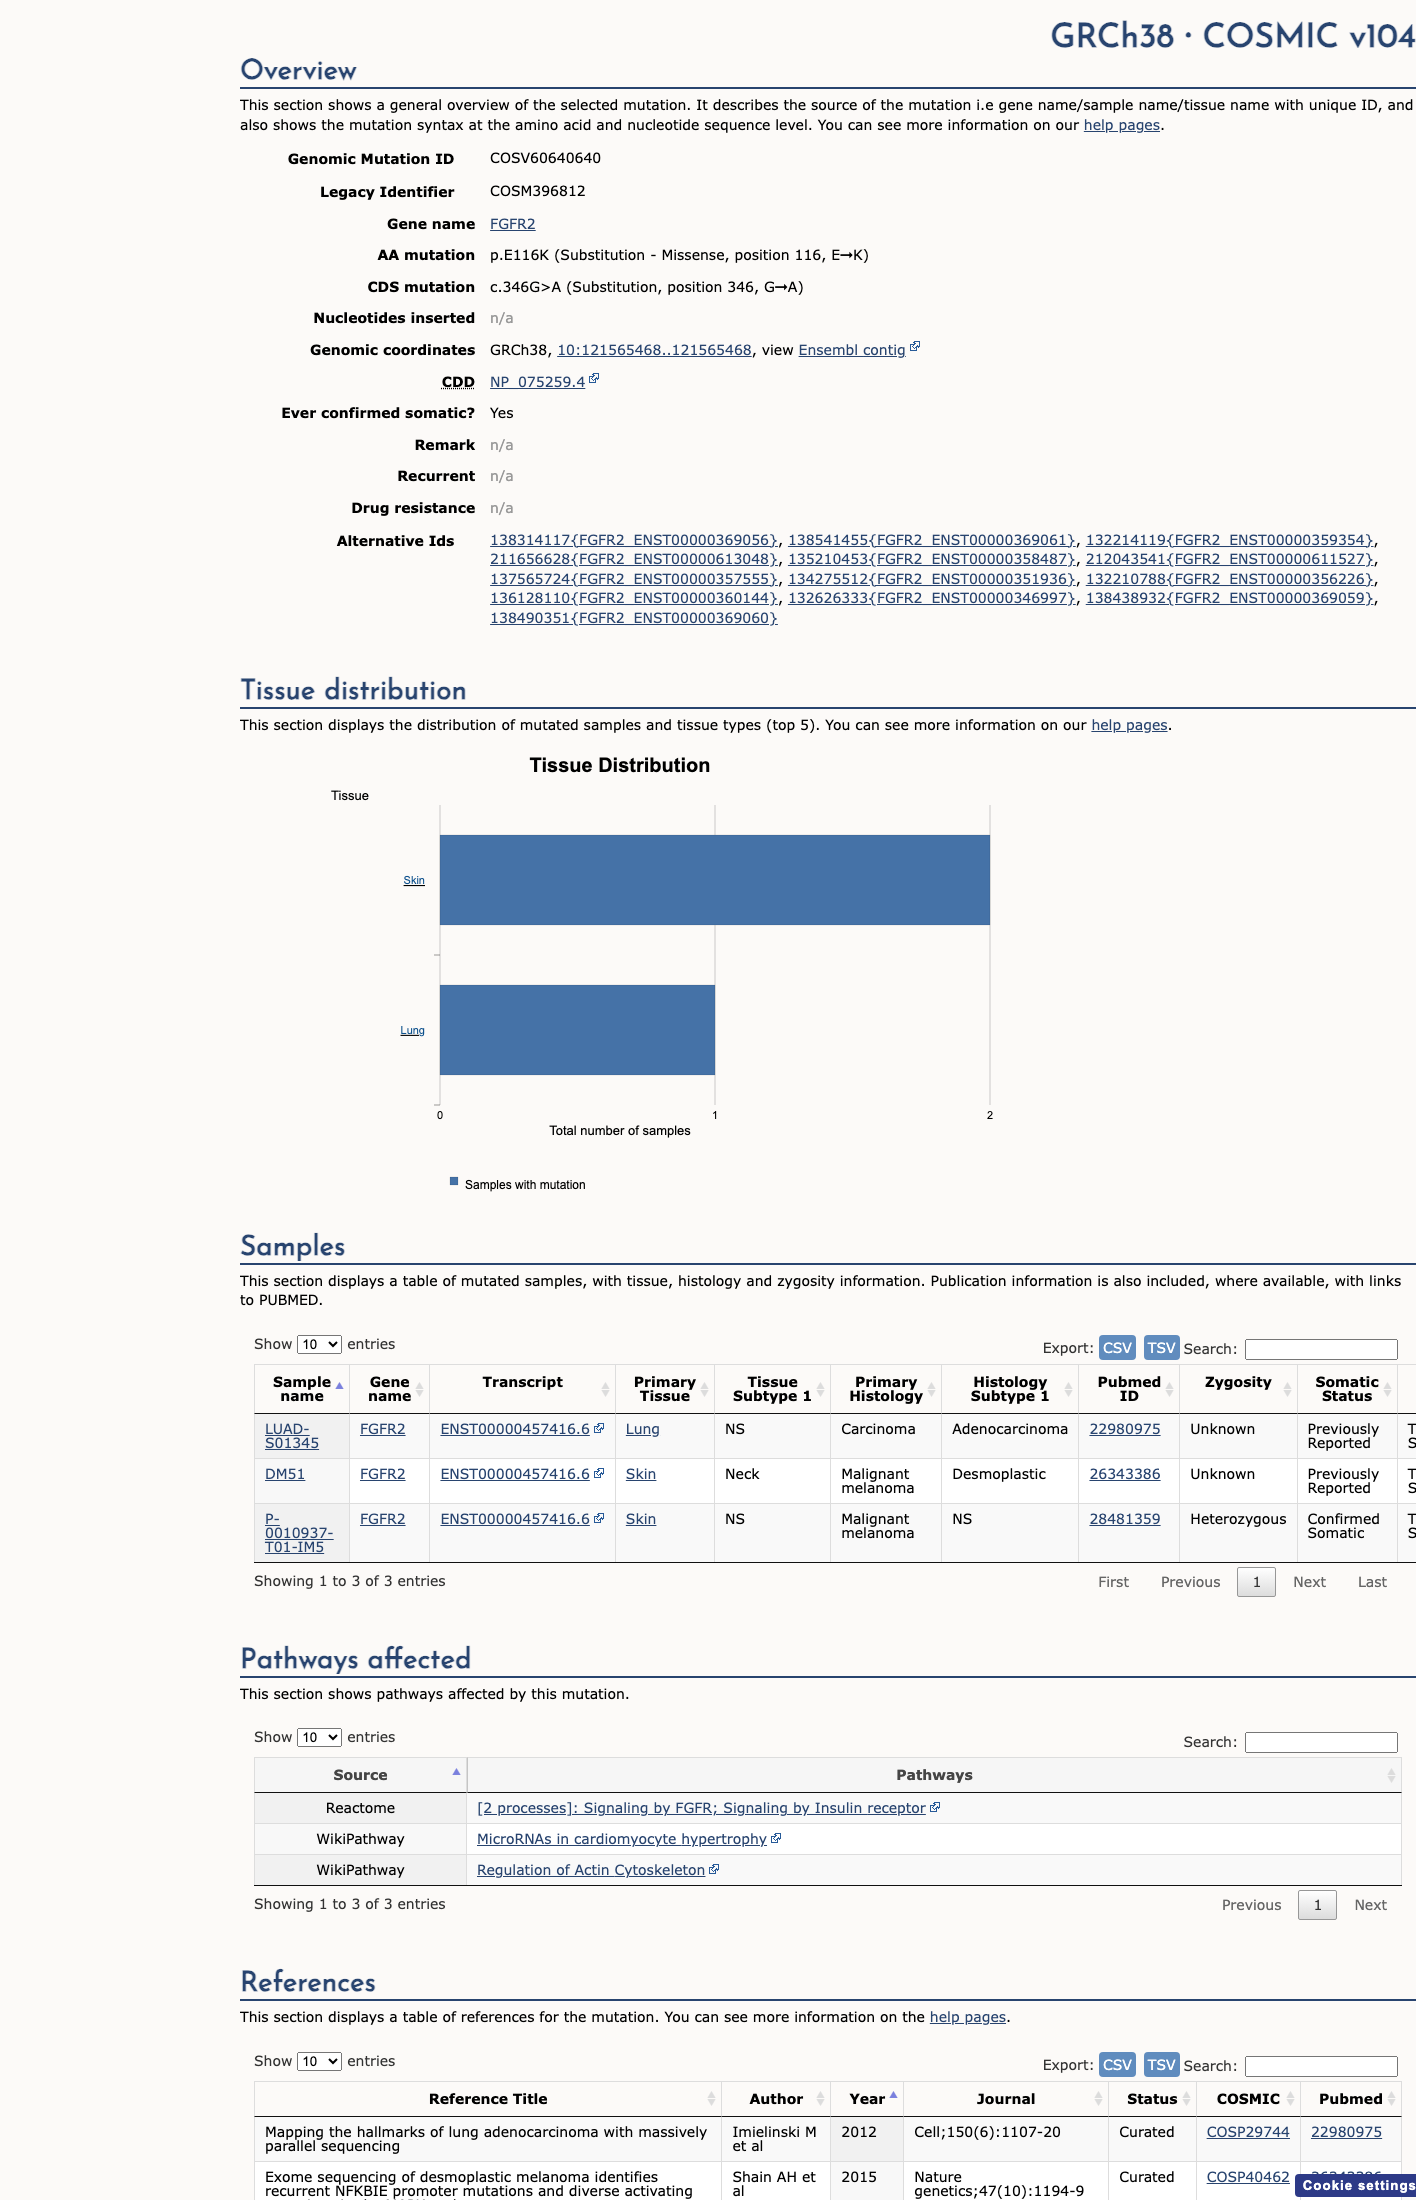
This variant does not lie in a statistically significant hotspot. This variant has previously been reported in somatic cancers (COSMIC; COSV60640640, n = 3 times).
Hotspots
This variant does not lie in a statistically significant hotspot.