Back
NM_006231.4:c.286-8C>G
p.? · POLE
León-Castillo et al. 2020 custom POLE framework · vleon-castillo-2020-custom-framework-v1
0%
complete
Final classification
VUS
PM2BP4
POLE
c.286-8C>G
p.?

POLE encodes the catalytic subunit of DNA polymerase epsilon, the enzyme that replicates the leading strand of DNA during cell division and participates in DNA repair. It contains a proofreading domain that corrects replication errors, keeping the accumulation of mutations in check. Germline mutations in POLE cause polyposis and predispose to colorectal cancer, and are also linked to a rare syndrome of facial dysmorphism, immunodeficiency, livedo, and short stature. Somatic mutations, particularly in the proofreading domain, occur in colorectal and endometrial cancers, where they drive an ultra-mutated tumor phenotype and are associated with better responses to immune checkpoint inhibitors.

This variant

POLE germline variants predispose to polyposis and colorectal cancer, with pathogenic missense changes concentrated in the exonuclease proofreading domain. This intronic variant is absent from population databases but predicted to have no splice impact, so no evidence links it to POLE disease mechanisms; it remains a variant of uncertain significance pending functional splicing and clinical data.

Transcript
NM_006231.4
HGVS · transcript:coding
NM_006231.4:c.286-8C>G
GRCh38
chr12:132680230 G>C
GRCh37
chr12:133256816 G>C
VUS: one pathogenic-supporting criterion (PM2, absent from gnomAD) and one benign-supporting (BP4, SpliceAI 0.08) meet no qualifying ACMG combination rule.
Classification rationale
PM2 BP4 VUS
POLE c.286-8C>G

PM2 (Supporting): absent from gnomAD v2.1 and v4.1 (AF=0), consistent with a rare disease-associated allele. BP4 (Supporting): SpliceAI max delta 0.08, below the 0.1 threshold, predicts no significant splice impact. Final classification: VUS — one pathogenic-supporting and one benign-supporting criterion satisfy no qualifying ACMG combination rule.

PM2 + BP4 → VUS
LYFE Sciences is an AI system, and it can make mistakes. Criteria may be applied incorrectly, sources may be misread, and a confident-looking classification can still be wrong. Double-check every criterion and its underlying evidence before relying on any call.
Gene diagram · NM_006231.4 · variants mapped to exon structure
POLE NM_006231.4
Fetching transcript structure from UCSC…
Applied criteria · 2 applied · 18 assessed
MetEvidence satisfies this criterion.
Not metEvaluated against available evidence; threshold not reached.
Not assessedApplies in principle, but no evidence was found to evaluate it.
N/ADoesn't apply to this variant type.
Applied · 2
Strength Supporting Moderate Strong Very strong
PM2 supporting Pathogenic
Met (supporting): absent from gnomAD v2.1 and v4.1 (AF=0), below the <0.1% ultra-rare threshold.
Absent (AF=0) in gnomAD v2.1 (GRCh37) and gnomAD v4.1 (GRCh38); AF=0 < project non-VCEP PM2 threshold of 0.1% (user profile convention).Base rule: ACMG/AMP 2015 PM2 (PMID 25741868) - absent in controls or extremely low frequency.PM2 supporting-strength calibration: Whiffin N et al., 'Using high-resolution variant frequencies to empower clinical genome interpretation', Genet Med 2017 (PMID 28518168), recommending PM2 at supporting strength for absence/ultra-rareness in population databases.
BP4 supporting Benign
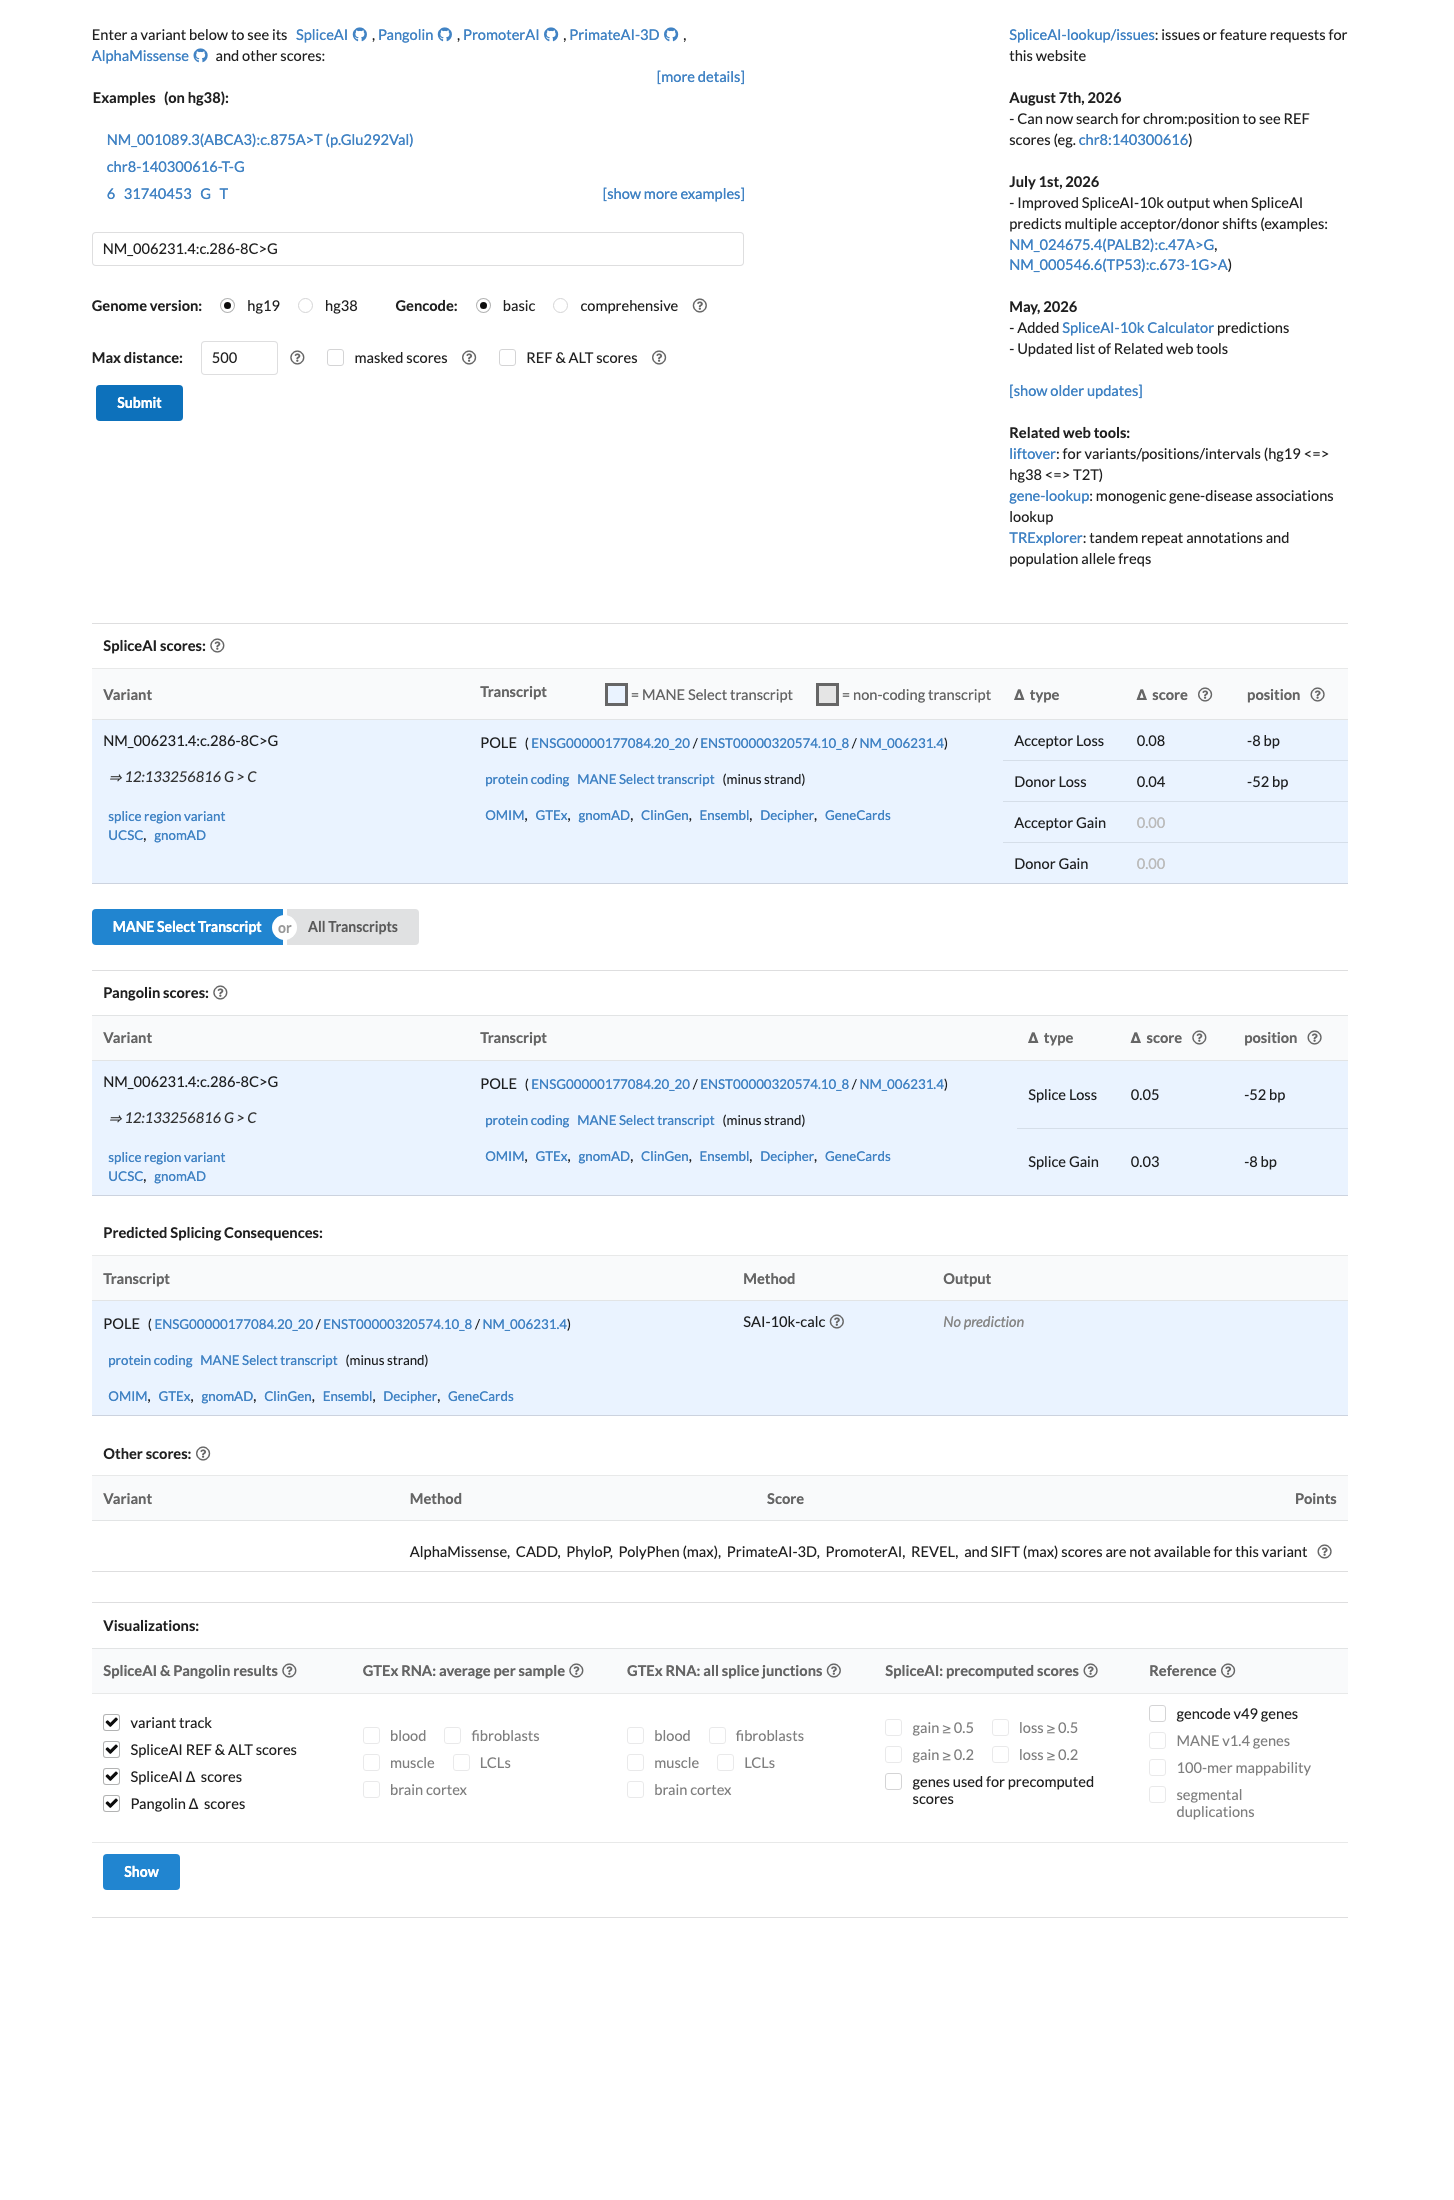
Met (supporting): SpliceAI max delta 0.08, below the 0.1 threshold; no significant splice impact predicted.
SpliceAI Lookup (spliceai): max delta 0.08 (DS_AG 0.0, DS_AL 0.08, DS_DG 0.0, DS_DL 0.04) - SpliceAI predicts no significant splice impact; below the BP4 threshold.Generic in-silico operating thresholds (generic_acmg_combination_rules, source PMID 25741868): for intronic/synonymous/non-canonical-splice-position variants evaluate SpliceAI only; SpliceAI max delta <0.1 -> BP4 supporting, per SVI-recommended thresholds (Walker et al. 2023, ClinGen SVI Splicing Subgroup report, PMID 37442131). Max delta 0.08 is <0.1, so BP4 supporting is met.Custom POLE BP4 rule (final_classification_framework; vcep_path_250_323_s003 / vcep_path_250_323_s004): applies only to exact missense variants listed in Supplementary Tables S2/S3; c.286-8C>G is intronic and absent, so the framework falls back to the generic in-silico workflow.
Assessed · not applied · 7 not met · 11 not assessed
Pathogenic
PVS1 Not met: no null-allele effect predicted — SpliceAI max delta 0.08, below the 0.1 threshold.
PS2 Not assessed: no proband-parent trio data with confirmed parentage was available to evaluate a de novo occurrence.
PS3 Not assessed: no functional assay evidence, such as RNA or minigene studies, was available for this variant.
PS4 Not assessed: no case-control, cohort, or somatic-recurrence data existed for this variant in any source.
PM3 Not assessed: no second POLE variant or phase data was available to establish a trans configuration.
PM6 Not assessed: no de novo observation of the variant was reported in ClinVar or the literature.
PP1 Not assessed: no affected family members were tested, so no segregation data existed.
PP3 Not met: SpliceAI max delta 0.08, below the >0.2 PP3 threshold for predicted splice impact.
PP4 Not assessed: no proband phenotype or family-history information was available to judge phenotype specificity.
PP5 Not met: no expert-panel ClinVar classification exists; the only submission is a single-lab Likely benign record.
Benign
BA1 Not met: absent from gnomAD (AF=0), far below the >1% BA1 population-frequency threshold.
BS1 Not met: allele frequency 0, below the >0.3% threshold; no excess carrier frequency observed.
BS2 Not met: no carriers observed in healthy individuals (AF=0); BS2 requires positive observation of the variant.
BS3 Not assessed: no well-established functional assay, such as an RNA splicing study, demonstrating normal function.
BS4 Not assessed: no family-testing data existed to observe a non-segregation event.
BP2 Not assessed: no second POLE variant was observed, so no cis/trans configuration could be evaluated.
BP5 Not assessed: no proband data on an alternate molecular basis for disease was available.
BP6 Not met: no expert-panel ClinVar classification exists; the single-lab Likely benign label does not qualify.
N/A · 8 PS1 · PM1 · PM4 · PM5 · PP2 · BP1 · BP3 · BP7
Research & evidence
Population frequency
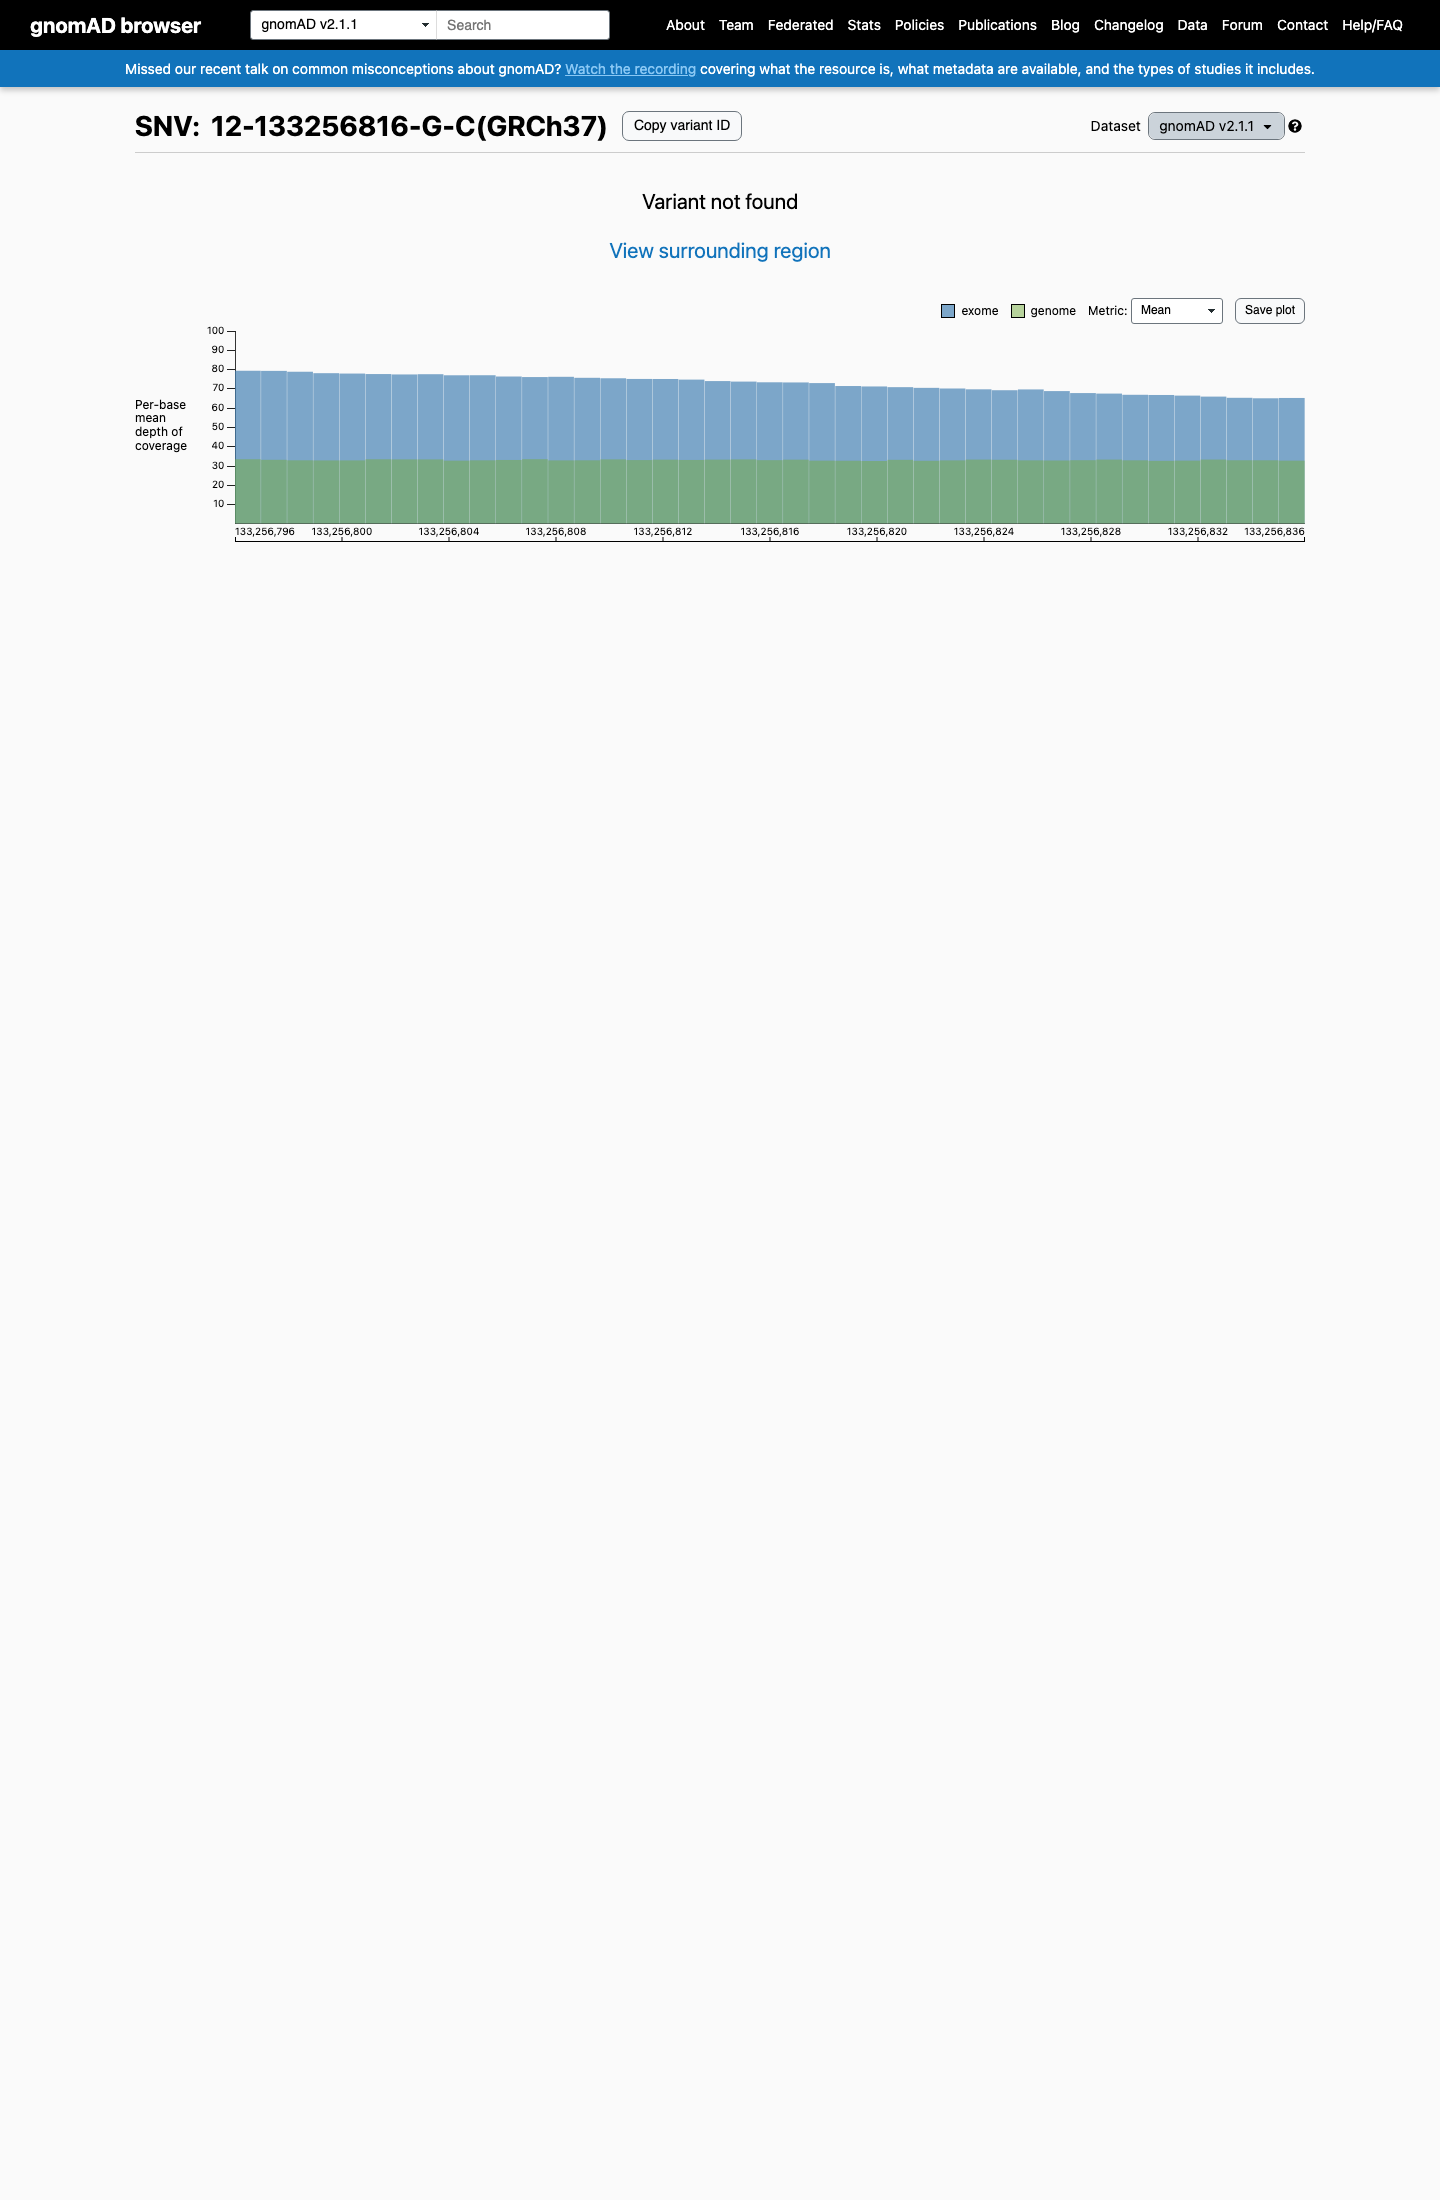
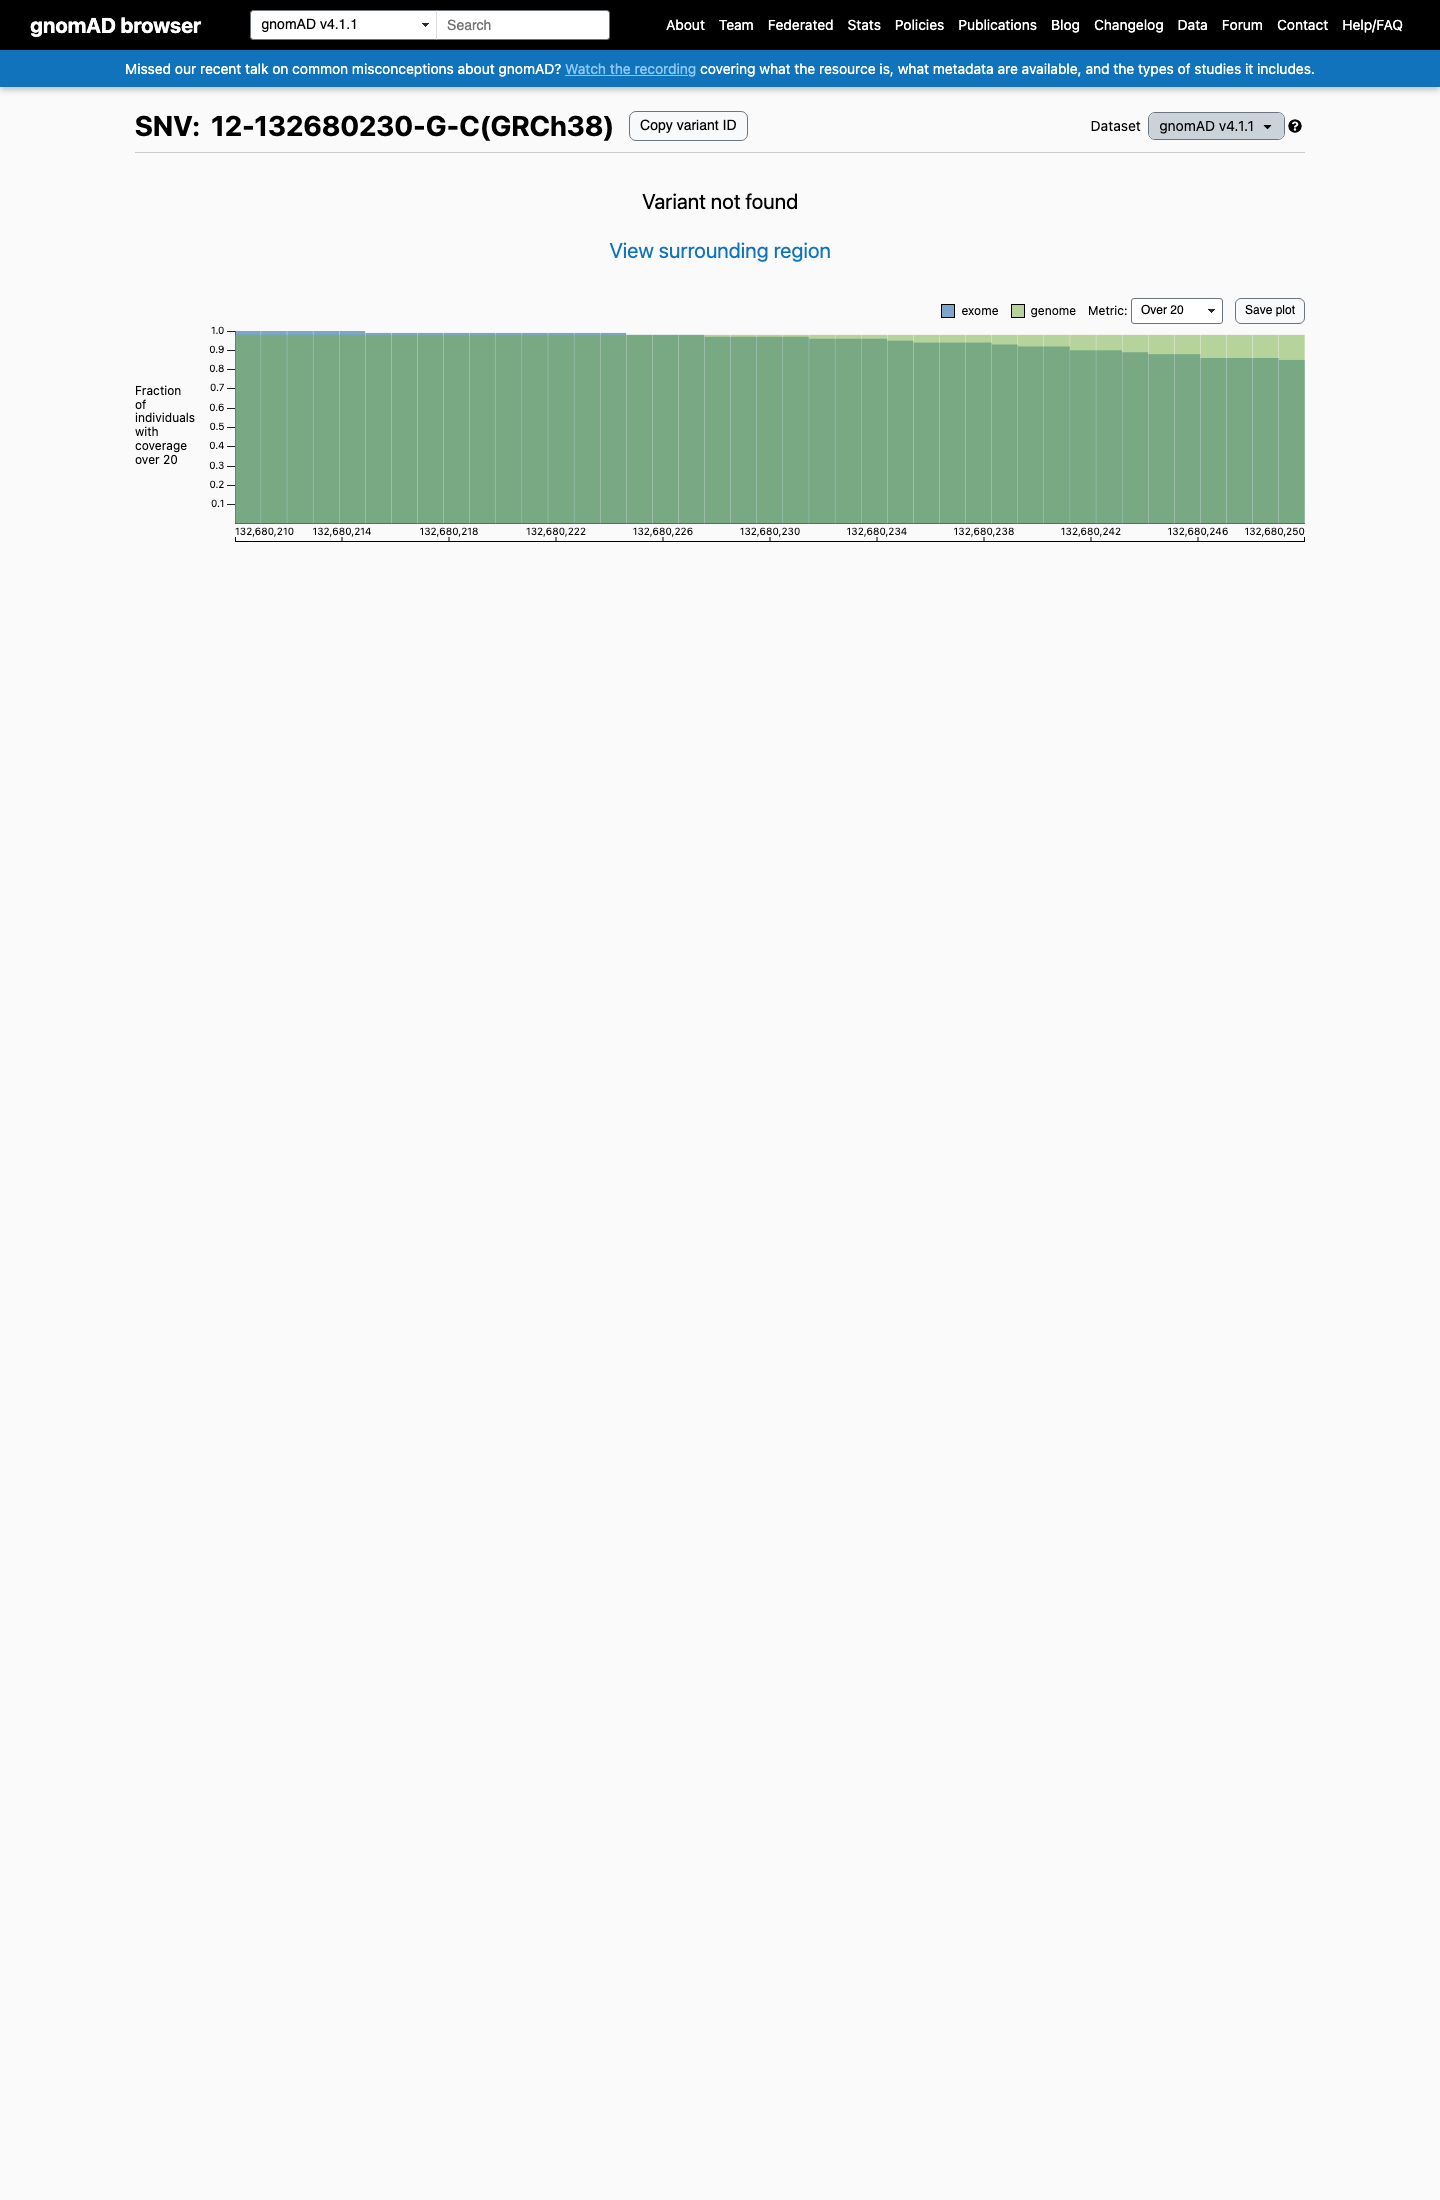
gnomAD v4.1 screenshot
gnomAD v4.1
gnomAD v2.1 screenshot
gnomAD v2.1
v4.1
Absent from gnomAD v4.1.
v2.1
Absent from gnomAD v2.1.
🇨🇦 CA
Not available in gnomAD-Canada v1.0.
Allele frequency by ancestry
three datasets · side by side
gnomAD v4.1
Absent · 0 / ?
0 hom
Not observed in any ancestry group.
gnomAD v2.1
Absent · 0 / ?
0 hom
Not observed in any ancestry group.
gnomAD Canada 🇨🇦
Absent · 0 / ?
0 hom
Not observed in any ancestry group.
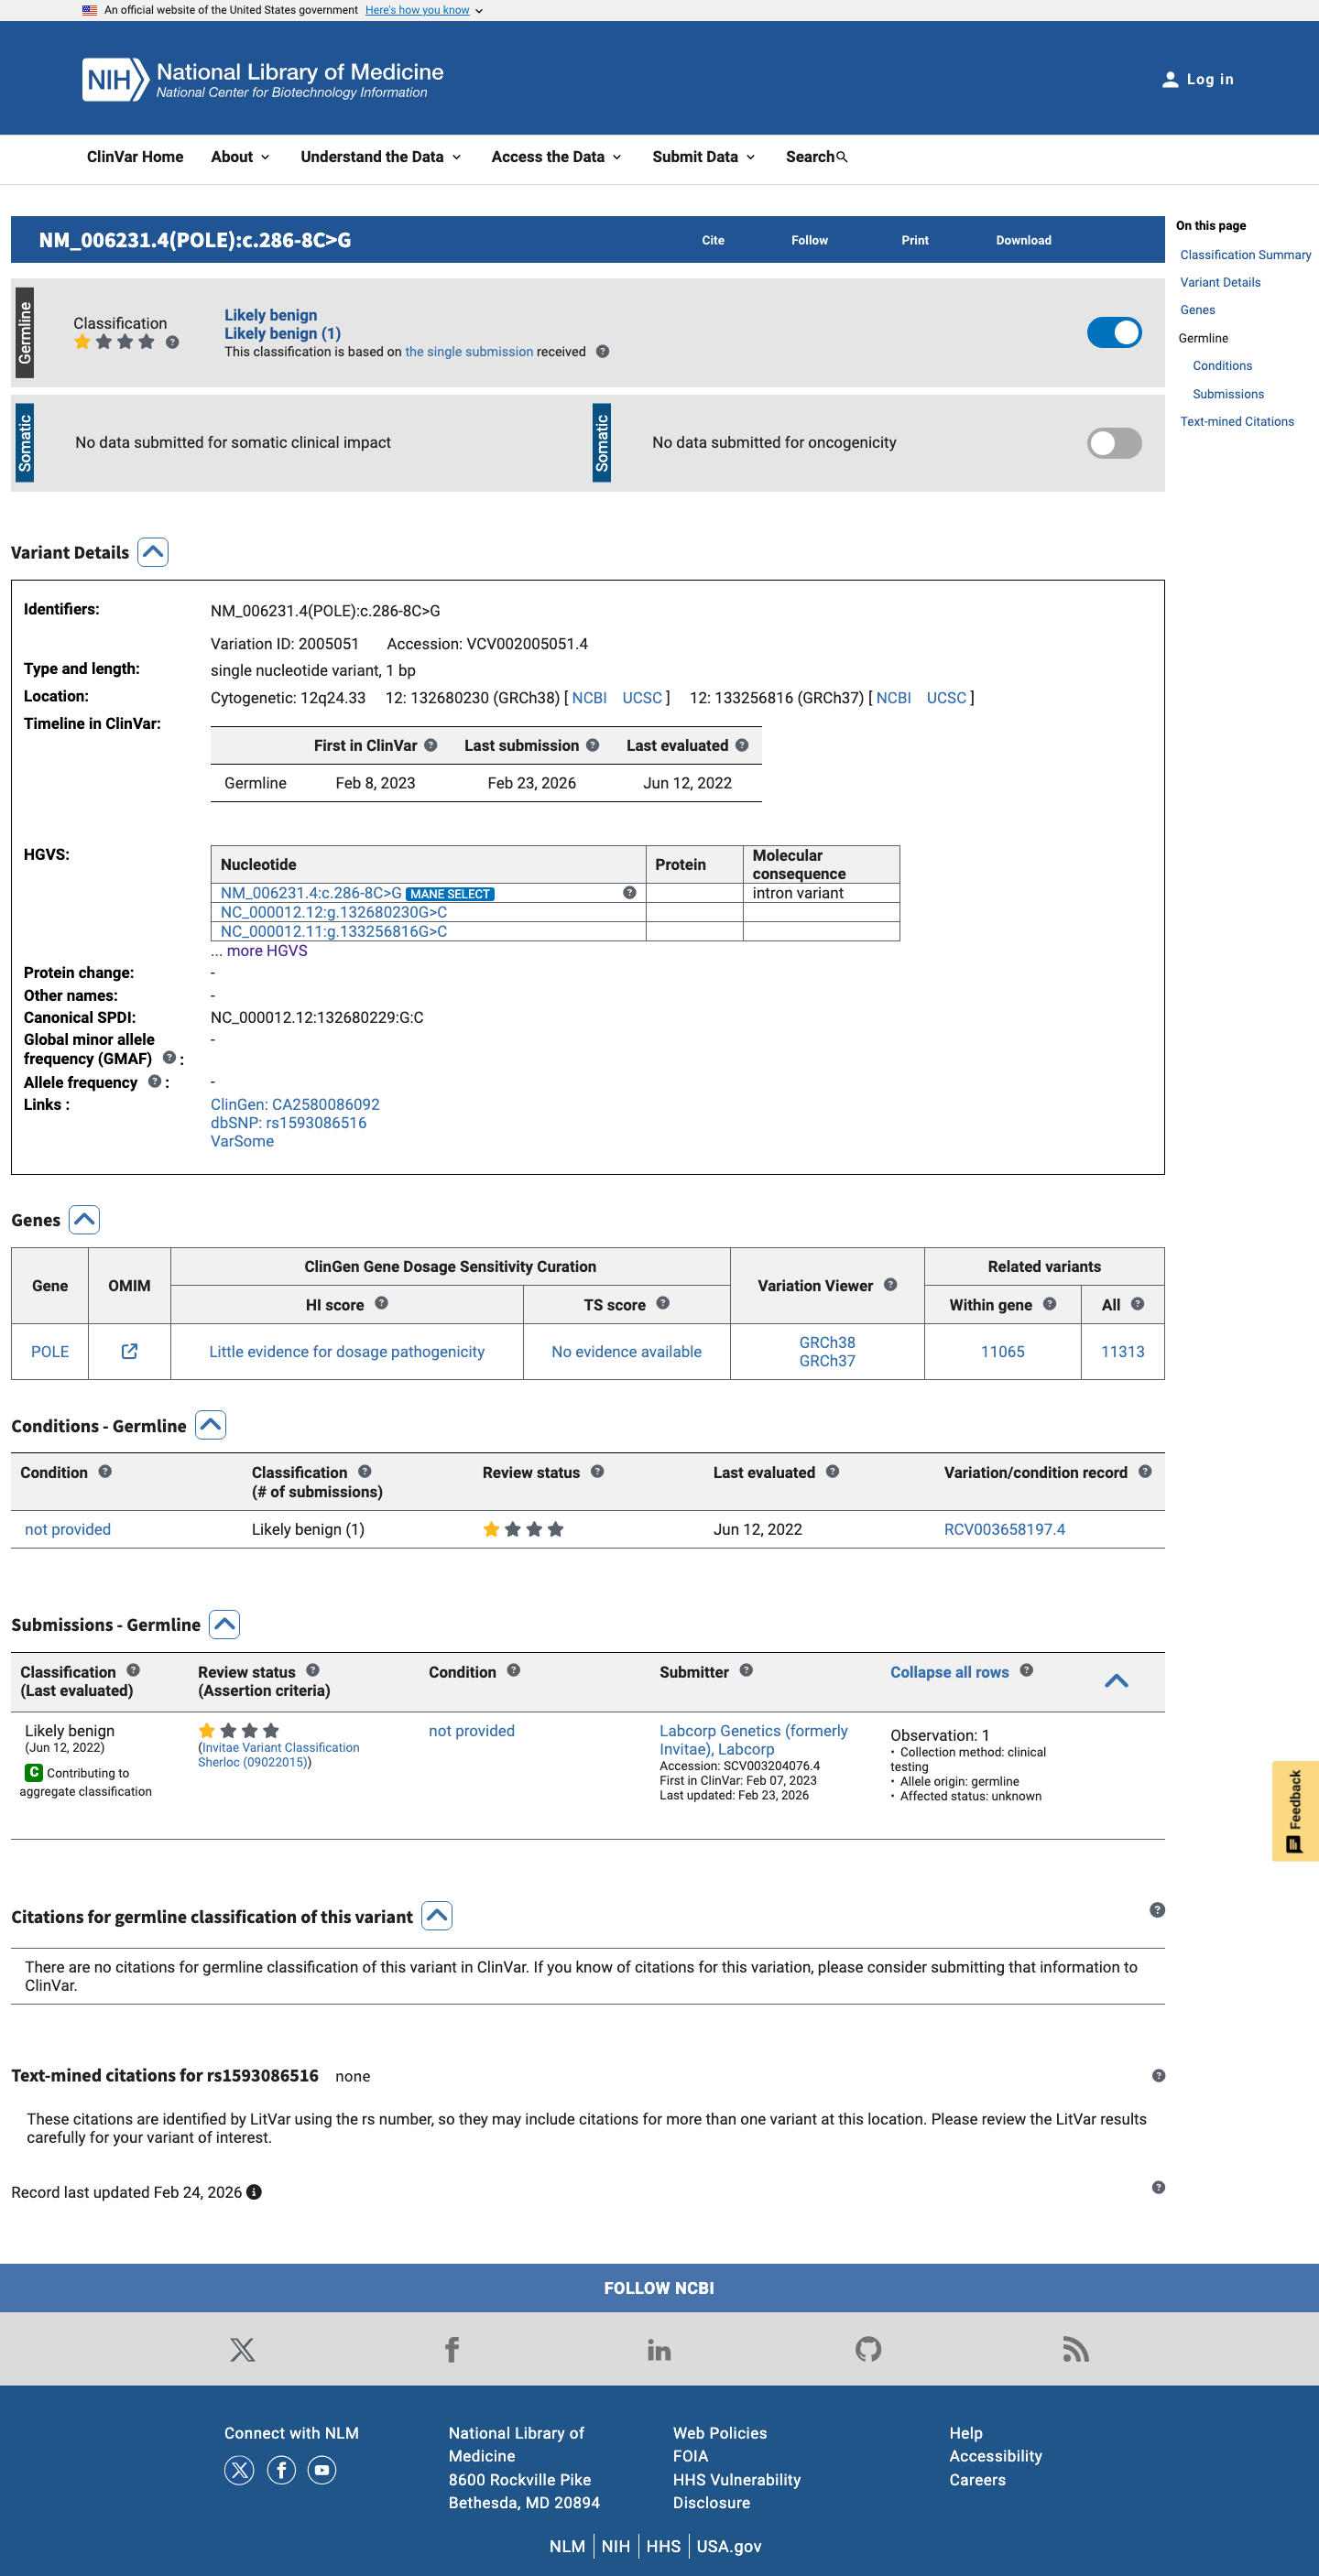
ClinVar screenshot
ClinVar
This variant has been reported in ClinVar as Likely benign (1 clinical laboratory). (ClinVarID = 2005051)
SpliceAI screenshot
In silico
SpliceAI predicts no significant splice impact for this variant (max delta score = 0.08).
Functional No data
No calibrated functional assay or RNA evidence was identified for this variant.
OncoKB ↗
COSMIC screenshot
COSMIC
Somatic evidence
COSMIC
This variant has not previously been reported in somatic cancers (COSMIC).
Hotspots
This variant does not lie in a statistically significant cancer hotspot.
COSMIC ↗
Literature · how each cited paper was used
1papers cited
Each card is an audit: what was searched, what was found, whether it names the variant, which criteria it fed, and why.
Rule & framework references · cited for criterion definitions, not variant evidence
28492532 ↗ Sherloc: a comprehensive refinement of the ACMG-AMP variant classification criteria.
Sources & reference links
7Sources
ClinVar
gnomAD v2.1
gnomAD v4.1
gnomAD-Canada
SpliceAI
OncoKB
COSMIC