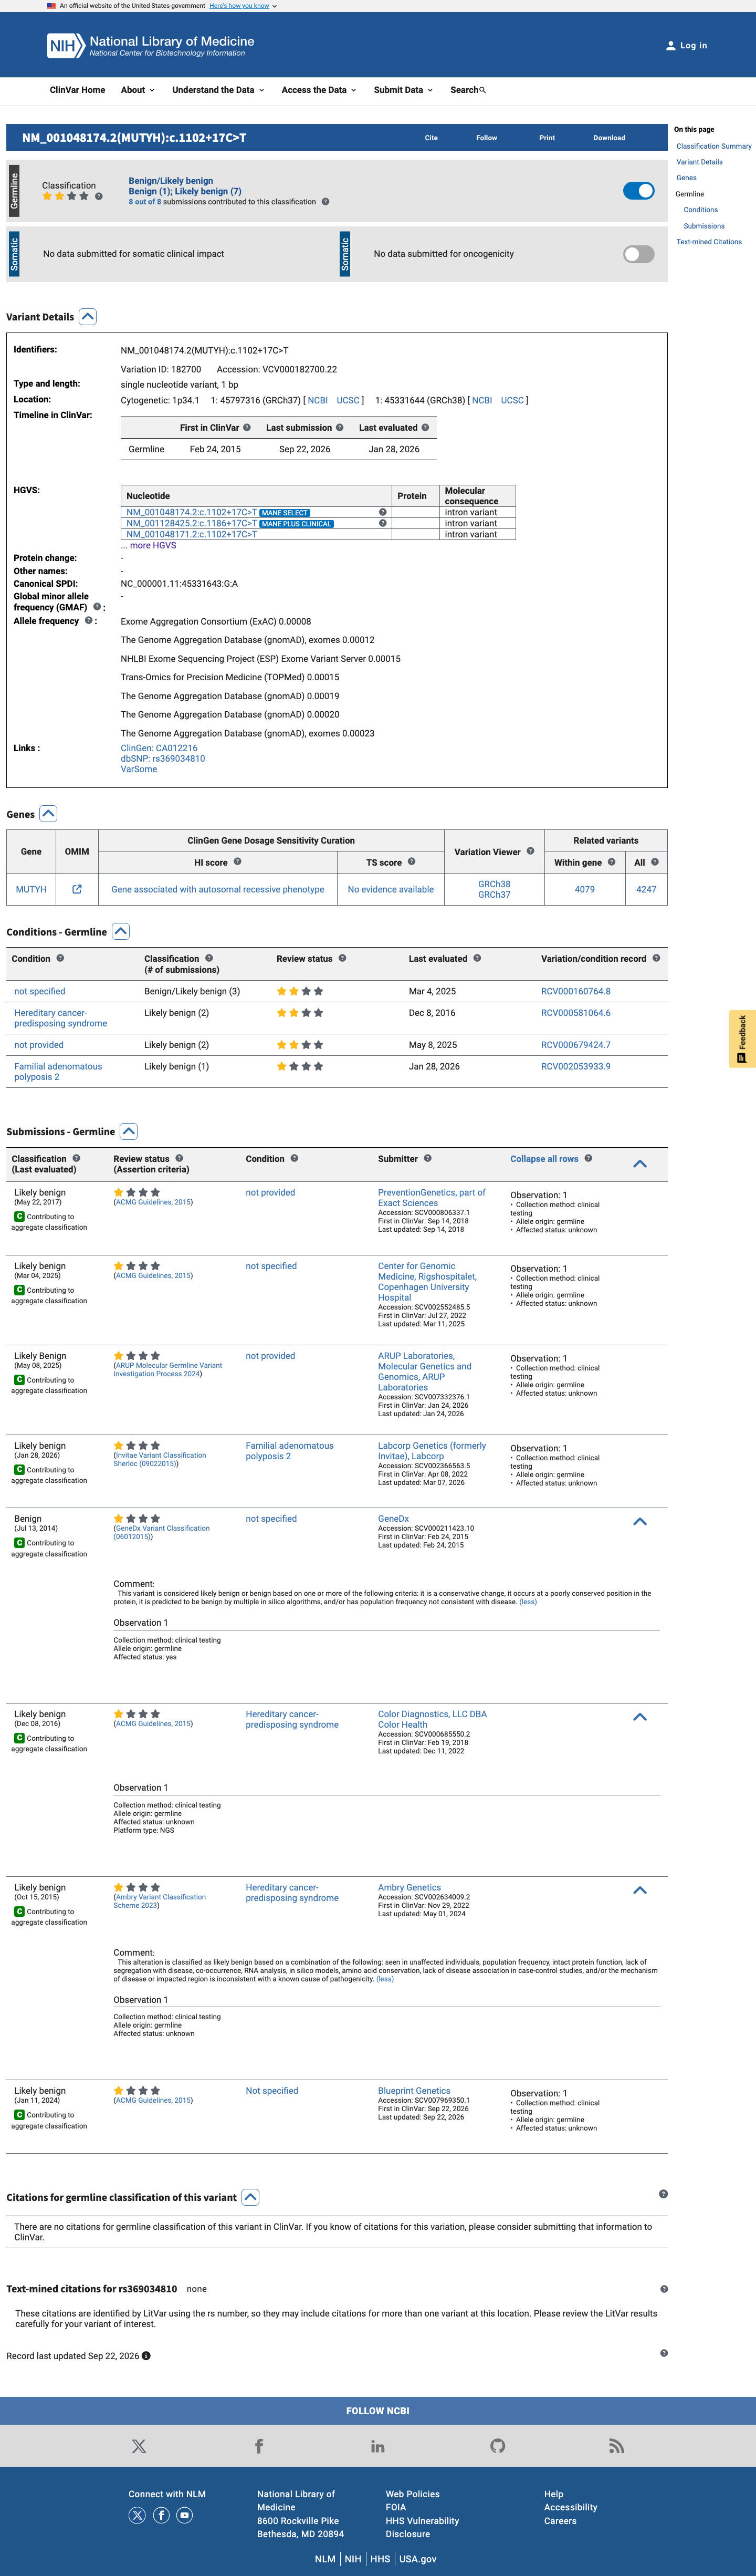
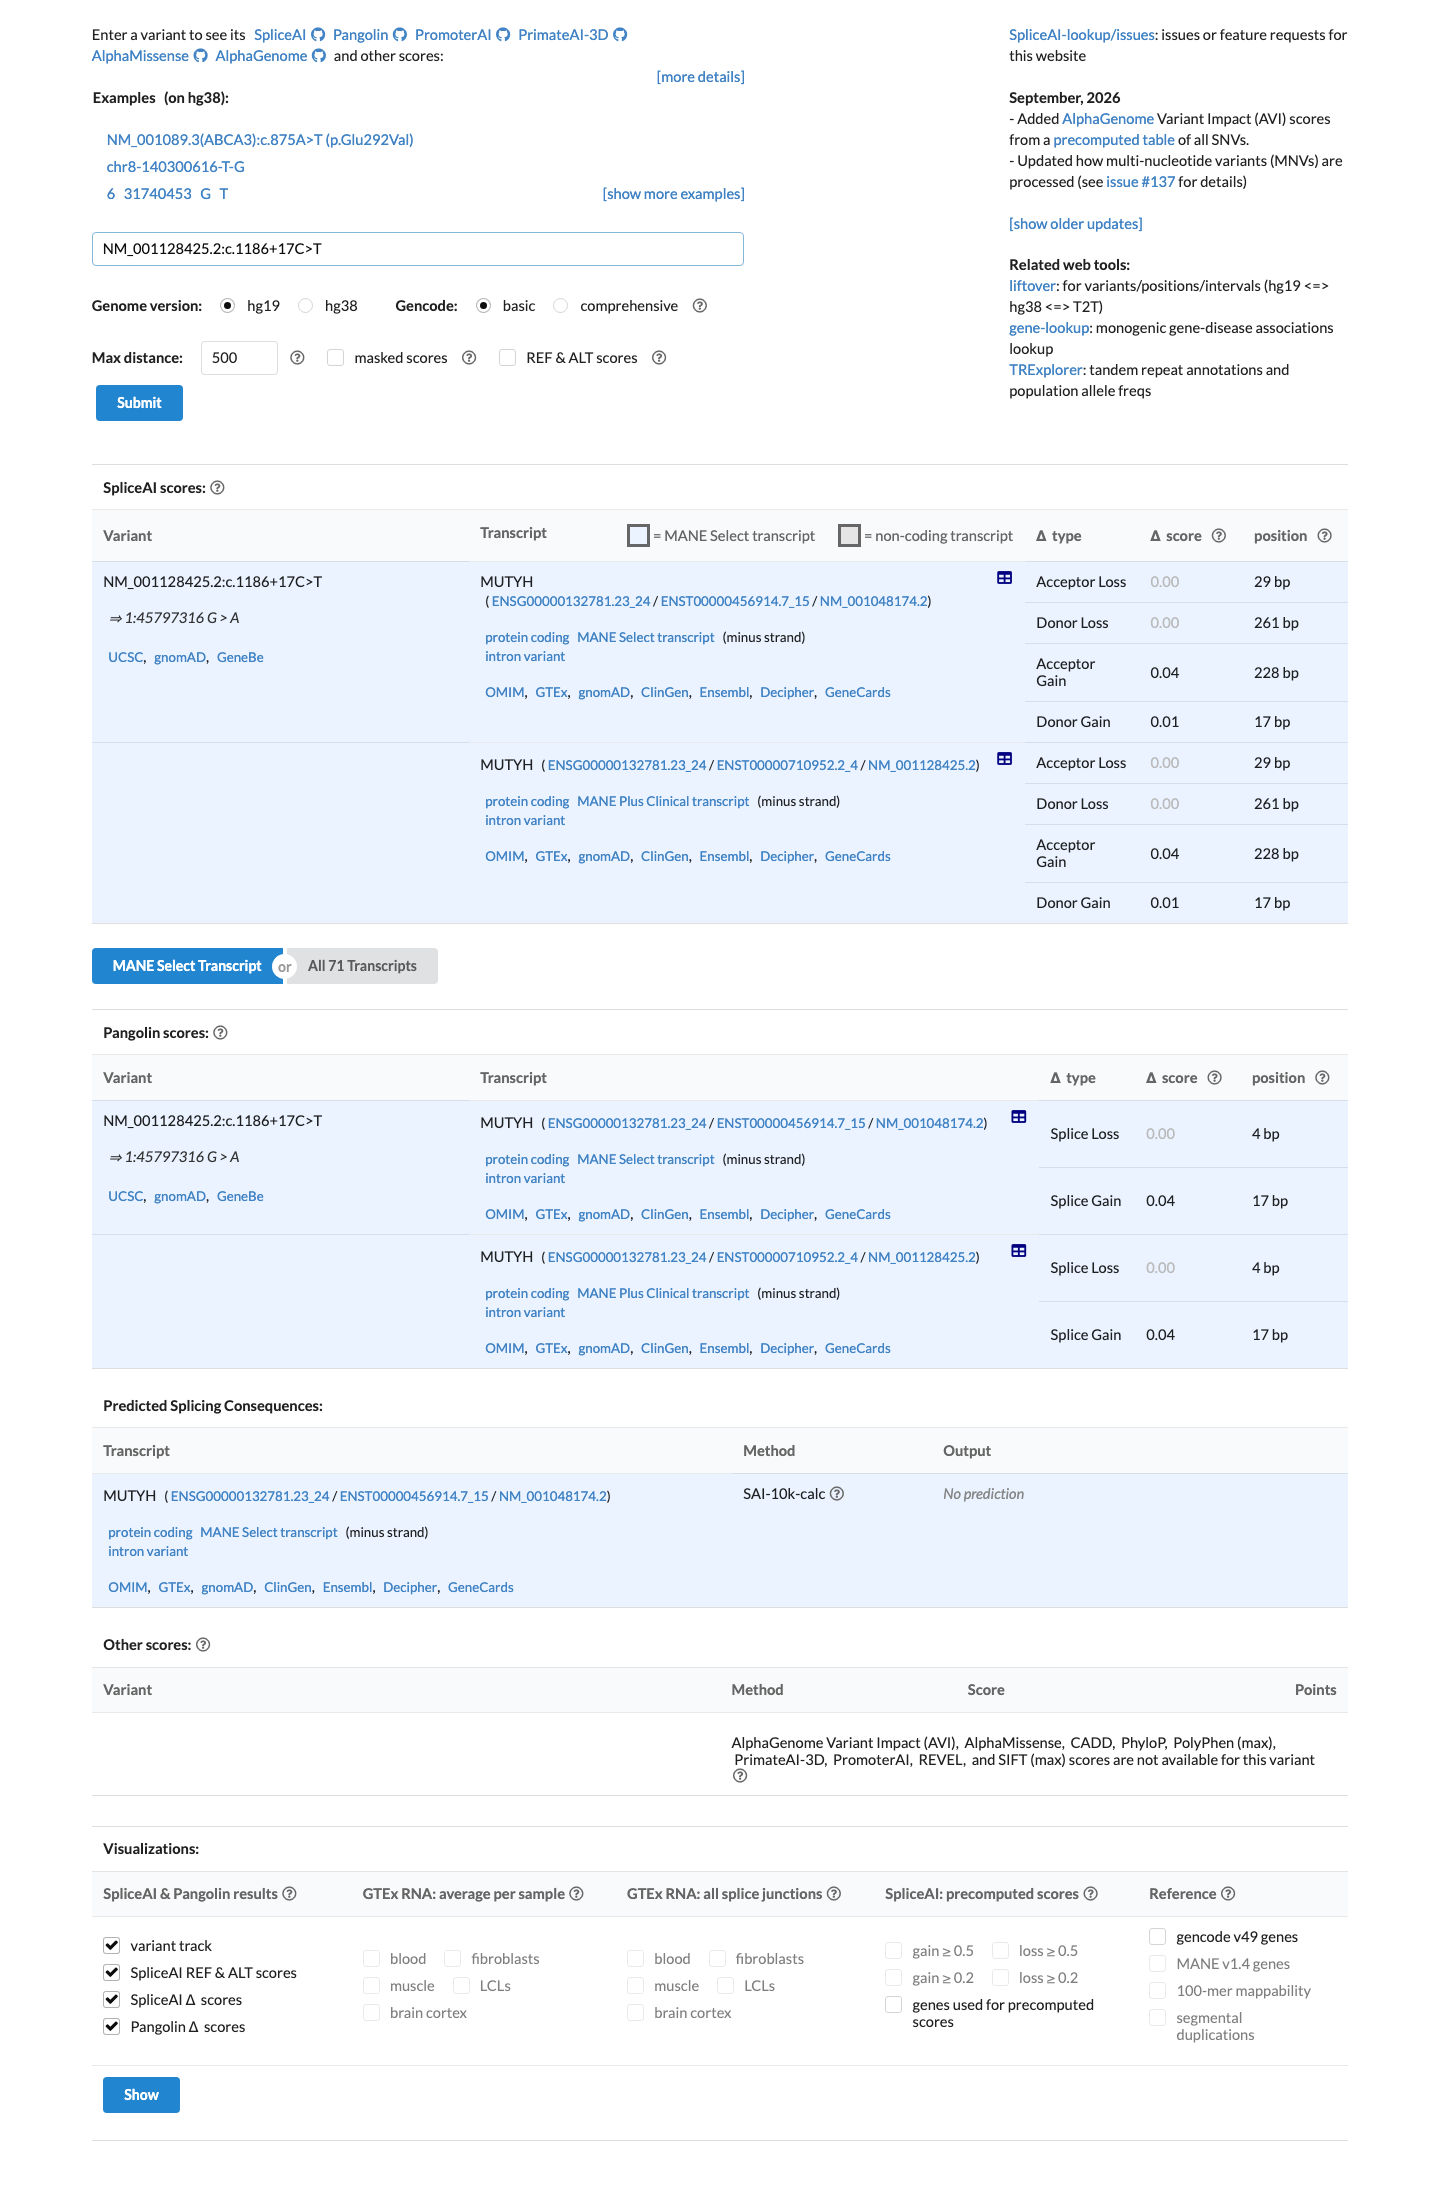
Group scope: the five criteria adjudicated here (PS1, PM1, PM5, PP2, BP1) are all keyed to a variant's codon, amino-acid residue, or position within a critical functional domain. Governing framework: the ClinGen InSiGHT Hereditary Colorectal Cancer/Polyposis Expert Panel Specification for MUTYH v1.0 is the applicable gene-specific specification and was consulted first; generic ACMG/AMP 2015 definitions were used only for the criterion definitions themselves. The InSiGHT MUTYH ruleset was present as a framework label but carried no machine-extractable criterion-level rule payload in this case, and its domain table was not available. Variant: MUTYH NM_001128425.2:c.1186+17C>T (NC_000001.10:g.45797316G>A) is an intronic substitution 17 nucleotides into the intron downstream of the exon ending at c.1186. It produces no amino-acid change (NP_001121897.1:p.?), has no residue context, and is not a missense allele. ClinVar mirrors this as NM_001048174.2:c.1102+17C>T. PS1, PM5, PP2 and BP1 are defined only for missense (amino-acid-substituting) variants; with no codon or residue produced, they are not applicable rather than refuted. PM5 specifically is residue-anchored and the case's own candidate harvest found no residue and zero candidates. PM1 is location-based and was assessed rather than set aside: vcep_materials.json contains no domain_tables entry for MUTYH, so no VCEP-approved critical-domain list existed to test a residue against, and no hotspot resource returned data. Independently decisive, the variant is non-coding and therefore cannot lie in a coding functional domain or missense hotspot; PM1 is not met. No evidence in this group supports any pathogenic or benign codon/residue/domain-based assertion for this allele; the benign direction of this variant rests on other evidence groups (population frequency, ClinVar submissions), not on BP1. All four segregation/de novo criteria (PS2, PM6, PP1, BS4) are unassessable for this variant because the evidence assembled for NM_001128425.2:c.1186+17C>T contains no proband, no trio or parental testing, no pedigree and no genotyped relatives - there are zero informative meioses. The ClinVar record (variation 182700) holds only eight laboratory clinical-testing submissions with no criterion leads or family-level data, and the variant is not mentioned in any of the four fetched full texts. The governing InSiGHT Hereditary Colorectal Cancer/Polyposis VCEP specification for MUTYH (CSPEC doc 1742141534, v1.0) was retrieved but is an unapproved ruleset in preparation with an empty criteria payload, so the generic ACMG/AMP 2015 definitions of PS2, PM6, PP1 and BS4 were applied; all four are recorded as not assessed rather than not met, since the absence of family data does not constitute negative evidence, and none may be met from population frequency or from another source's benign classification. Neither PS3 nor BS3 can be adjudicated for MUTYH NM_001128425.2:c.1186+17C>T. Both criteria require well-established functional assay evidence (deleterious for PS3, non-damaging for BS3), and no functional or transcript/splice assay of this variant exists in the case evidence: no paper in the seven-PMID triage set reports functional data, all four extracted full texts were screened for the variant with zero hits, and the ClinVar submission audit yielded zero usable criterion leads. For this deep intronic (+17) variant the only assay route to PS3/BS3 would be a splice/transcript assay (minigene, RNA RT-PCR or RNA-seq) or an equivalent protein assay. In-silico splice prediction is not a substitute for either criterion: it belongs to PP3/BP4, so even a successful SpliceAI run would not satisfy PS3/BS3. SpliceAI returned no scores at all (query timeout), so no calibrated splice prediction is available. Per the case annotation this missing result is explicitly not evidence of absent splice impact and must not be used benignly; the only prediction numbers present are Pangolin (0.041 gain / -0.002 loss), which is uncalibrated for ACMG strength and is not assay evidence. Both criteria are recorded as not_assessed (evidence insufficient) rather than not_met: the requirement is an absent assay, not a contradicting one. The gap is closeable in principle by a transcript assay or a repeat SpliceAI run, and human review is flagged for that reason. The MUTYH InSiGHT VCEP specification (cspec doc 1742141534) was consulted as the governing framework but its criterion payload is not populated in this case, so generic ACMG/AMP 2015 (PMID:25741868) was applied for both criteria; no gene-specific PS3/BS3 strength calibration was available to use. No case-control or cohort evidence demonstrates enrichment of MUTYH NM_001128425.2:c.1186+17C>T in affected individuals; no retrieved source names the variant, so PS4 is not met.1 No expert-panel ClinVar assertion exists for this exact variant (review status 'criteria provided, single submitter', 0 expert-panel submissions), so neither the pathogenic (PP5) nor the benign (BP6) expert-panel-based assertion criterion is met; the aggregate Likely benign label reflects only independent laboratory submissions.2 PP4 and BP5 remain not assessed because the case provides no proband phenotype, family history, or alternate-molecular-basis information against which phenotype specificity or a competing diagnosis could be judged.3 MUTYH-associated disease is autosomal recessive (ClinGen InSiGHT MUTYH specification version 1.0, MONDO:0012041 'familial adenomatous polyposis 2'; PMID:35802134 lists MAP as AR with reporting of 2 pathogenic/likely pathogenic variants; PMID:24310308 describes MYH-associated polyposis as autosomal recessive), so the allelic group operates only on cis/trans configurations and the BP2 'trans with a pathogenic variant for a fully penetrant dominant disorder' clause is structurally unavailable. This is a variant-only assessment of the intronic change NM_001128425.2:c.1186+17C>T (NP_001121897.1:p.?, equivalent to NM_001048174.2:c.1102+17C>T, 17 bp into an intron): there is no affected proband, no genotype and no phase-resolved data of any kind (no segregation, allele-specific, long-read or trio phasing) in the case. PM3 is not met: no source, including the 8 ClinVar submissions for variation 182700 (none expert-panel or VCEP, zero criterion leads, no phase information), reports this variant in trans with a pathogenic or likely pathogenic MUTYH allele, and no biallelic/compound-heterozygous MAP genotype containing it is reported. BP2 is not met: no source reports this variant in cis with a pathogenic or likely pathogenic MUTYH allele, and the alternative trans-with-a-pathogenic-variant-for-a-dominant-disorder clause cannot apply to this recessive gene. Both criteria are therefore non-scoring for this variant; the allelic group contributes neither pathogenic nor benign weight, and the limiting factor is the complete absence of proband-level, phase-resolved data rather than evidence of a benign allelic configuration. No population criterion is met: BA1 and BS1 fall one to two orders of magnitude below their generic thresholds (highest frequency anywhere 0.000543, i.e. 0.054%, versus 0.05 and 0.01), BS2 has no observed homozygote in any cohort despite the autosomal recessive mode of inheritance, and PM2 fails because every gnomAD source, including the non-cancer subsets, exceeds the 0.0001 supporting cutoff. Source selection does not change any verdict: the all-comers v2.1/v4.1 totals (0.000128/0.000232) and the non-cancer v2.1-exome/v3.1-genome subsets (0.000119/0.000196) agree closely, so the unretrievable InSiGHT MUTYH VCEP threshold payload is immaterial here except for the narrow PM2 margin (lowest value only ~19% above 0.0001), which is flagged for human review. Population evidence therefore contributes no pathogenic or benign codes from this group; the variant is rare but consistently present at ~0.01-0.02% in reference populations, so any benign classification must be driven by other criteria groups.
MUTYH encodes a DNA repair enzyme (a glycosylase) that fixes oxidative DNA damage by removing adenine bases that have been mistakenly paired with guanine or with oxidized guanine lesions. Inherited mutations in both copies of the gene cause MUTYH-associated polyposis (MAP), a recessive condition that strongly predisposes people to multiple colorectal polyps and colorectal cancer. The gene acts as a tumor suppressor whose loss of function allows DNA damage to accumulate, and somatic changes in it have also been reported in colon cancer, though whether they drive cancer on their own is not fully established.
MUTYH encodes a DNA-repair glycosylase in which biallelic loss of function causes autosomal recessive MUTYH-associated polyposis, so an intronic change such as c.1186+17C>T would require demonstrated biallelic, splice-altering or loss-of-function evidence before it could be regarded as disease-causing.
No criteria were applied for this variant.
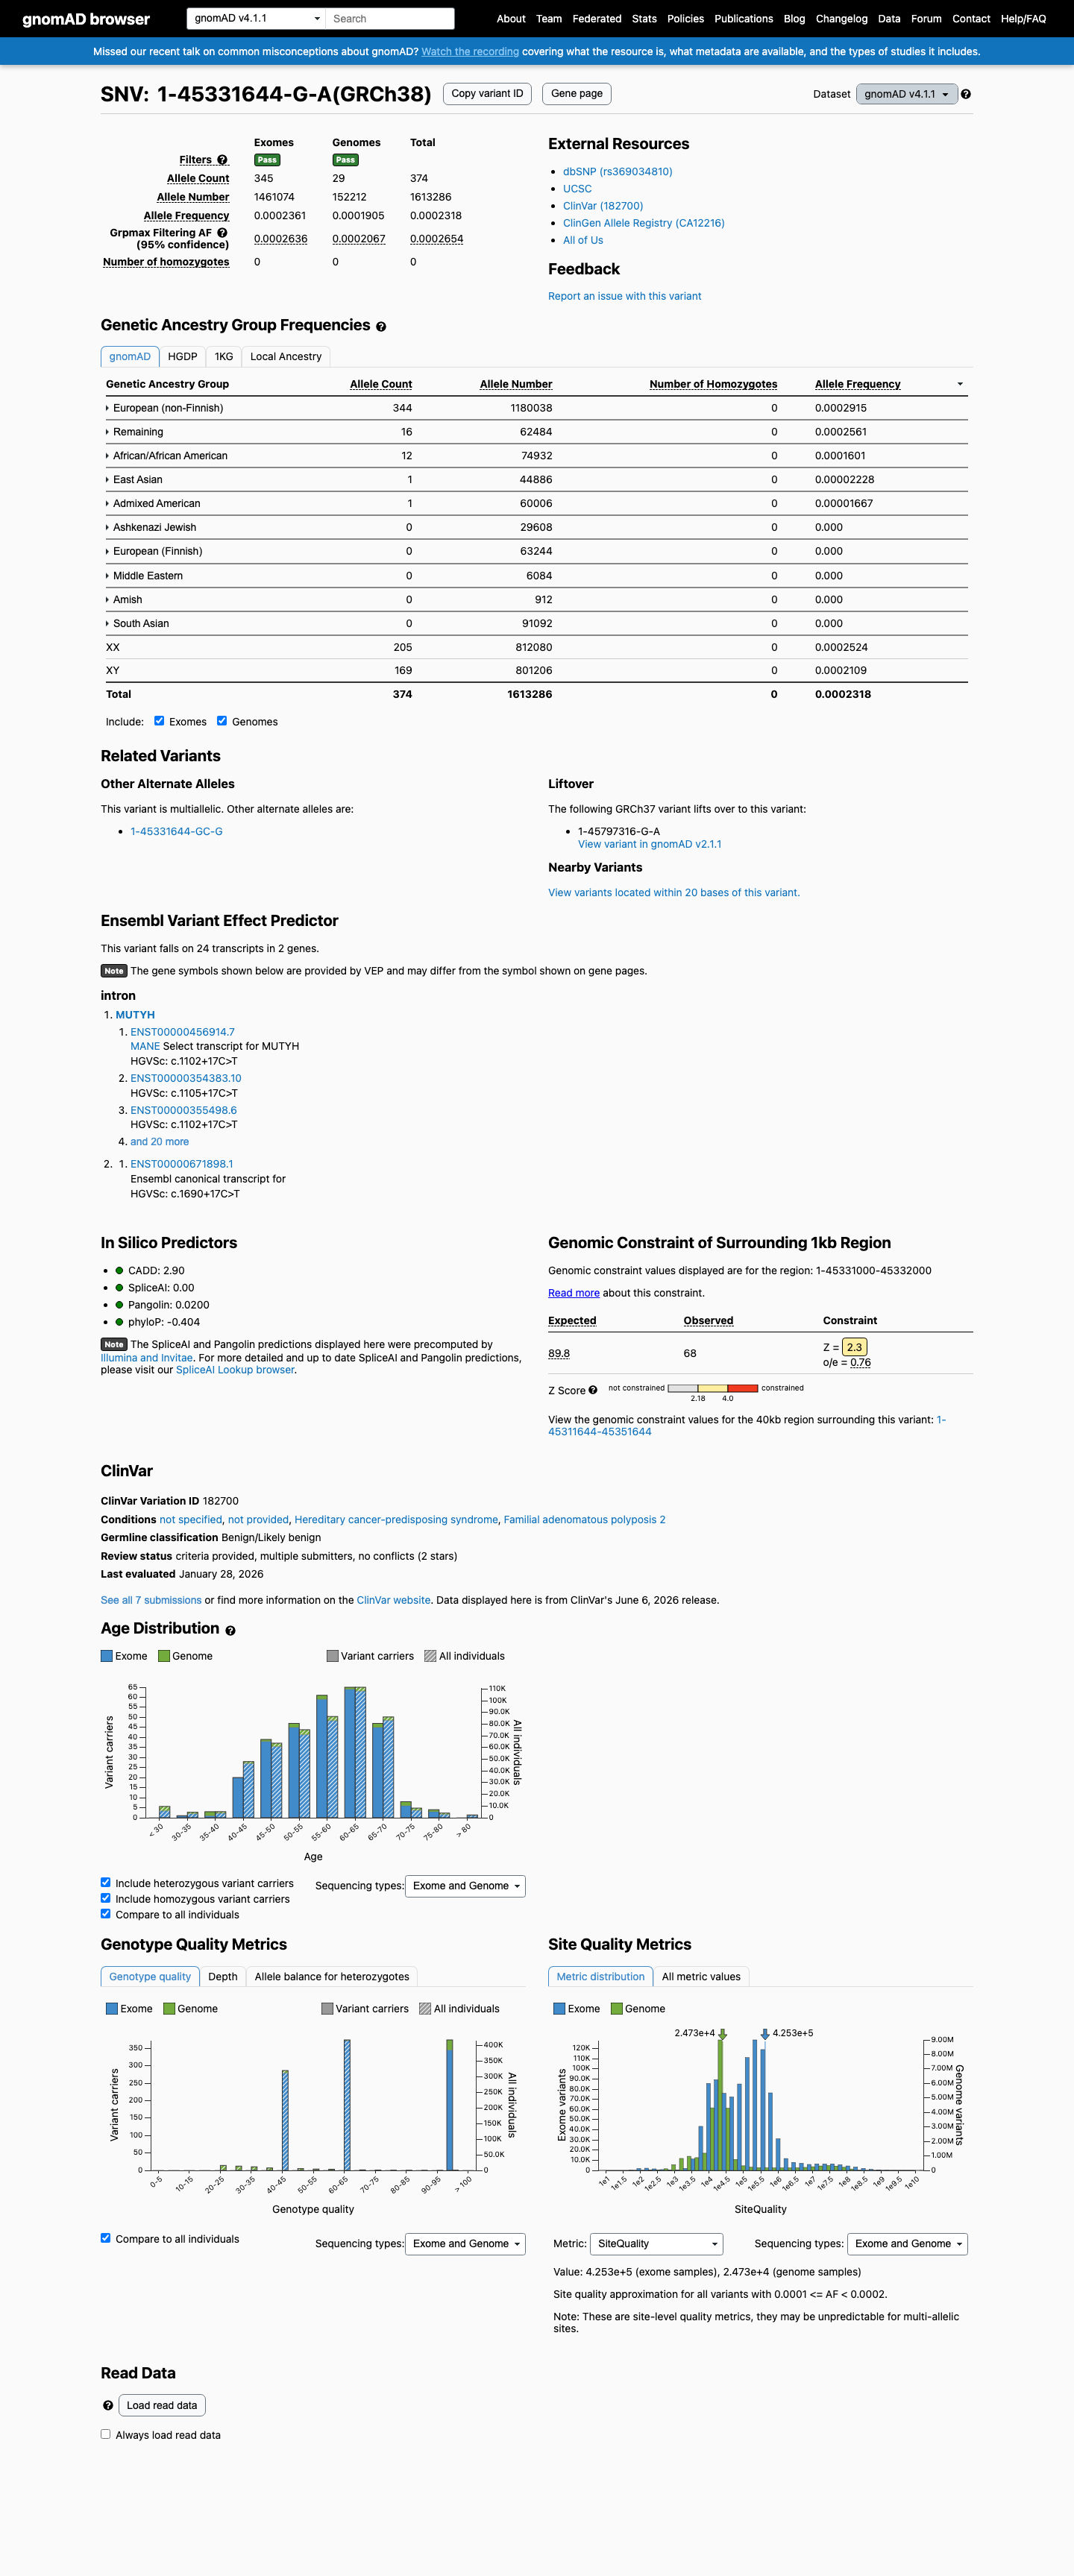
0 hom · FAF 0.027%
European (non-Finnish) 344 / 1,180,038 |
0.029% |
Remaining individuals 16 / 62,484 |
0.026% |
African/African American 12 / 74,932 |
0.016% |
East Asian 1 / 44,886 |
0.0022% |
Admixed American 1 / 60,006 |
0.0017% |
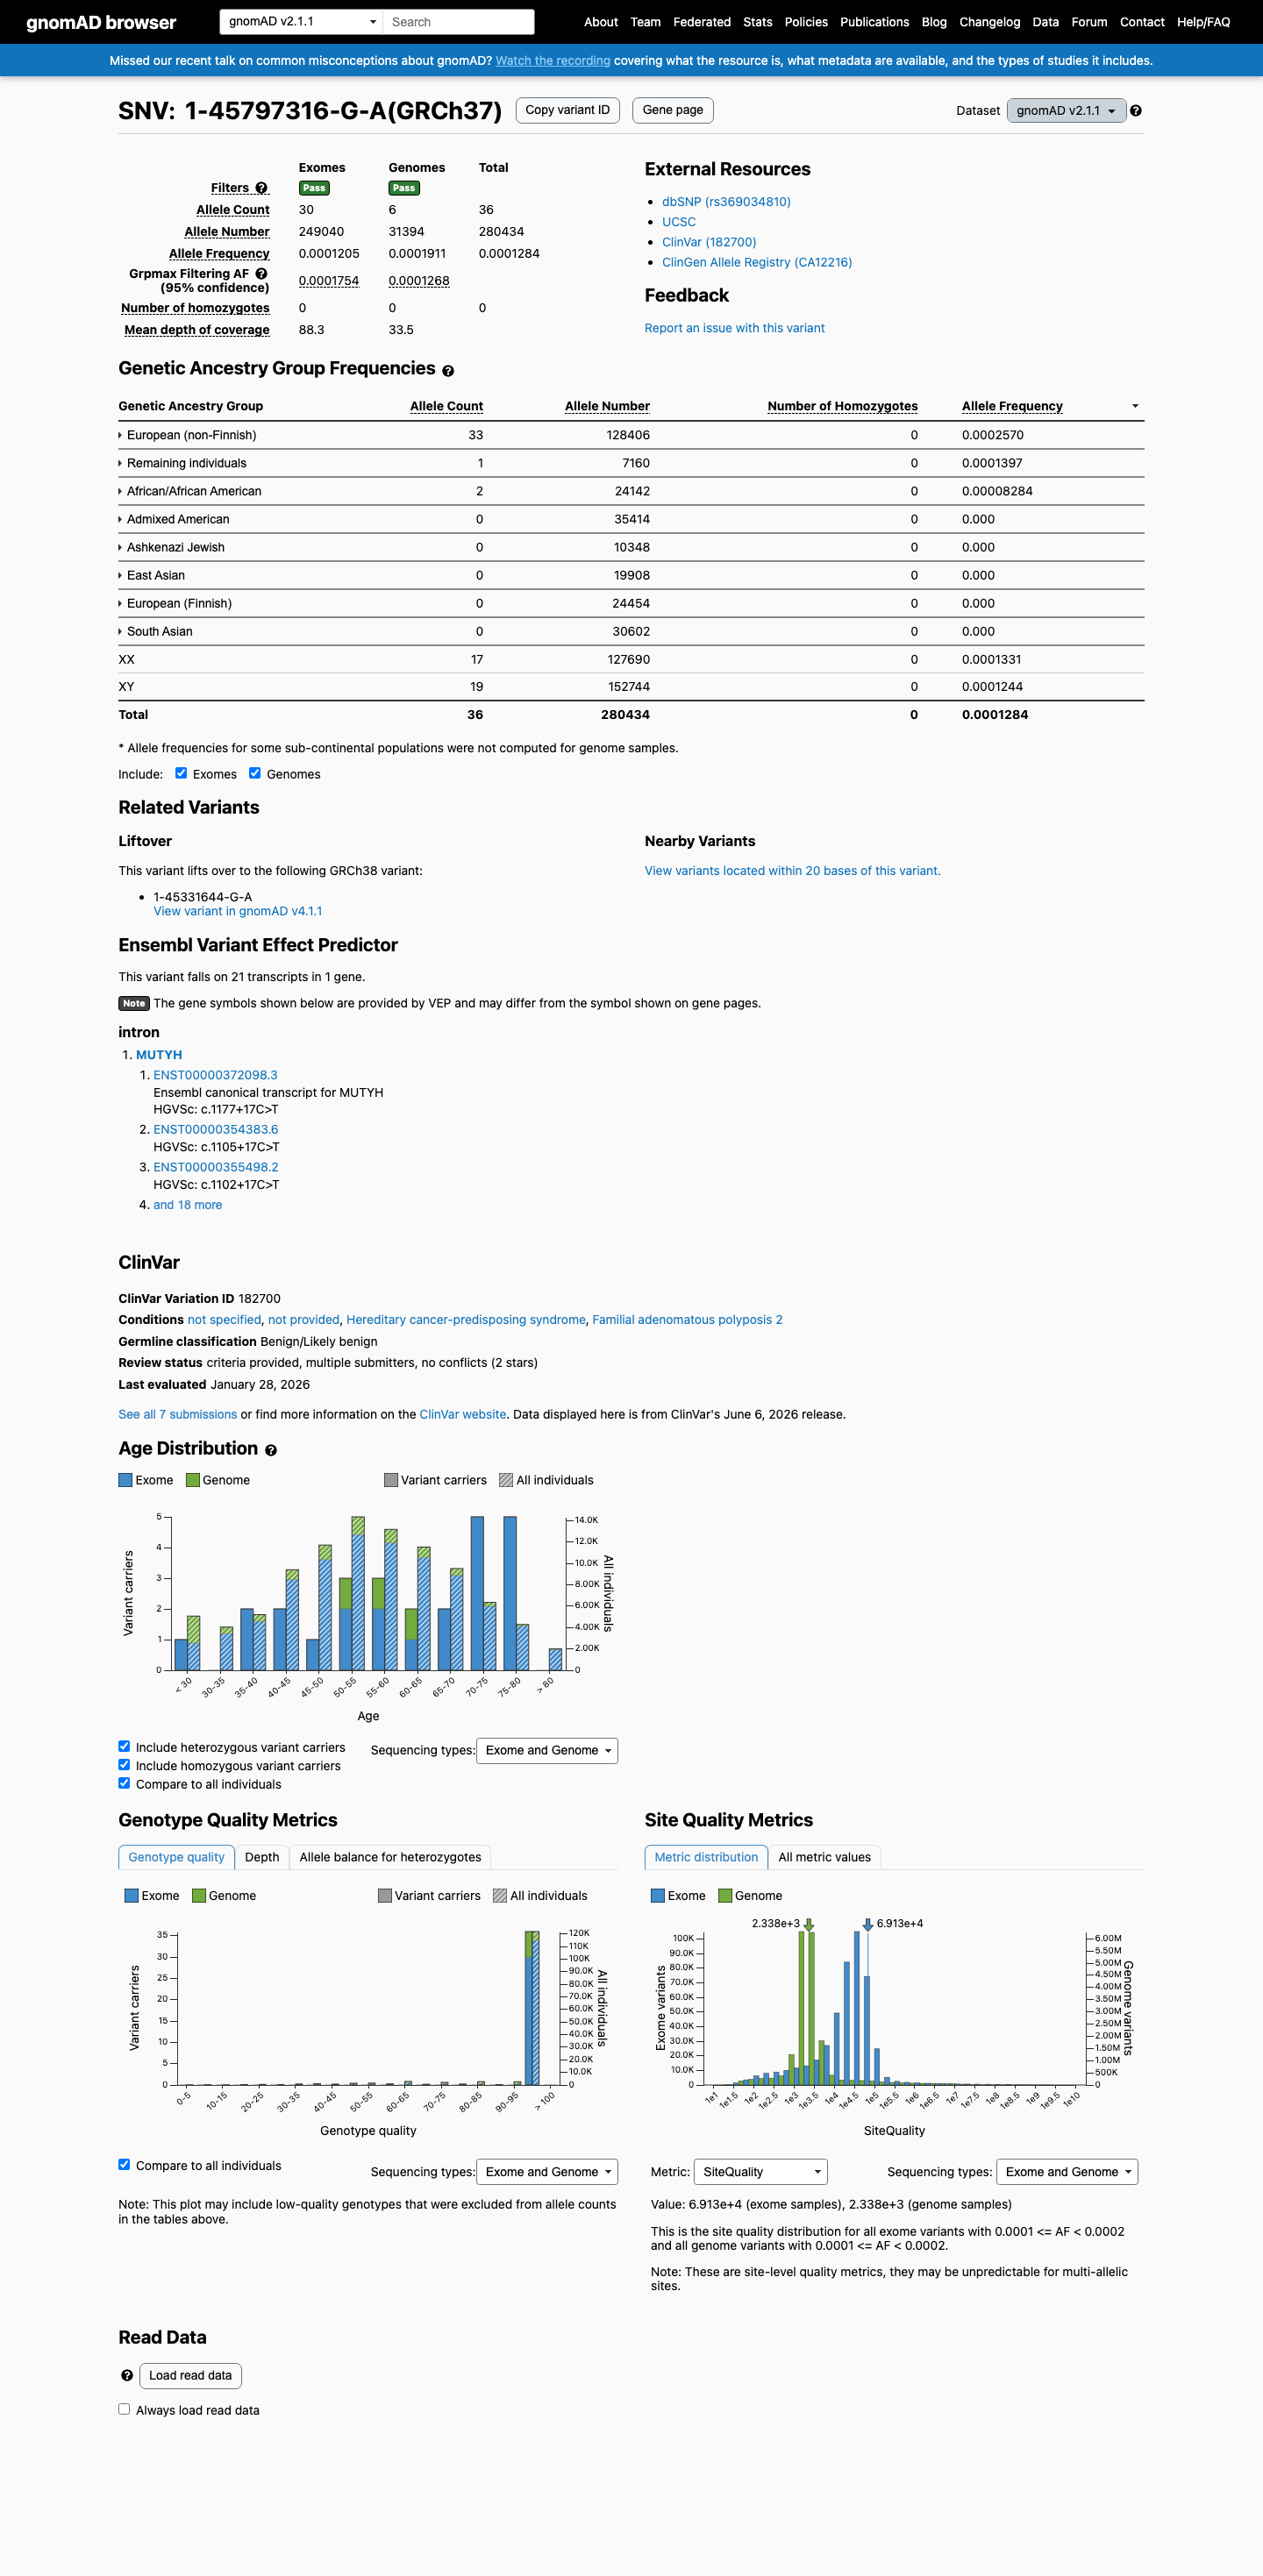
0 hom · FAF 0.018%
European (non-Finnish) 33 / 128,406 |
0.026% |
Remaining individuals 1 / 7,160 |
0.014% |
African/African American 2 / 24,142 |
0.0083% |
0 hom · FAF 0.046%
European (non-Finnish) 10 / 11,730 |
0.085% |