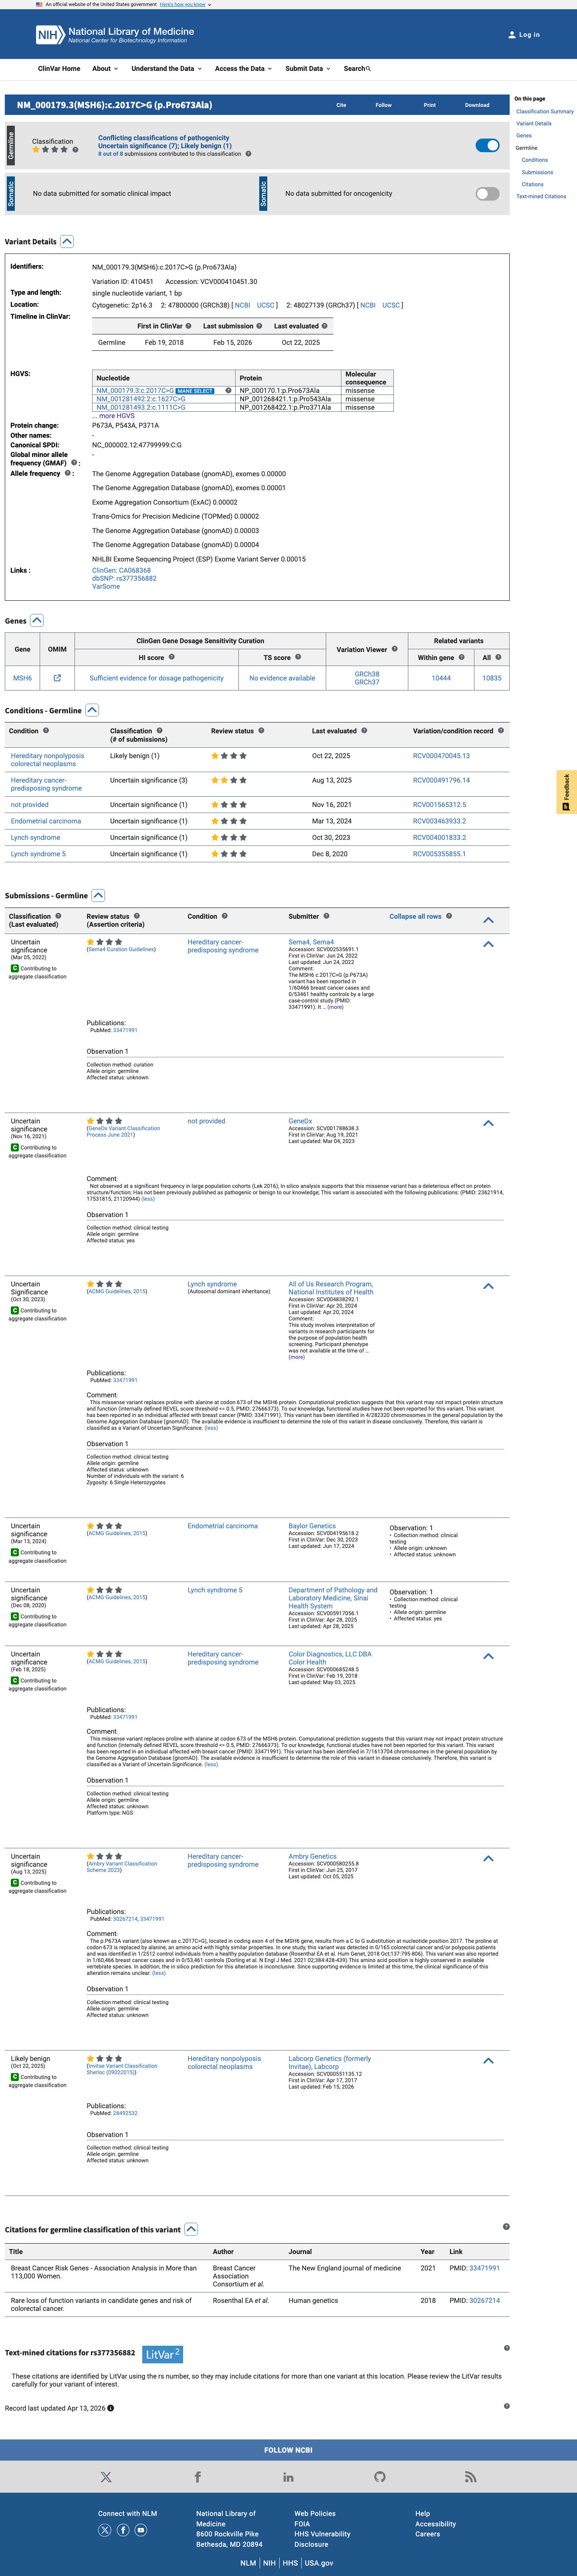
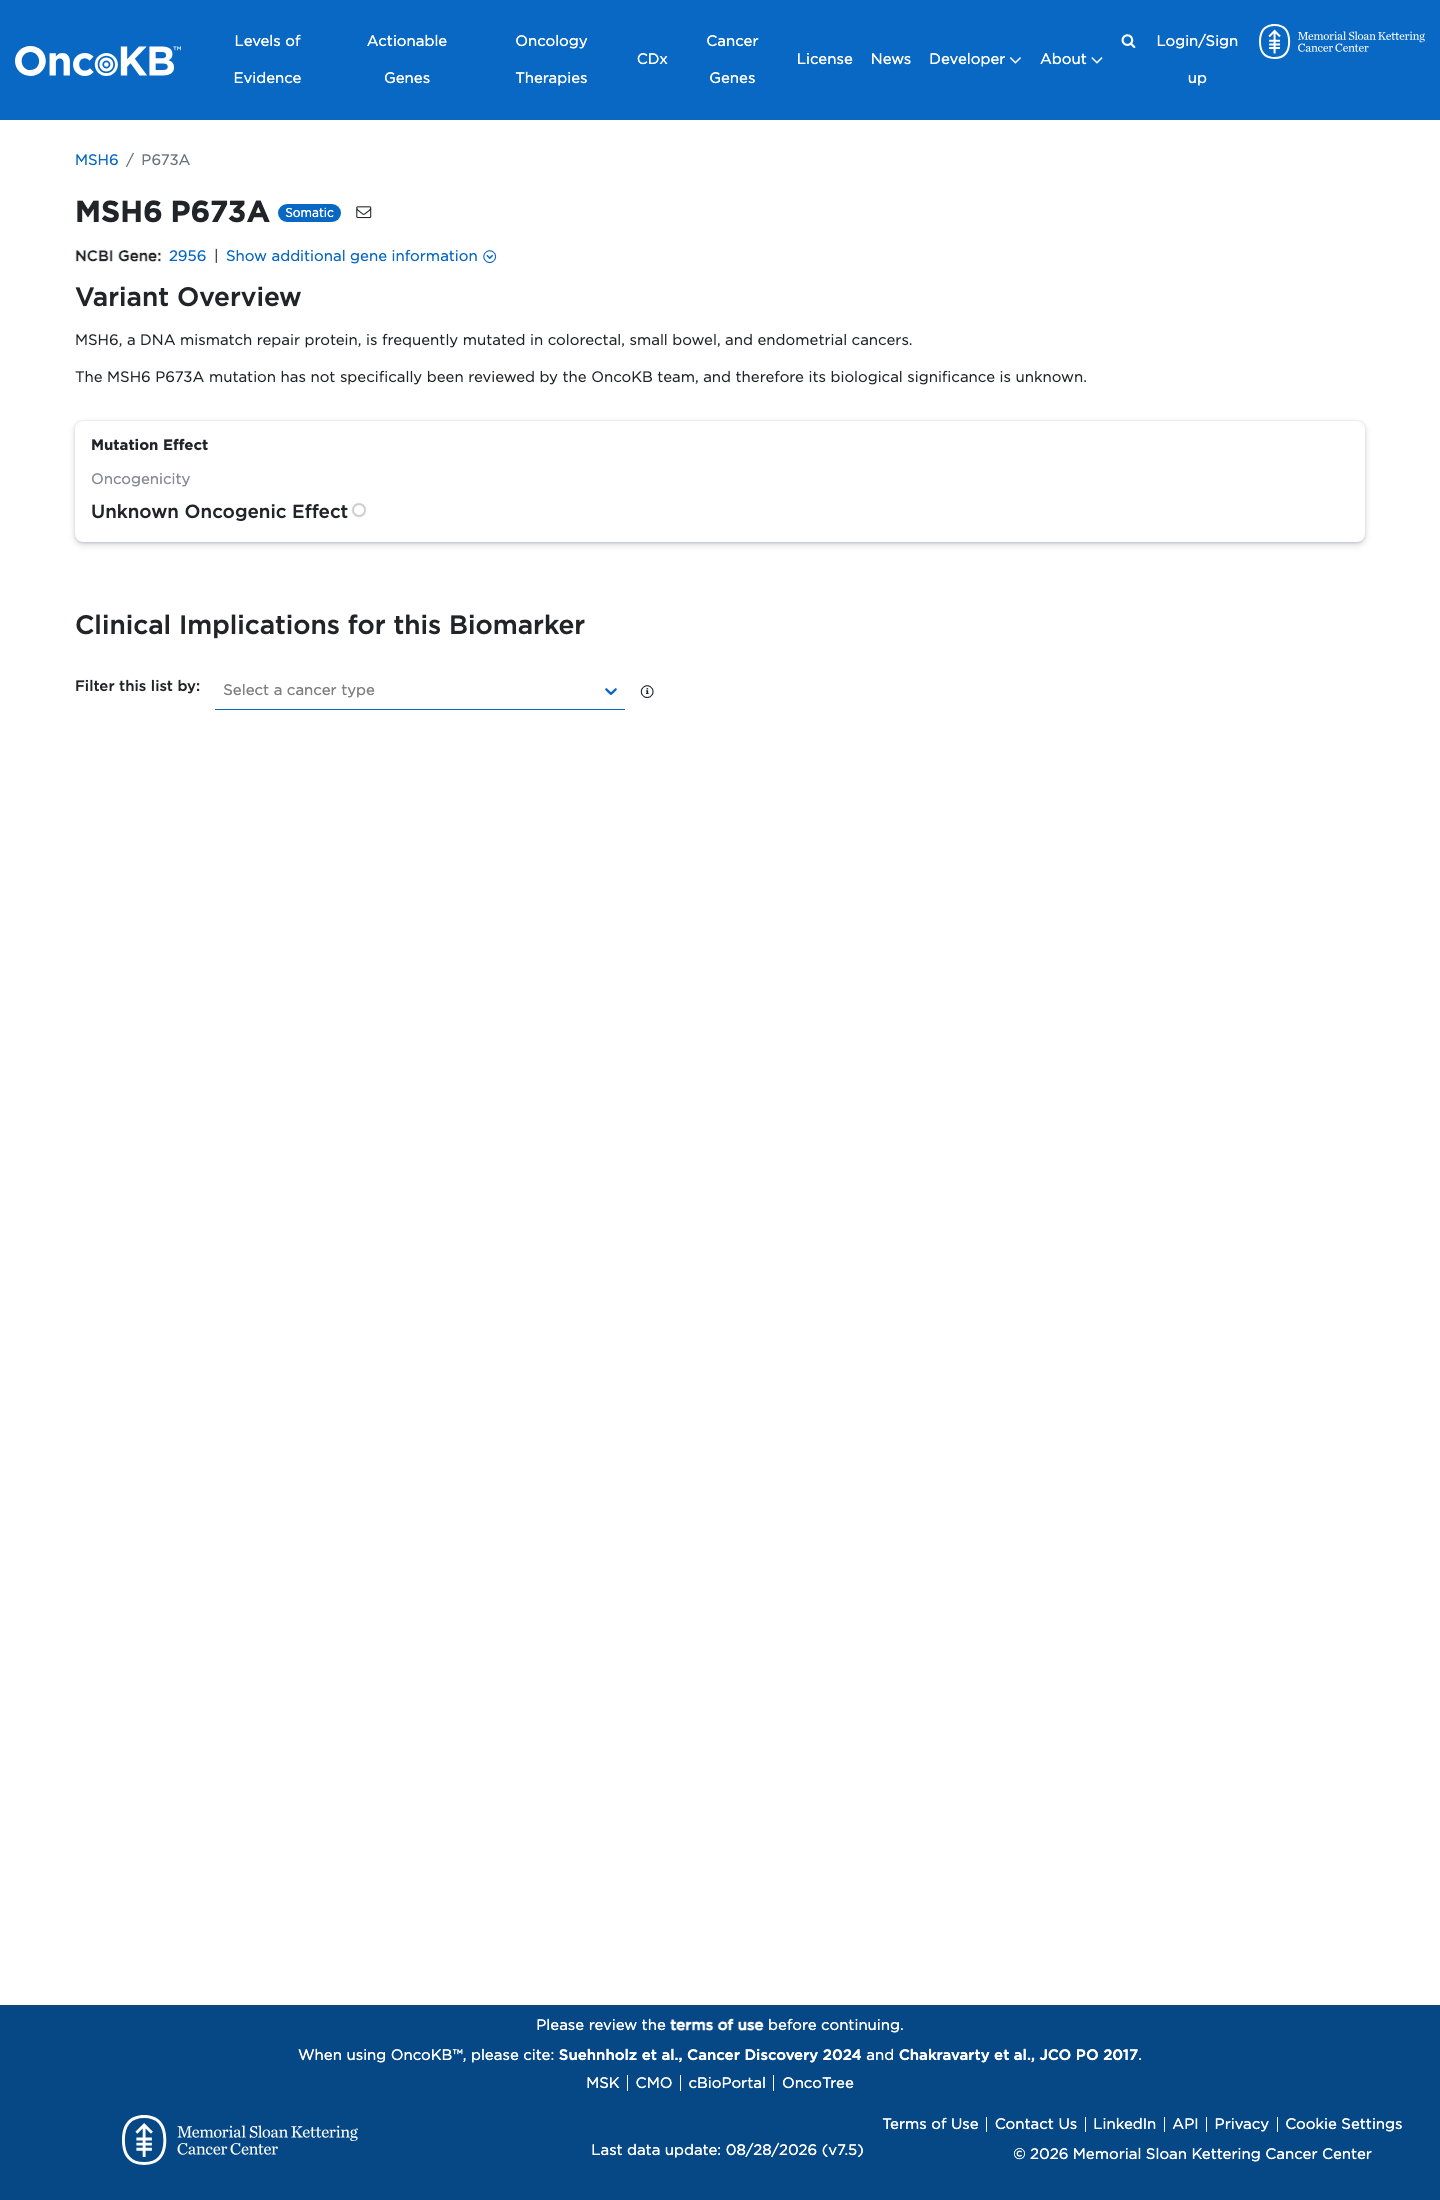
All three consequence/LoF criteria resolve from the variant's own consequence class: NM_000179.3:c.2017C>G is a missense substitution (NP_000170.1:p.(Pro673Ala)) with no protein-length change (mutalyzer start 672 / end 673 unchanged) and no predicted splice effect (SpliceAI max delta 0.014), so the allele is neither a null variant nor an in-frame length-altering variant. PVS1 is therefore not met - no PTC, no frameshift, no large genomic alteration, no IVS+/-1 or +/-2 change, and no mRNA assay evidence of a splicing aberration - and no PVS1 strength tier is assigned (the 'very strong' tier would require a met, un-downgraded null call, which this is not). PM4 and BP3 are not applicable: the governing ClinGen InSiGHT MSH6 VCEP v2.0 explicitly designates both criteria as Not Applicable (protein length change from an in-frame variant not used; in-frame indels in a repetitive region of unknown function not used). This group contributes no pathogenic and no benign evidence; classification of this variant rests entirely on the other evidence groups. None of the five codon/residue/domain criteria contributes pathogenic or benign evidence for NM_000179.3:c.2017C>G (p.Pro673Ala): PS1 and PM5 are not met, and PM1, PP2 and BP1 are designated Not Applicable by the governing InSiGHT MSH6 VCEP specification v2.0. PS1 fails because c.2017C>G is the only codon-673 substitution that encodes alanine (codon 673 is CCG), so no alternate-nucleotide p.Pro673Ala comparator exists, and no codon-673 variant carries a VCEP Pathogenic/Likely Pathogenic classification. PM5 fails on two independent limbs: no VCEP-classified different missense change exists at residue 673, and the VCEP's mandatory PP3 gate is unsatisfied because this variant's HCI prior of 0.0159 falls in the BP4_supporting range (<0.11) rather than above the PP3_supporting threshold (>0.68). The benign direction carried by this group is limited to the observation, relevant only to the VCEP in-silico rules, that the HCI prior of 0.0159 (and REVEL 0.447) sit in the BP4_supporting range; no criterion in this group is met. The segregation/de novo group contributes no scoring evidence for NM_000179.3:c.2017C>G (p.Pro673Ala): PS2 scores 0 de novo points, PP1 is unmet (no pedigree or family genotypes, so no co-segregation Bayes likelihood ratio exists), BS4 is unmet (no informative family, so non-segregation cannot be shown), and PM6 is not applicable in the governing specification. Governing framework is the InSiGHT Hereditary Colorectal Cancer/Polyposis Expert Panel specification for MSH6 v2.0 (CSPEC doc 1578294885): PS2 is a proband-point rule (2 points de novo with confirmed maternity/paternity and MMR-deficient LS-spectrum tumour; 1 point with confirmed maternity/paternity and LS-spectrum tumour; 0.5 points assumed de novo with unconfirmed parentage; >=4 Very Strong, 2-3.5 Strong, 1-1.5 Moderate, 0.5 Supporting), PP1 and BS4 are graded from a combined pedigree Bayes likelihood ratio (PP1 Supporting >2.08, Moderate >4.3, Strong >18.7 in >=2 families; BS4 Strong <0.05, Supporting >0.05-0.48), and PM6 is explicitly not applicable. The absence of evidence is documented rather than assumed: ClinVar variation 410451 contains 8 single-submitter germline submissions (7 Uncertain significance, 1 Likely benign, no expert panel) with no de novo, parental-testing, pedigree or segregation statement, the submission criterion signals are limited to PP3, PS3 and PP4, and none of the seven fetched full texts mentions the variant. This case carries no proband-level clinical record of any kind - no pedigree, no trio or parental genotypes, no family history, no tumour phenotype - so the group's criteria cannot be satisfied by any in-record observation, and the de novo point total (0) and both likelihood-ratio-based criteria (PP1, BS4) remain at their unmet/not-calculable defaults. PM6 non-applicability is a specification decision (MSH6 v2.0 marks PM6 and all of its strength tiers not applicable, folding assumed-de-novo evidence into the PS2 point scale) and must not be carried into the final classification as benign or pathogenic evidence. Framework applied: ClinGen InSiGHT Hereditary Colorectal Cancer/Polyposis Expert Panel specification for MSH6 v2.0 (case framework_mode = vcep; doc_id 1578294885), which is gene-specific and therefore takes precedence over generic ACMG/AMP. Both PS3 and BS3 in that specification are driven exclusively by functional assay data: calibrated functional assays reported as functional odds for pathogenicity, or variant-specific protein/mRNA assay results evaluated through the MMR functional assay flowchart. PS3 is not met and BS3 is not met, for the same reason: no functional assay of any kind has been performed on NM_000179.3:c.2017C>G, p.(Pro673Ala). No calibrated assay result (cell-free or mammalian MMR repair activity, MSH6 protein expression/stability, subcellular localisation, cDNA full-length transcript with and without NMD inhibition) appears anywhere in the case evidence; the VCEP's approved-assay documentation contains no entry for this variant, and the VCEP pilot-variant table does not list it. Independent corroboration of the absence of functional data: two clinical-laboratory ClinVar submissions (All of Us Research Program SCV004838292 and Color Diagnostics SCV000685248) state that functional studies have not been reported for this variant; OncoKB reports no variant-specific reviewed functional evidence; and none of the seven full-text papers retrieved for this case mentions the variant or reports an MSH6 functional assay. SpliceAI max delta 0.014 (no significant splice impact) means the variant cannot be routed into a splicing-based functional path either; the flowchart's missense-without-splice-impact branch requires a calibrated functional assay or two independent concordant assays, and neither was performed. The BS3_Strong synonymous/intronic branch is inapplicable to a missense variant. Deliberate non-use of a superficially attractive number: the local HCI prior for p.P673A is 0.0159 (MAPP/PP2 prior column; Custom_PP2_score 0.409, MAPP 4.34). Numerically this sits below the BS3 functional-odds threshold of <=0.05, but it is an in-silico prior that this VCEP assigns to PP3/BP4 (<0.11 = BP4_Supporting), not a measurement from a calibrated functional assay. Using it for BS3 would double-count a computational prior as functional evidence; the PP3/BP4 consequences are left to the in-silico group. Net functional contribution to this case: zero points in either direction. No other source's final classification was used to reach this conclusion. Three of this group's five criteria (PS4, PP5, BP6) are not applicable: the governing InSiGHT Hereditary Colorectal Cancer/Polyposis MSH6 specification v2.0 disallows them for this gene, and PP5/BP6 additionally have no exact-variant ClinVar expert-panel classification to act on (expert-panel submissions = 0). PP4 (MSI-H tumour phenotype) is applicable but not met: qualifying tumour count 0 versus the Supporting threshold of at least 1 (0 >= 1? No). BP5 (MSS / no-MMR-loss tumour phenotype) is applicable but not met: qualifying tumour count 0 versus the Supporting threshold of 2 or 3 (0 >= 2? No). Net contribution of this group to the final classification is zero: no tumour MSI/IHC, BRAF V600E or MLH1 methylation data exist for MSH6 c.2017C>G (p.Pro673Ala), so neither the pathogenic (PS4/PP4) nor the benign (BP5/BP6) side of this group supplies evidence. This group contributes no scoring evidence: PM3 scores 0 points because the InSiGHT MSH6 v2.0 co-occurrence rule (second pathogenic MSH6 variant in a CMMRD-consistent patient, 1.0 point in trans or 0.5 points phase-unknown) has no qualifying observation for c.2017C>G, and BP2 is not applicable in this gene-disease specification, which uses BS2 instead. Allelic evidence is uniformly absent rather than merely unreported: the variant is reported only as a heterozygous germline finding in Lynch-syndrome-spectrum testing (7 ClinVar submissions Uncertain significance, 1 Likely benign, no expert panel), no submitter or publication describes a second MSH6 variant, phase, or a biallelic/CMMRD case, and gnomAD v4.1 shows 7/1,613,704 alleles with zero homozygotes. Because the variant's known clinical use is heterozygous in a dominant cancer-predisposition context, this group cannot supply pathogenic or benign weight from trans/cis configuration; any such weight would have to come from a CMMRD-setting co-occurrence observation that does not currently exist. Consequence type fixed the single predictor path: c.2017C>G is a missense substitution (NP_000170.1:p.(Pro673Ala), MSH6 exon 4), so PP3/BP4 were evaluated on the protein-impact path only; the SpliceAI splice path and BP7 were excluded upstream by scope, not because evidence was missing or unresolved. The governing ClinGen InSiGHT MSH6 VCEP specification (v2.0) replaces generic REVEL calibration for missense variants with the HCI prior probability of pathogenicity: >0.81 = PP3_Moderate, >0.68-0.81 = PP3_Supporting, <0.11 = BP4_Supporting. The declared local VCEP lookup HCI-PRIORS-MSH6.txt was searched under all three notations of this variant (c.2017C>G, p.Pro673Ala, p.P673A) and contains the exact row at line 4413 (dbid MSH6_04411) with prior probability 0.0159; this yields PP3 not_met and BP4 met at supporting strength, the strength the VCEP assigns to BP4 by default. The single HCI prior value (0.0159) supports exactly one criterion: it falls below 0.11 (BP4) and below 0.68 (PP3), so no prediction is double-counted across PP3/BP4, and BP7 is not applicable to a missense variant. Generic calibration was used only as a non-governing cross-check: REVEL 0.447 is in the indeterminate zone (0.29-0.644, PMID:36413997) and would give neither PP3 nor BP4 on its own; the SpliceAI delta of 0.014 was not used for either missense criterion, and no other source's final classification (ClinVar Uncertain significance, OncoKB unknown) was inferred into any criterion. Population group result under the governing ClinGen InSiGHT MSH6 v2.0 specification: BA1 not met, BS1 not met, BS2 not met, PM2 met at Supporting. The variant is genuinely rare rather than absent: gnomAD v4.1 records 7 alleles in 1,613,704 (total AF 4.337846e-06; Grpmax filtering AF 1.83e-06) with 0 homozygotes, which clears the VCEP's PM2 cutoff of <0.00002 but falls three orders of magnitude short of the VCEP's BS1 (0.00022) and BA1 (0.0022) thresholds, so no benign population-frequency evidence is generated. No gnomAD iteration or ancestry group approaches a benign threshold: maxima available are Grpmax filtering AF 2.849e-05 (v3.1 non-cancer genomes, European non-Finnish driven) and subpopulation AF 7.725110e-05 (European non-Finnish, v3.1 non-cancer genomes), both far below the VCEP BS1 floor of 0.00022; gnomAD v2.1, gnomAD v2.1 non-cancer exomes and gnomAD-Canada provide nothing higher (gnomAD-Canada: absent). Zero homozygotes were observed in every population dataset for this variant, so there is no population observation supporting BS2 (no healthy homozygous adult) or, conversely, any biallelic/CMMRD-type signal. Net contribution of this group to the final classification: one pathogenic criterion at Supporting strength (PM2_Supporting) and no benign criteria; the founder-pathogenic-variant exclusion clause attached to BA1/BS1 is moot because neither frequency threshold is approached. Source-selection sensitivity is limited and does not change any verdict: whether the VCEP-specified gnomAD v4 all-comers figures, the v2.1 (all-comers or non-cancer exome) figures, or the v3.1 non-cancer genome figures are used, BA1 and BS1 are not met; only PM2 is sensitive to source choice, and the VCEP explicitly names the gnomAD v4 dataset, which yields 1.83e-06 and therefore meets it.
MSH6 encodes a protein in the DNA mismatch repair system, which fixes errors made during DNA replication. Partnering with MSH2, it forms a complex that recognizes and helps correct mismatched DNA bases, keeping the genetic code stable. Inherited mutations in MSH6 cause Lynch syndrome (hereditary nonpolyposis colorectal cancer), raising the risk of colorectal, endometrial, ovarian, and other cancers, while mutations in both copies lead to constitutional mismatch repair deficiency. Because faulty mismatch repair drives tumor development and produces microsatellite instability, MSH6 acts as a tumor suppressor, and cancers with such repair defects often respond well to immune checkpoint inhibitor therapy.
All three consequence/LoF criteria resolve from the variant's own consequence class: NM_000179.3:c.2017C>G is a missense substitution (NP_000170.1:p.(Pro673Ala)) with no protein-length change (mutalyzer start 672 / end 673 unchanged) and no predicted splice effect (SpliceAI max delta 0.014), so the allele is neither a null variant nor an in-frame length-altering variant.
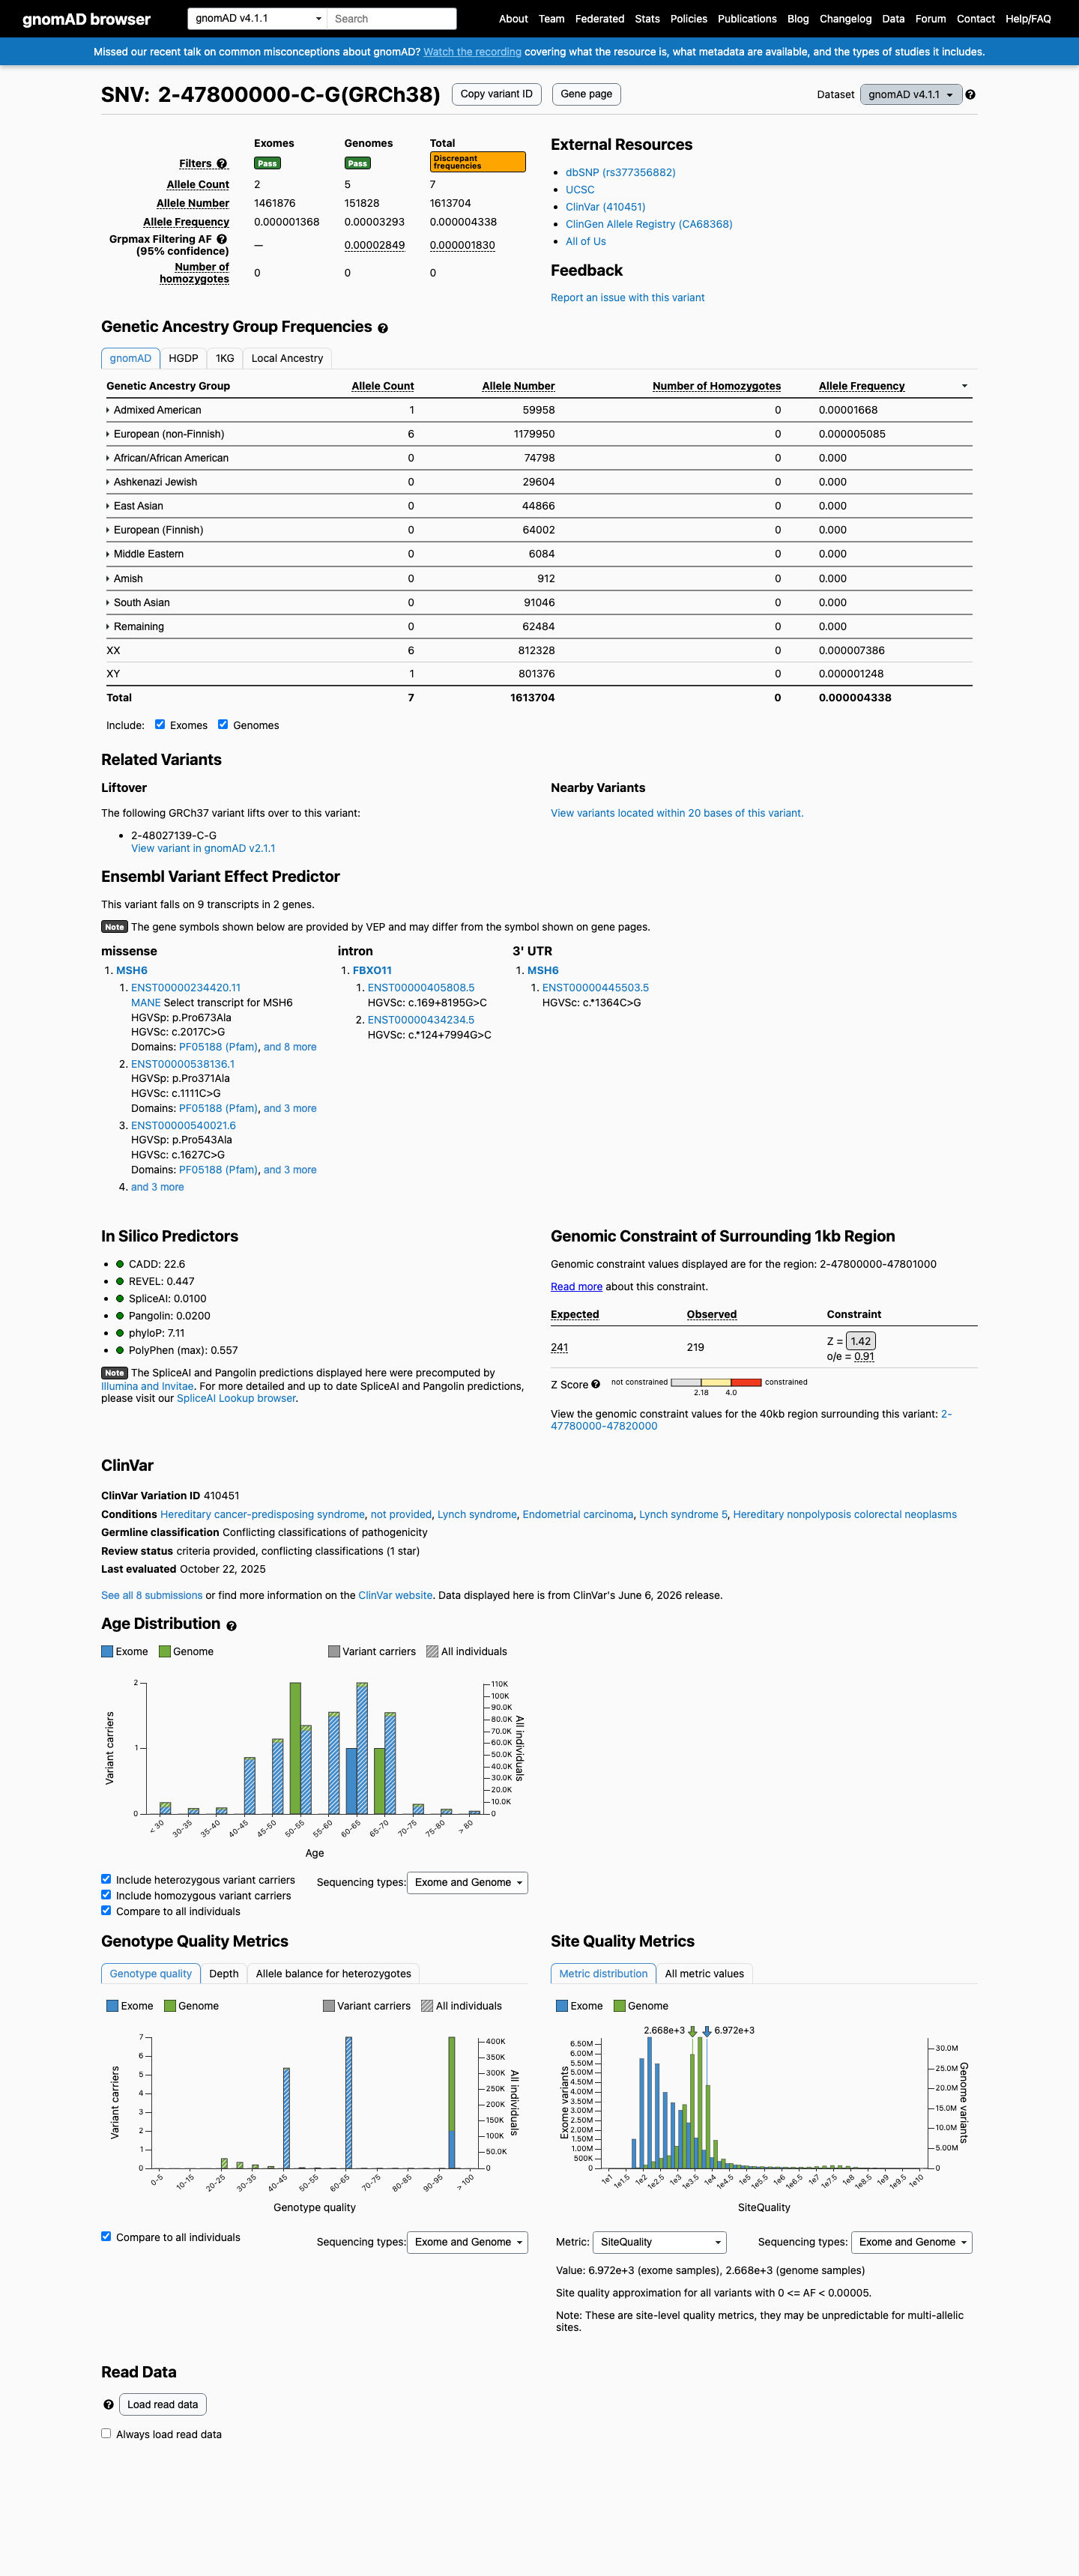
0 hom · FAF 0.00018%
Admixed American 1 / 59,958 |
0.0017% |
European (non-Finnish) 6 / 1,179,950 |
0.00051% |
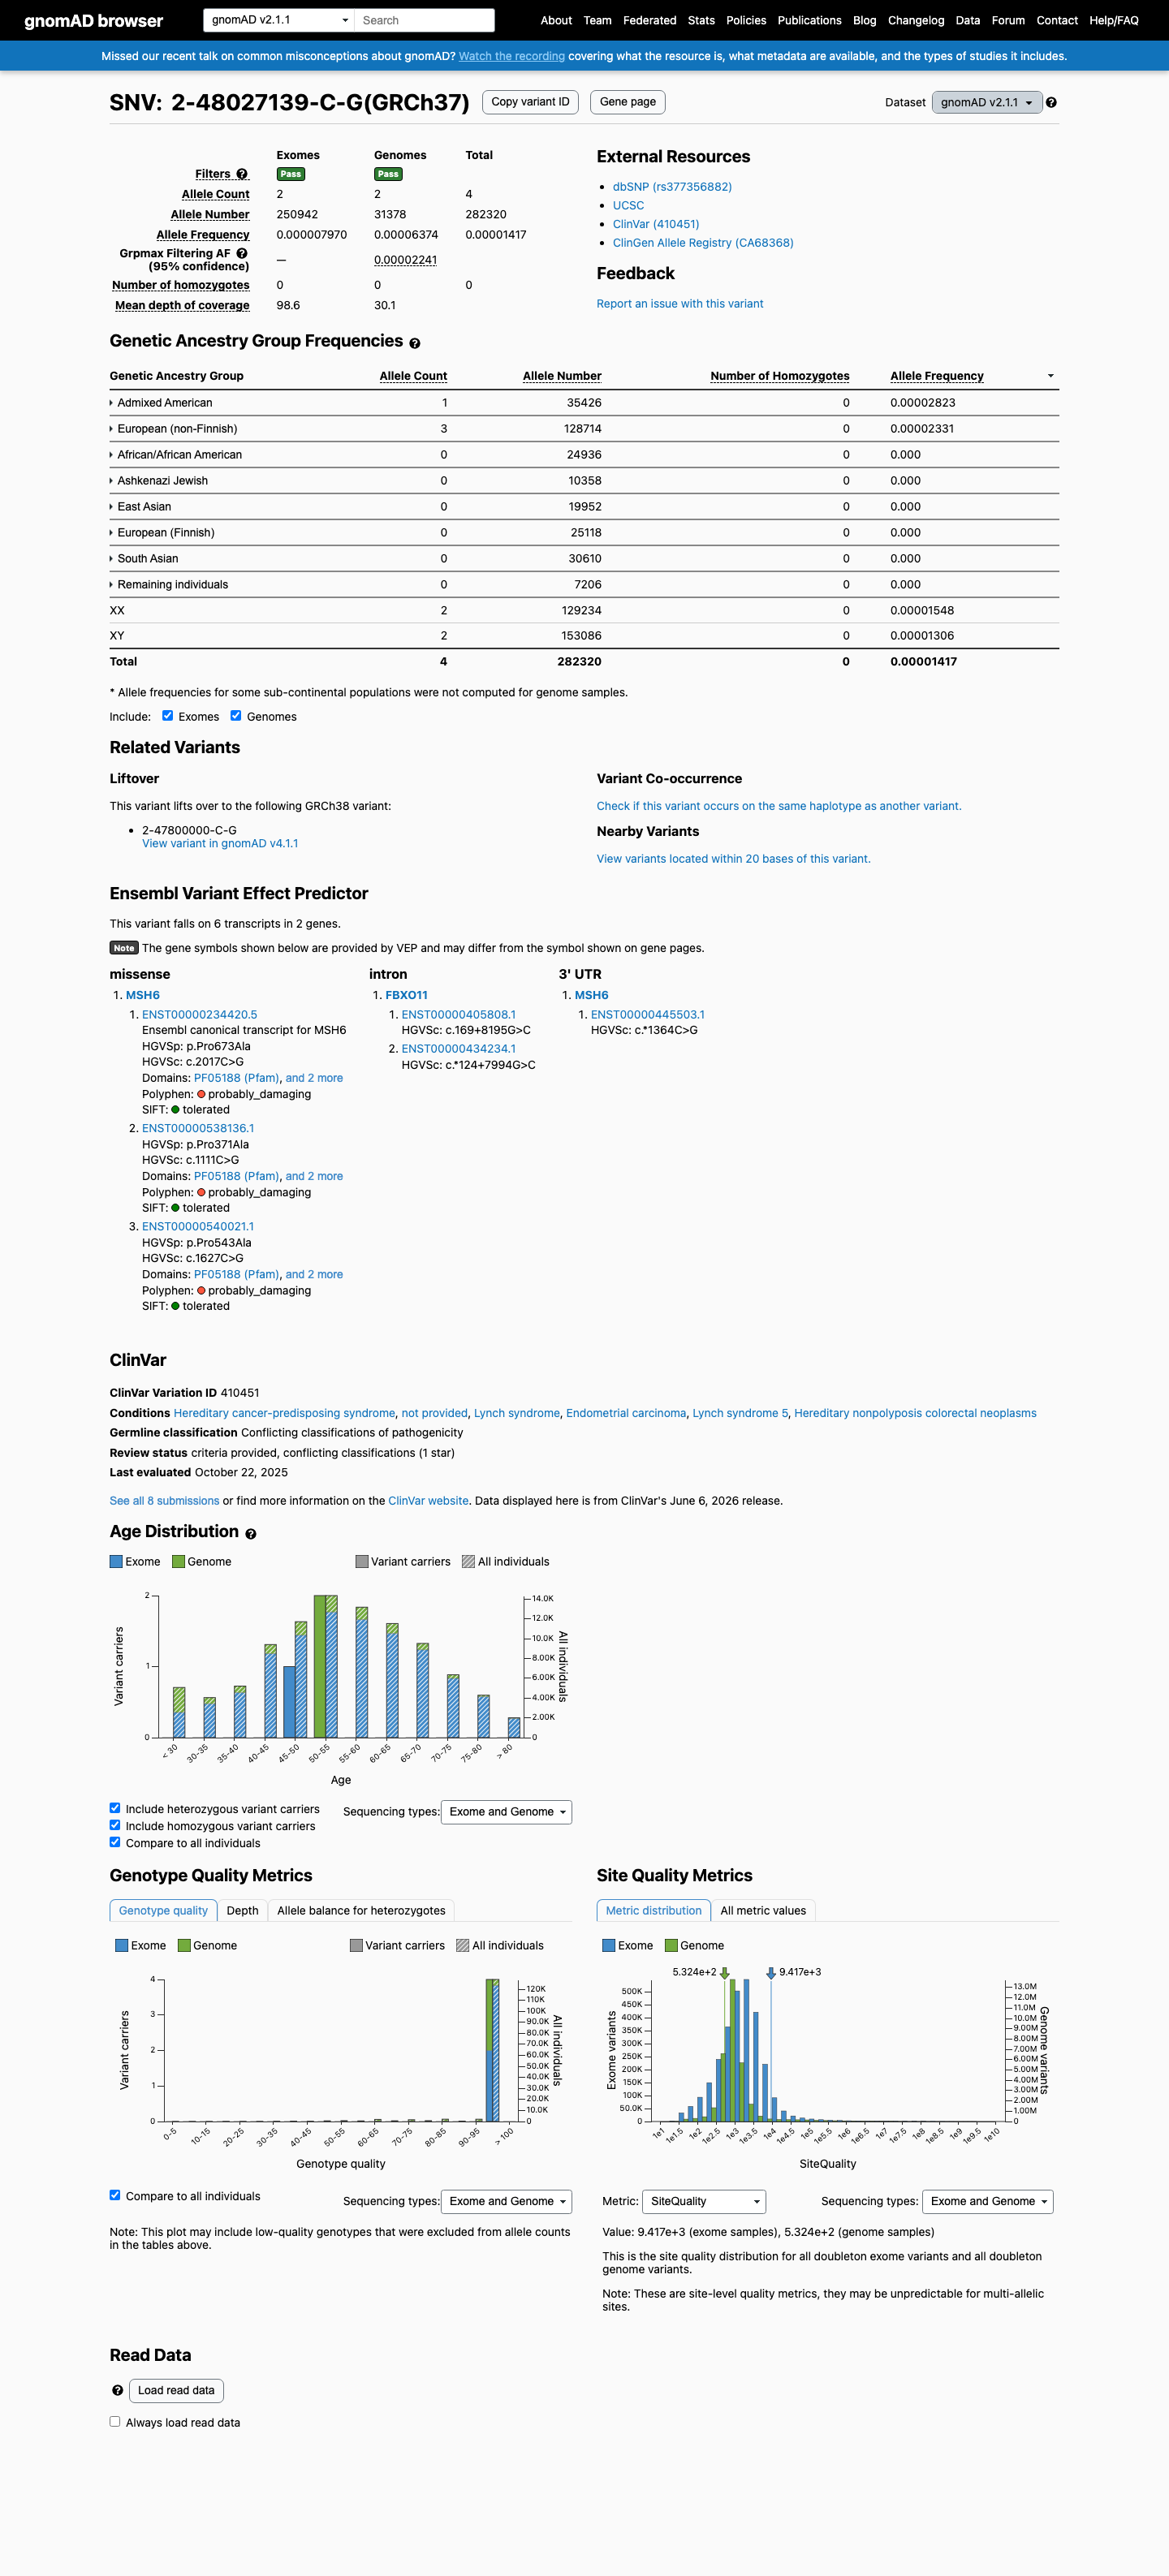
0 hom · FAF 0.0022%
Admixed American 1 / 35,426 |
0.0028% |
European (non-Finnish) 3 / 128,714 |
0.0023% |
0 hom