PMS2 is a DNA mismatch-repair protein that works with MLH1 to correct replication errors, including mismatches and small insertion or deletion loops. It acts as a tumor suppressor, and inherited loss of PMS2 function can cause Lynch syndrome and constitutional mismatch repair deficiency, increasing the risk of colorectal, endometrial, ovarian, urothelial, and other cancers. Loss of PMS2 function in tumors can cause hypermutation and microsatellite instability, which may make some cancers responsive to certain immunotherapies.
This variant
This PMS2 intronic variant is evaluated in the context of PMS2 mismatch-repair activity with MLH1, whose inherited loss of function causes Lynch syndrome and constitutional mismatch repair deficiency.
Transcript
NM_000535.7
HGVS · transcript:coding
NM_000535.7:c.1145-11C>T
GRCh38
chr7:5987631 G>A
GRCh37
chr7:6027262 G>A
Likely Benign: BS1 (strong) plus BP7 (supporting) satisfy the ClinGen InSiGHT PMS2 Version 2.0 Rule18; PP3 is also supporting.
Classification rationale
PP3BS1BP7Likely Benign
PMS2 c.1145-11C>Tunknown · exon 10i
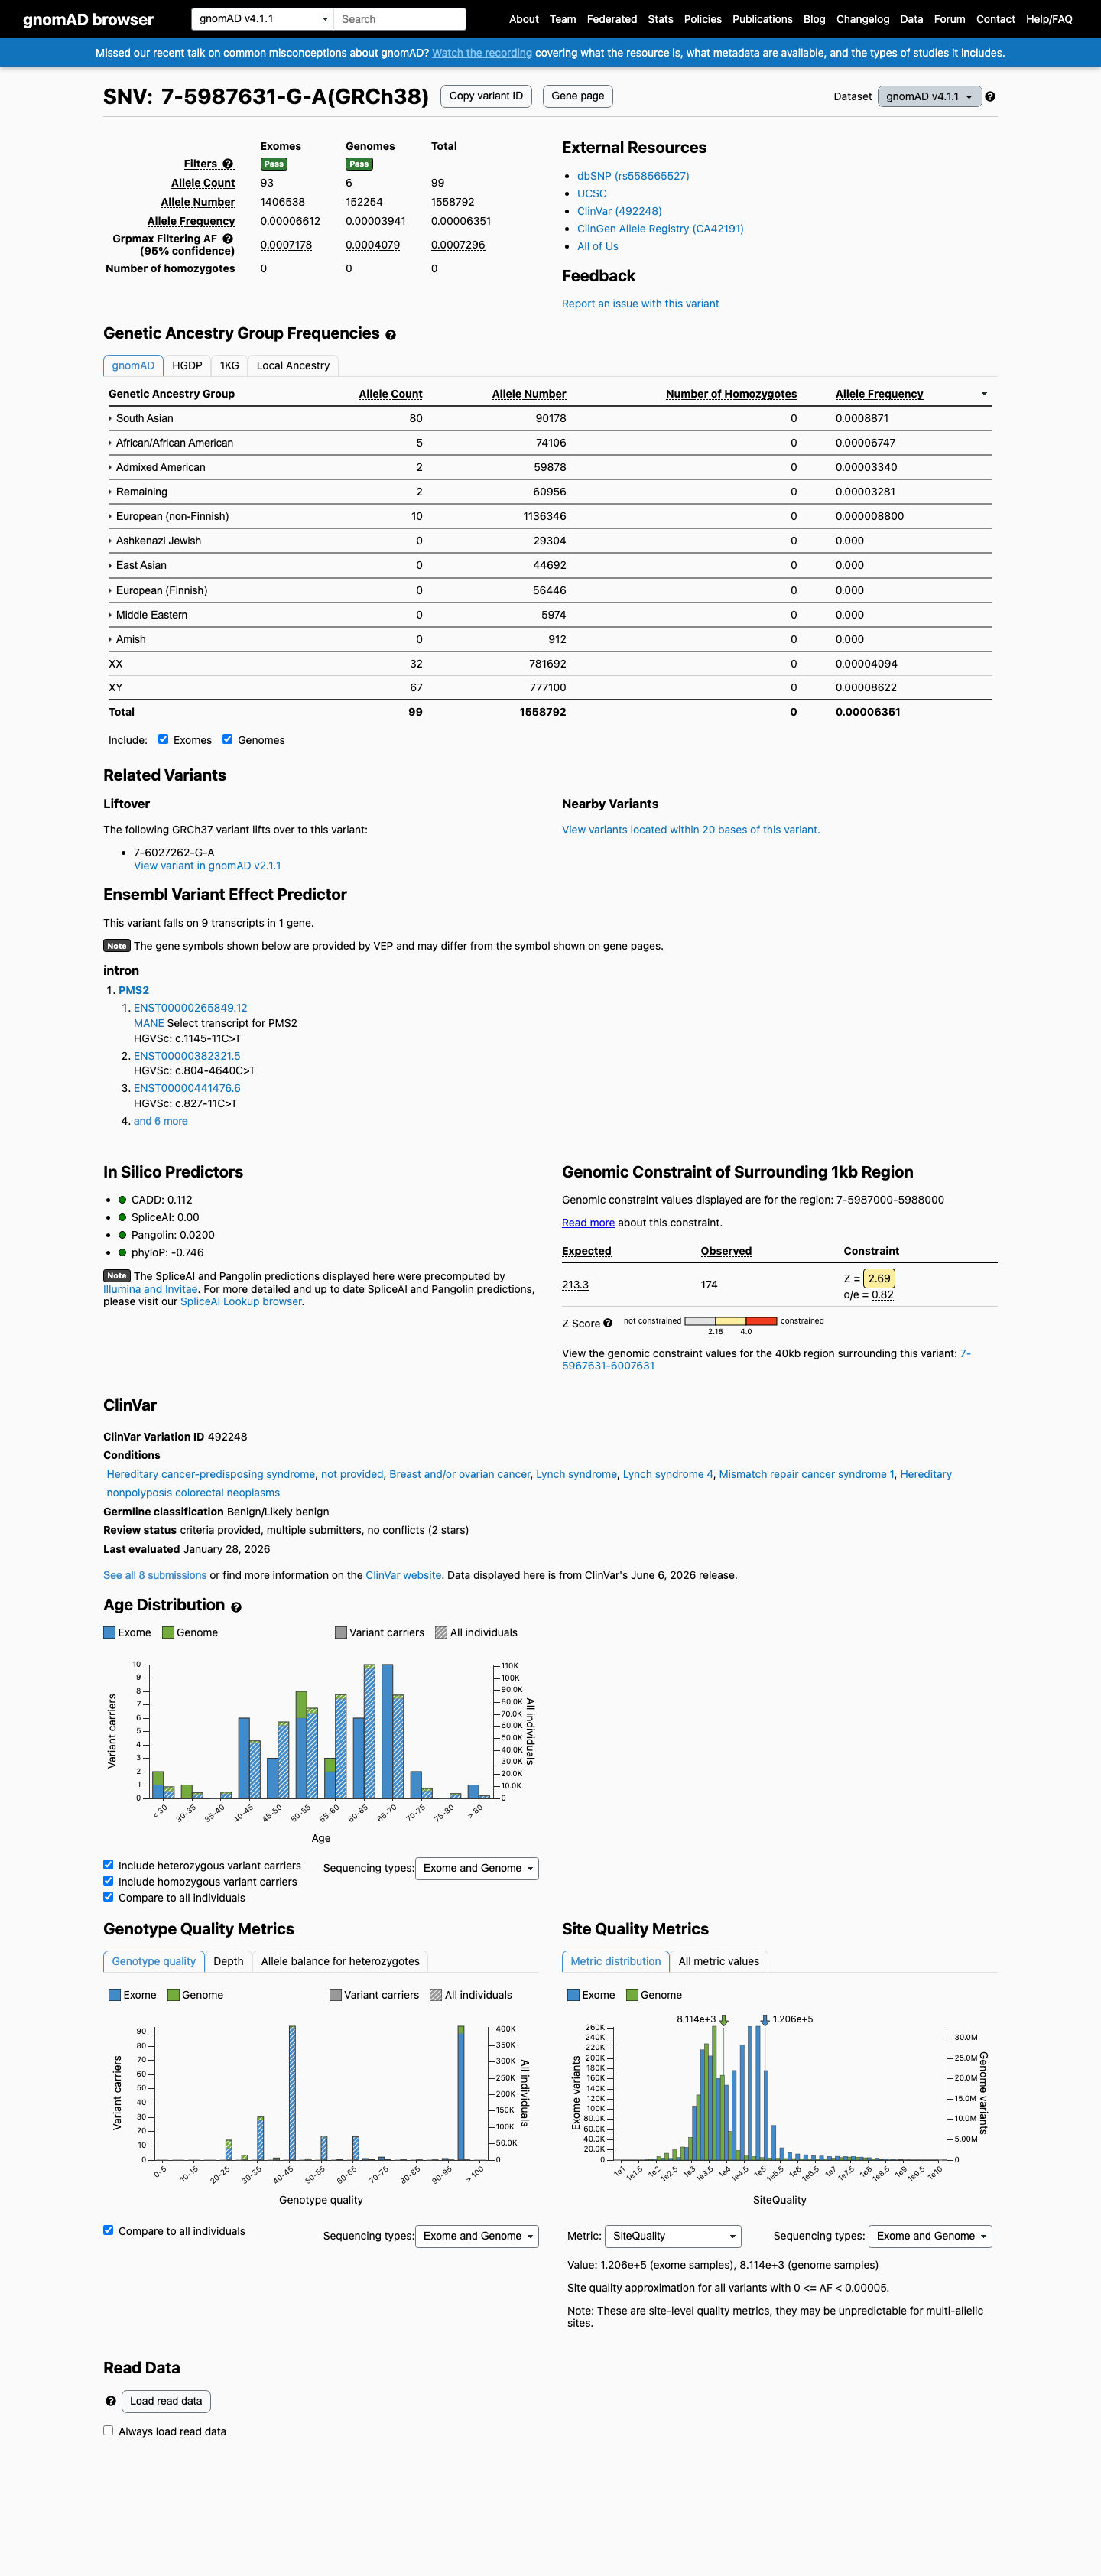
Likely Benign: PP3 (supporting) is met because SpliceAI max delta 0.213 meets the PMS2 non-canonical splice threshold. Likely Benign: BS1 (strong) is met because gnomAD v4.1 Grpmax FAF 0.00072958 falls within the PMS2 BS1 interval. Likely Benign: BP7 (supporting) is met because the intronic position -11 lies within the PMS2 VCEP BP7 range.
PP3 + BS1 + BP7→Likely Benign
LYFE Sciences is an AI system, and it can make mistakes. Criteria
may be applied incorrectly, sources may be misread, and a confident-looking
classification can still be wrong. Double-check every criterion and
its underlying evidence before relying on any call.
Gene diagram
· NM_000535.7 · variants mapped to exon structure
PMS2NM_000535.7
Fetching transcript structure from UCSC…
Exons
—
Transcript span
—
Strand
—
Variants mapped
—
Source
UCSC ncbiRefSeqCurated
All variants in PMS2—click a row to locate it on the plot · use the link column to open its page
Protein
Location
Classification
Link
Applied criteria · 3 applied · 14 assessed
MetEvidence satisfies this criterion.
Not metEvaluated against available evidence; threshold not reached.
Not assessedApplies in principle, but no evidence was found to evaluate it.
N/ADoesn't apply to this variant type.
Applied · 3
Strength Supporting Moderate Strong Very strong
✓
PP3supportingPathogenic
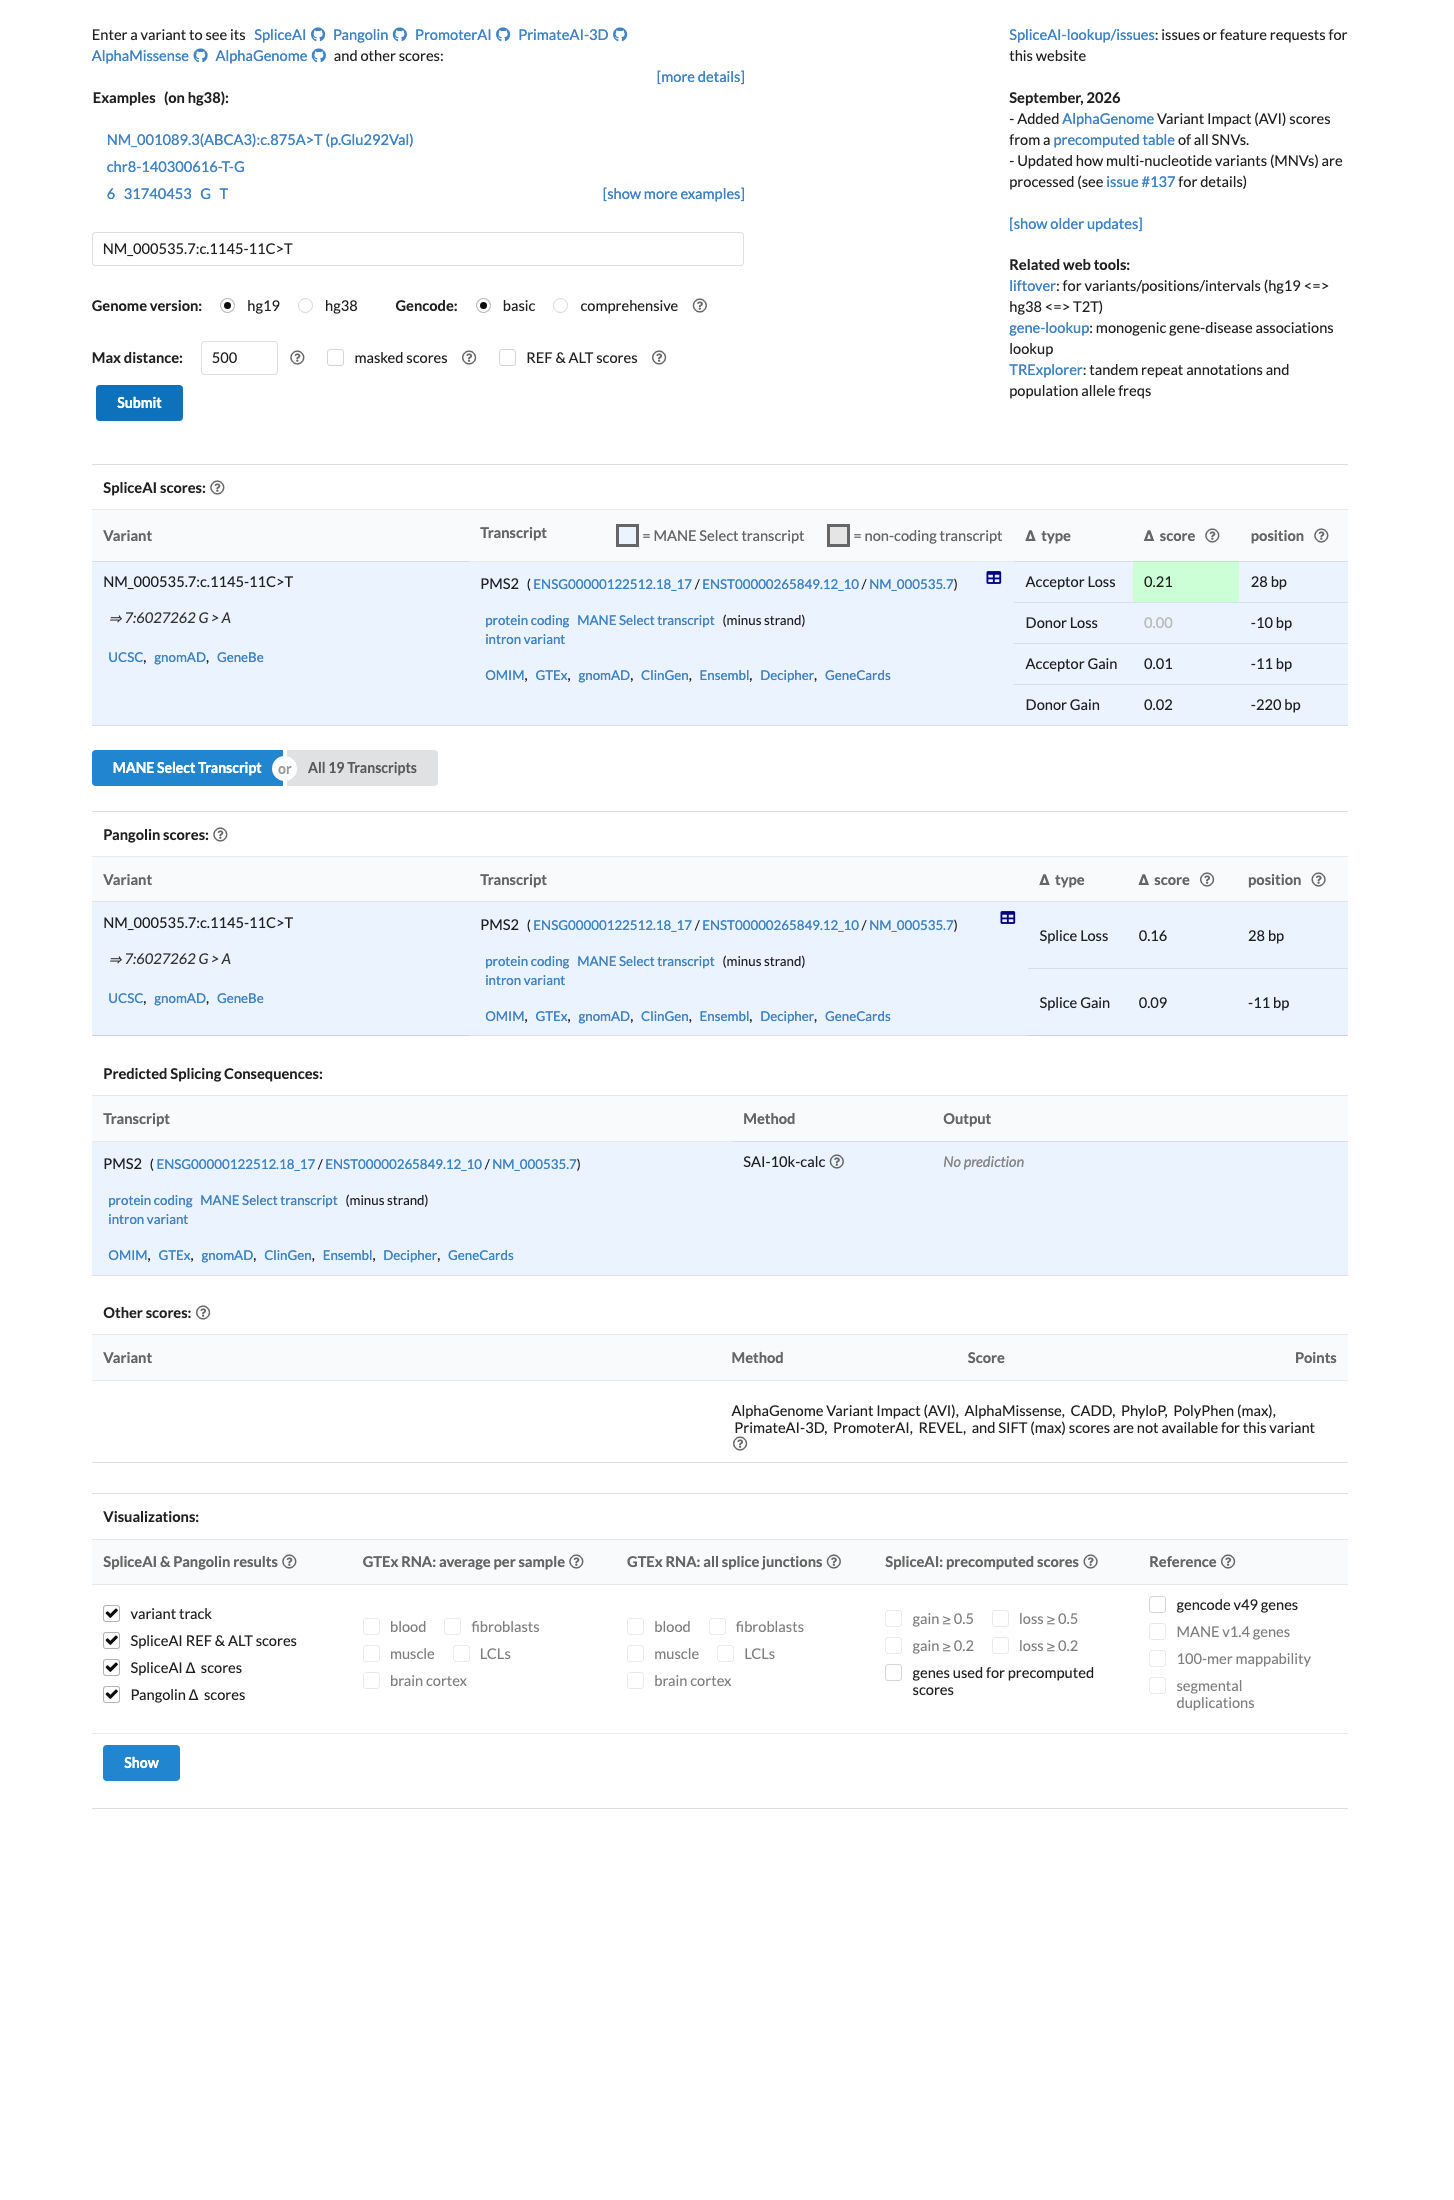
Met at Supporting: SpliceAI max delta 0.213 meets the PMS2 VCEP non-canonical splice threshold of >=0.2.
The PMS2 VCEP specification states that PP3_Supporting applies to a predicted splice defect at a non-canonical splice nucleotide when SpliceAI delta score is >= 0.2.SpliceAI reports DS_AL 0.213 as the maximum delta score for NM_000535.7:c.1145-11C>T, with the predicted acceptor-loss event at a non-canonical intronic position.The indexed HCI-PRIORS-PMS2.txt.txt file is a missense-only lookup table and was searched under c.1145-11C>T, p.?, and p.? without an exact entry.
Met at Strong: gnomAD v4.1 Grpmax FAF was 0.00072958, within the VCEP BS1 interval of 0.00028 to below 0.0028.
The InSiGHT PMS2 VCEP Version 2.0 defines BS1 Strong as gnomAD v4 Grpmax filtering allele frequency >=0.00028 and <0.0028 (0.028-0.28%), excluding founder pathogenic variants.gnomAD v4.1 reports joint Grpmax FAF 0.00072958 (0.072958%), based on 99/1,558,792 total alleles and 0 homozygotes; the South Asian subgroup has AF 0.000887134 (80/90,178 alleles).
Met at Supporting: c.1145-11C>T is intronic at -11, within the PMS2 VCEP BP7 range of -21/+7.
The PMS2 VCEP BP7 rule applies at Supporting strength to synonymous or intronic variants at or beyond -21/+7 relative to the exonic boundary.NM_000535.7:c.1145-11C>T is an intronic variant located 11 bases upstream of the exon boundary, within the specified BP7 range.
Assessed · not applied
· 4 not met · 10 not assessed
Pathogenic
PVS1Not met: NM_000535.7:c.1145-11C>T is an intronic −11 variant outside the PMS2 VCEP’s ±1/2 splice-site PVS1 rule.
PS1Not assessed: SpliceAI max delta is 0.213, but no qualifying pathogenic comparator at the same non-canonical splice nucleotide is documented.
PS2Not assessed: no proband-level de novo observation, parental confirmation, tumor consistency, or de novo point total is documented.
PS3Not assessed: no variant-specific functional or RNA assay is reported; SpliceAI max delta 0.213 is predictive, not functional evidence.
PM2Not met: gnomAD v4.1 total AF was 0.0000635107, exceeding the VCEP PM2 threshold of less than 0.00002.
PM3Not assessed: no affected-proband CMMRD observation or pathogenic PMS2 partner with documented phase is available to assign the VCEP's PM3 points.
PP1Not assessed: no informative pedigree, meioses, affected-relative testing, or combined Bayes Likelihood Ratio is documented.
PP4Not assessed: no patient-specific MSI, tumor-genome, or PMS2 IHC result is available to satisfy the PP4 tumor-evidence rule.
Benign
BA1Not met: gnomAD v4.1 Grpmax FAF was 0.00072958, below the VCEP BA1 threshold of 0.0028.
BS2Not assessed: no documented in-trans pathogenic PMS2 variant, phase confirmation, qualifying age, or CMMRD assessment is available for the BS2 rule.
BS3Not assessed: no variant-specific benign functional or RNA result is reported; SpliceAI max delta 0.213 cannot establish proficient function.
BS4Not assessed: no documented non-segregating affected relatives, informative meioses, or combined Bayes Likelihood Ratio is available.
BP4Not met: SpliceAI max delta 0.213 exceeds the PMS2 VCEP no-impact threshold of <=0.1.
BP5Not assessed: no tumor MSS/IHC, BRAF V600E, or MLH1 methylation findings are available for the BP5 alternate-basis rule.
This variant is present in gnomAD v4.1 (AF= 6.35107e-05; MAF= 0.00635%, 99/1558792 alleles, homozygotes = 0) and has highest observed frequency in the South Asian population (AF= 0.000887134; MAF= 0.08871%, 80/90178 alleles, homozygotes = 0); grpmax FAF= 0.00072958.
v2.1
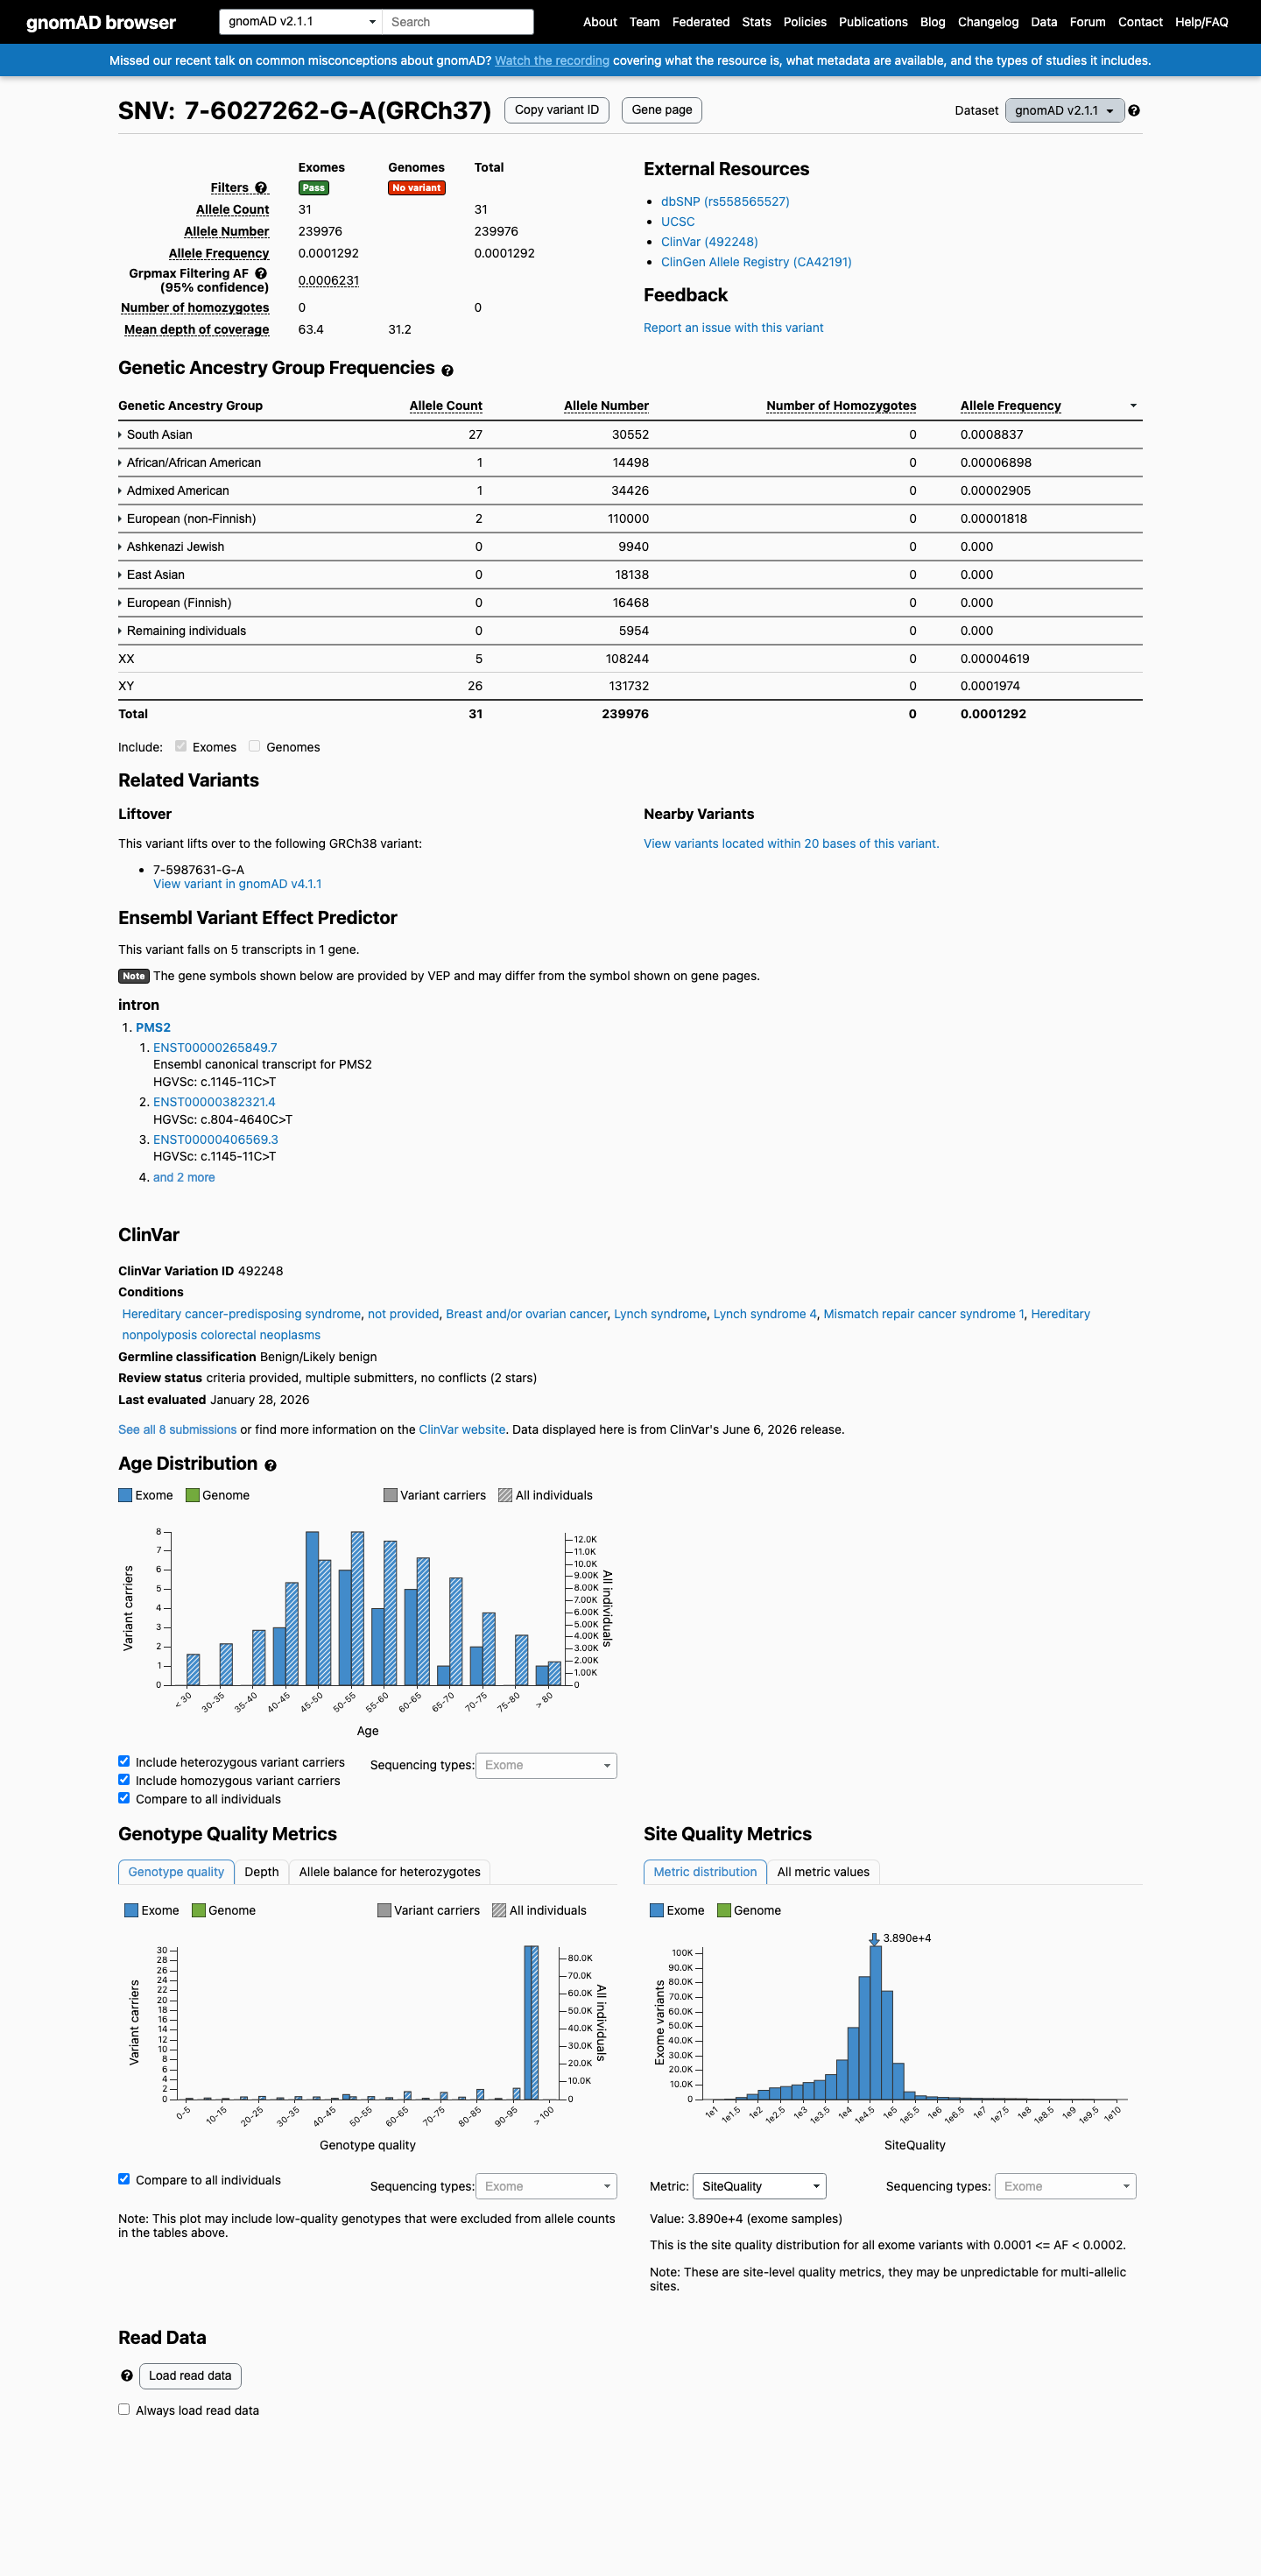
This variant is present in gnomAD v2.1 (AF= 0.00012918; MAF= 0.01292%, 31/239976 alleles, homozygotes = 0) and has highest observed frequency in the South Asian population (AF= 0.000883739; MAF= 0.08837%, 27/30552 alleles, homozygotes = 0); grpmax FAF= 0.0006231.
🇨🇦 CA
This variant is present in gnomAD-Canada v1.0 (AF= 0.0001085894233901618, 2/18418 alleles, homozygotes = 0).
Allele frequency by ancestry
three datasets · side by side
gnomAD v4.1
0.0064%
· 99 / 1,558,792
0 hom · FAF 0.073%
South Asian
80 / 90,178
0.089%
African/African American
5 / 74,106
0.0067%
Admixed American
2 / 59,878
0.0033%
Remaining individuals
2 / 60,956
0.0033%
European (non-Finnish)
10 / 1,136,346
0.00088%
+ 5 not observed (European (Finnish), Amish, East Asian, Middle Eastern, Ashkenazi Jewish)
gnomAD v2.1
0.013%
· 31 / 239,976
0 hom · FAF 0.062%
South Asian
27 / 30,552
0.088%
African/African American
1 / 14,498
0.0069%
Admixed American
1 / 34,426
0.0029%
European (non-Finnish)
2 / 110,000
0.0018%
+ 4 not observed (Ashkenazi Jewish, East Asian, European (Finnish), Remaining individuals)
gnomAD Canada 🇨🇦
0.011%
· 2 / 18,418
0 hom · FAF 0.026%
South Asian
2 / 1,362
0.15%
+ 8 not observed (African/African American, Latino/Admixed American, Ashkenazi Jewish, East Asian, European (Finnish), Middle Eastern, European (non-Finnish), Remaining individuals)
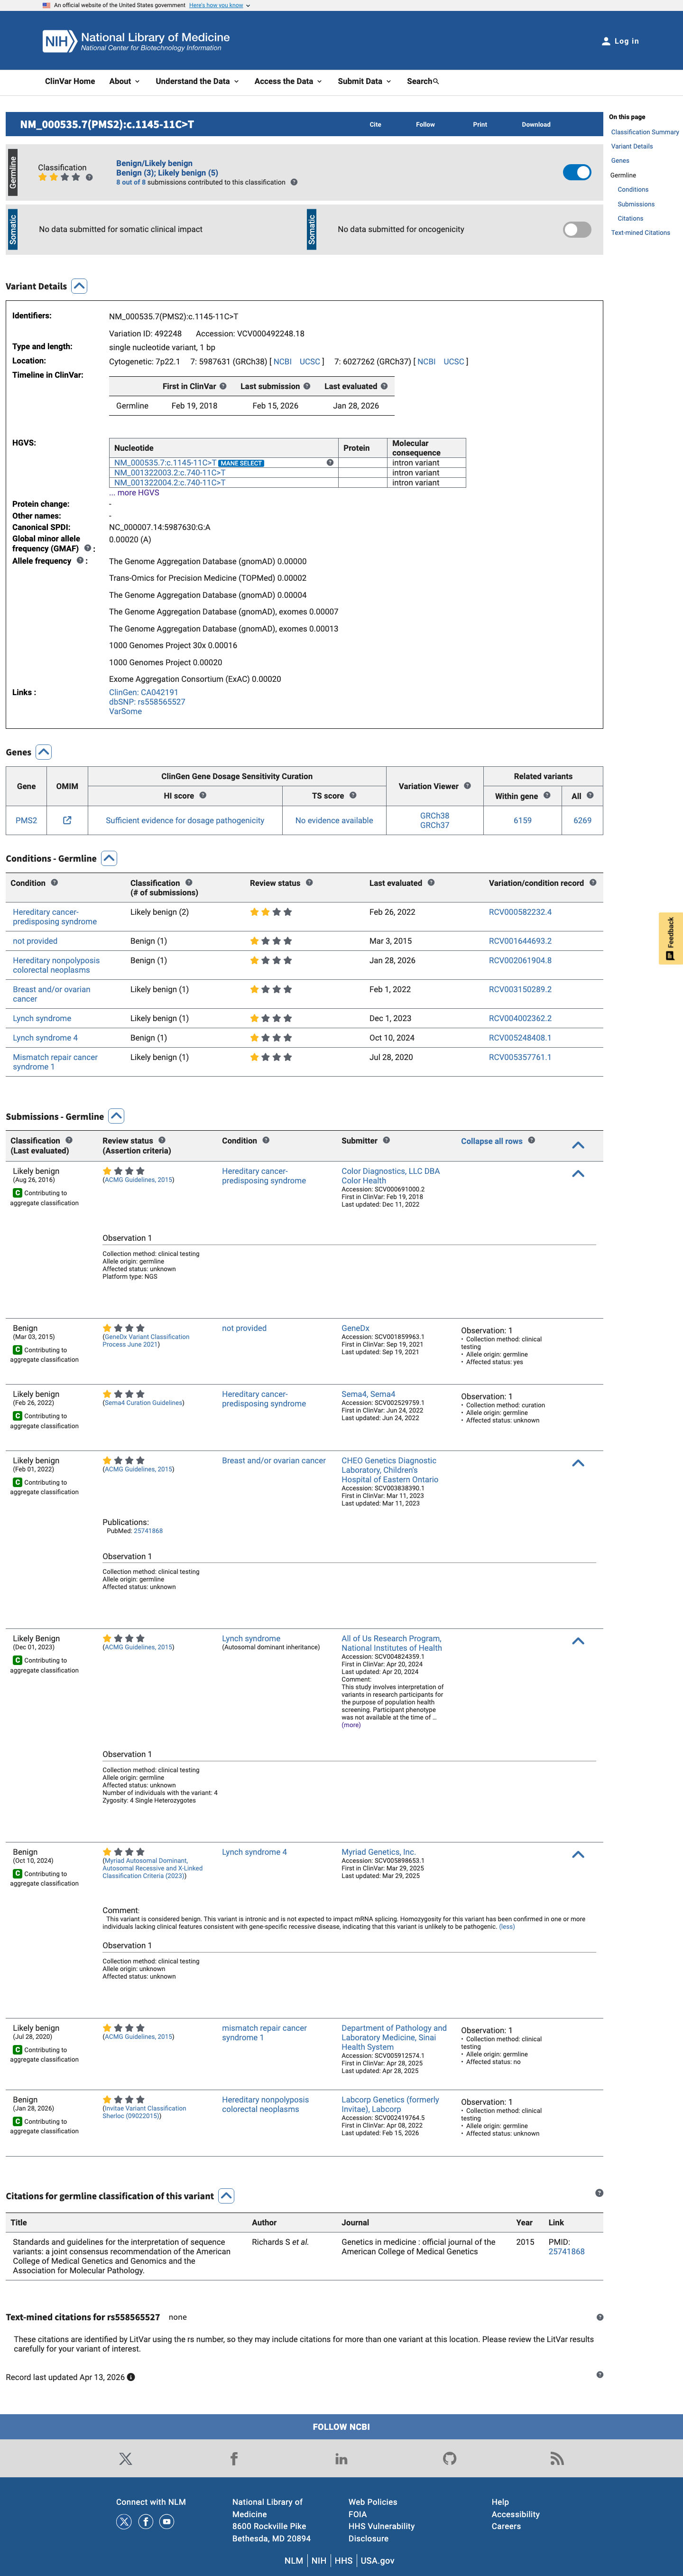
This variant has been reported in ClinVar as Likely benign (3 clinical laboratories) and as Benign (3 clinical laboratories) and as Likely Benign (1 clinical laboratory). (ClinVarID = 492248)
Triaged references · 7 PMIDs not cited in assessment
25741868 ↗Standards and guidelines for the interpretation of sequence variants: a joint consensus recommendation of the American College of Medical Genetics and Genomics and the Association for Molecular Pathology.CLINVAR
11598466 ↗Practice parameters for the identification and testing of patients at risk for dominantly inherited colorectal cancer--supporting documentation.CLINVAR
23535968 ↗Informing family members of individuals with Lynch syndrome: a guideline for clinical geneticists.CLINVAR
25394175 ↗A practice guideline from the American College of Medical Genetics and Genomics and the National Society of Genetic Counselors: referral indications for cancer predisposition assessment.CLINVAR
25452455 ↗Hereditary colorectal cancer syndromes: American Society of Clinical Oncology Clinical Practice Guideline endorsement of the familial risk-colorectal cancer: European Society for Medical Oncology Clinical Practice Guidelines.CLINVAR
25711197 ↗Lynch Syndrome: A Primer for Urologists and Panel Recommendations.CLINVAR
28492532 ↗Sherloc: a comprehensive refinement of the ACMG-AMP variant classification criteria.CLINVAR