APC is a tumor suppressor gene whose protein acts as a key brake on the Wnt signaling pathway by helping mark the growth-promoting protein beta-catenin for destruction; it also participates in cell migration, adhesion, and apoptosis. Inherited mutations in APC cause familial adenomatous polyposis (FAP), an autosomal dominant condition characterized by numerous colorectal polyps and a very high risk of colorectal cancer, with related forms including attenuated FAP and gastric adenocarcinoma and proximal polyposis of the stomach (GAPPS). Somatic APC mutations are found in roughly 50-80% of sporadic colorectal cancers, where they act as early tumor-initiating events, and are also observed in some breast, stomach, and prostate cancers. Loss of APC function leaves Wnt signaling abnormally active, driving uncontrolled cell growth, which makes APC a central tumor suppressor in colorectal cancer.
This variant
This APC variant occurs in a tumor-suppressor gene that restrains Wnt signaling, whose inherited loss predisposes to familial adenomatous polyposis and colorectal cancer.
Transcript
NM_001127510.3
HGVS · transcript:coding
NM_001127510.3:c.4413A>G
GRCh38
chr5:112840007 A>G
GRCh37
chr5:112175704 A>G
Likely Benign: PM2, BP4, and BP7 at supporting strength satisfy APC VCEP Version 2.1 Rule19.
Classification rationale
PM2BP4BP7Likely Benign
APC c.4413A>Gsynonymous · exon 17
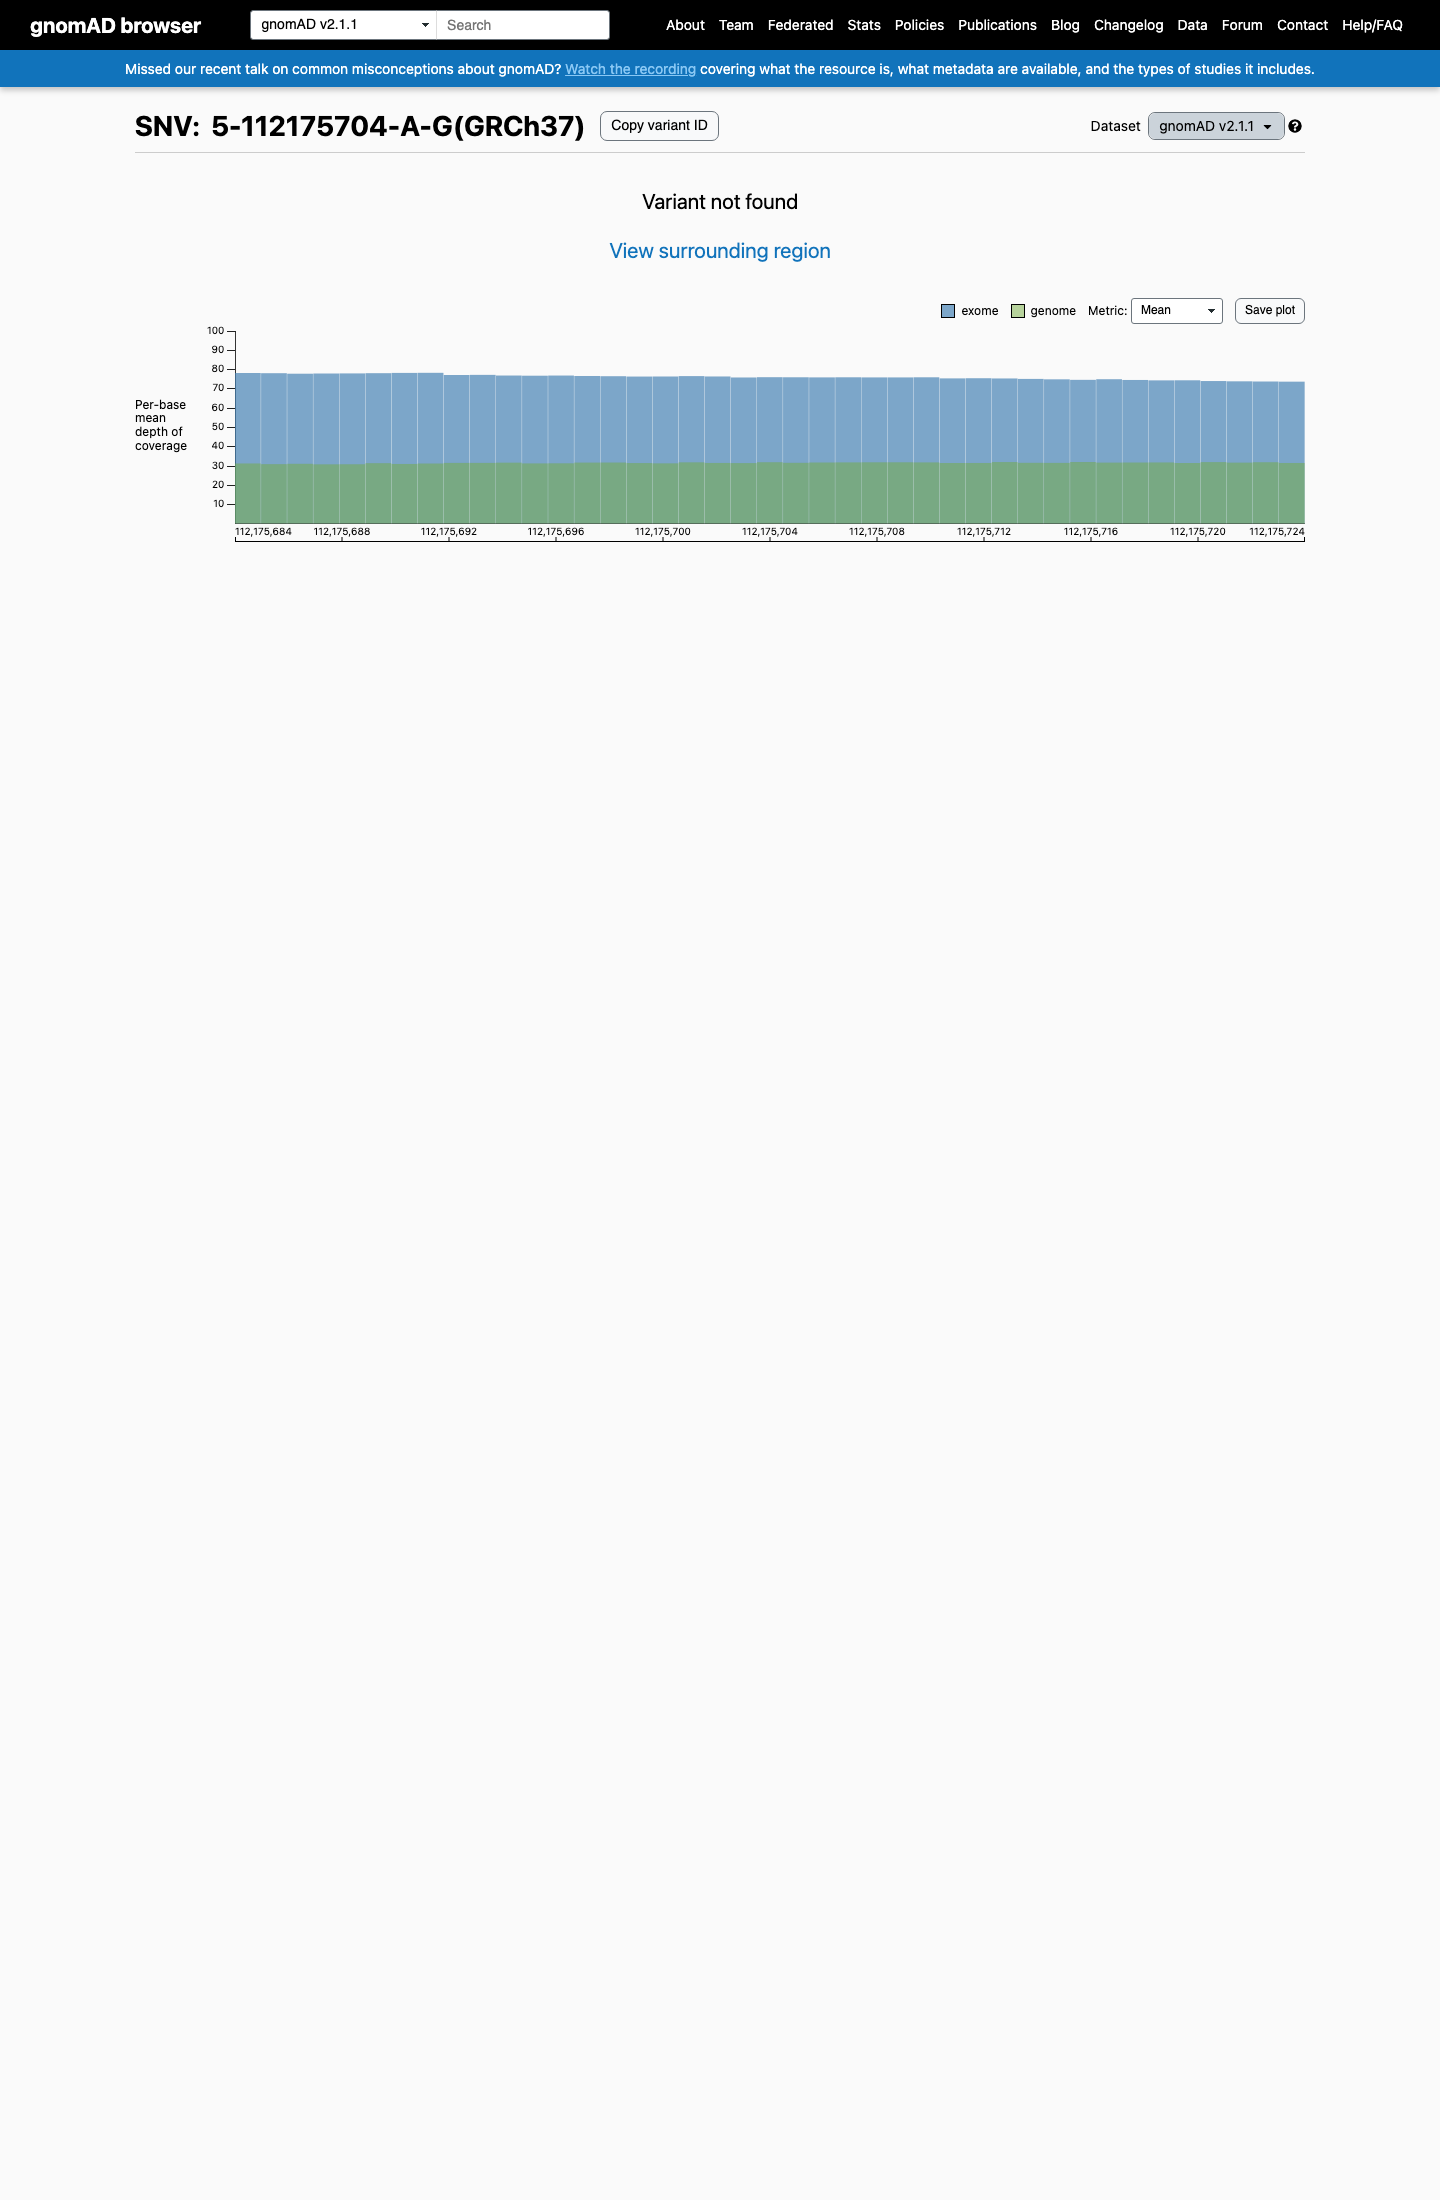
PM2 supporting: the variant is absent from gnomAD v2.1.1 non-cancer exomes, with AF 0 and allele count 0. BP4 supporting: SpliceAI maximum delta 0.001 and Pangolin predictions indicate no significant splice impact. BP7 supporting: the synonymous variant has concordant near-zero splice predictions from multiple algorithms.
PM2 + BP4 + BP7→Likely Benign
LYFE Sciences is an AI system, and it can make mistakes. Criteria
may be applied incorrectly, sources may be misread, and a confident-looking
classification can still be wrong. Double-check every criterion and
its underlying evidence before relying on any call.
Gene diagram
· NM_001127510.3 · variants mapped to exon structure
APCNM_001127510.3
Fetching transcript structure from UCSC…
Exons
—
Transcript span
—
Strand
—
Variants mapped
—
Source
UCSC ncbiRefSeqCurated
All variants in APC—click a row to locate it on the plot · use the link column to open its page
Protein
Location
Classification
Link
Applied criteria · 3 applied · 13 assessed
MetEvidence satisfies this criterion.
Not metEvaluated against available evidence; threshold not reached.
Not assessedApplies in principle, but no evidence was found to evaluate it.
N/ADoesn't apply to this variant type.
Applied · 3
Strength Supporting Moderate Strong Very strong
✓
PM2supportingPathogenic
Met at supporting: gnomAD v2.1.1 non-cancer exomes show AF 0 with allele count 0, below the APC PM2 threshold of 0.00001.
The APC InSiGHT VCEP specifies the total population from gnomAD v2.1.1 non-cancer and defines PM2_Supporting as AF <= 0.000003 for allele count > 1 or AF < 0.00001 for allele count <= 1.The variant is absent from the gnomAD v2.1 non-cancer exome dataset, equivalent to allele count 0 and AF 0; this satisfies the allele-count-at-most-1 branch of the VCEP PM2 rule.
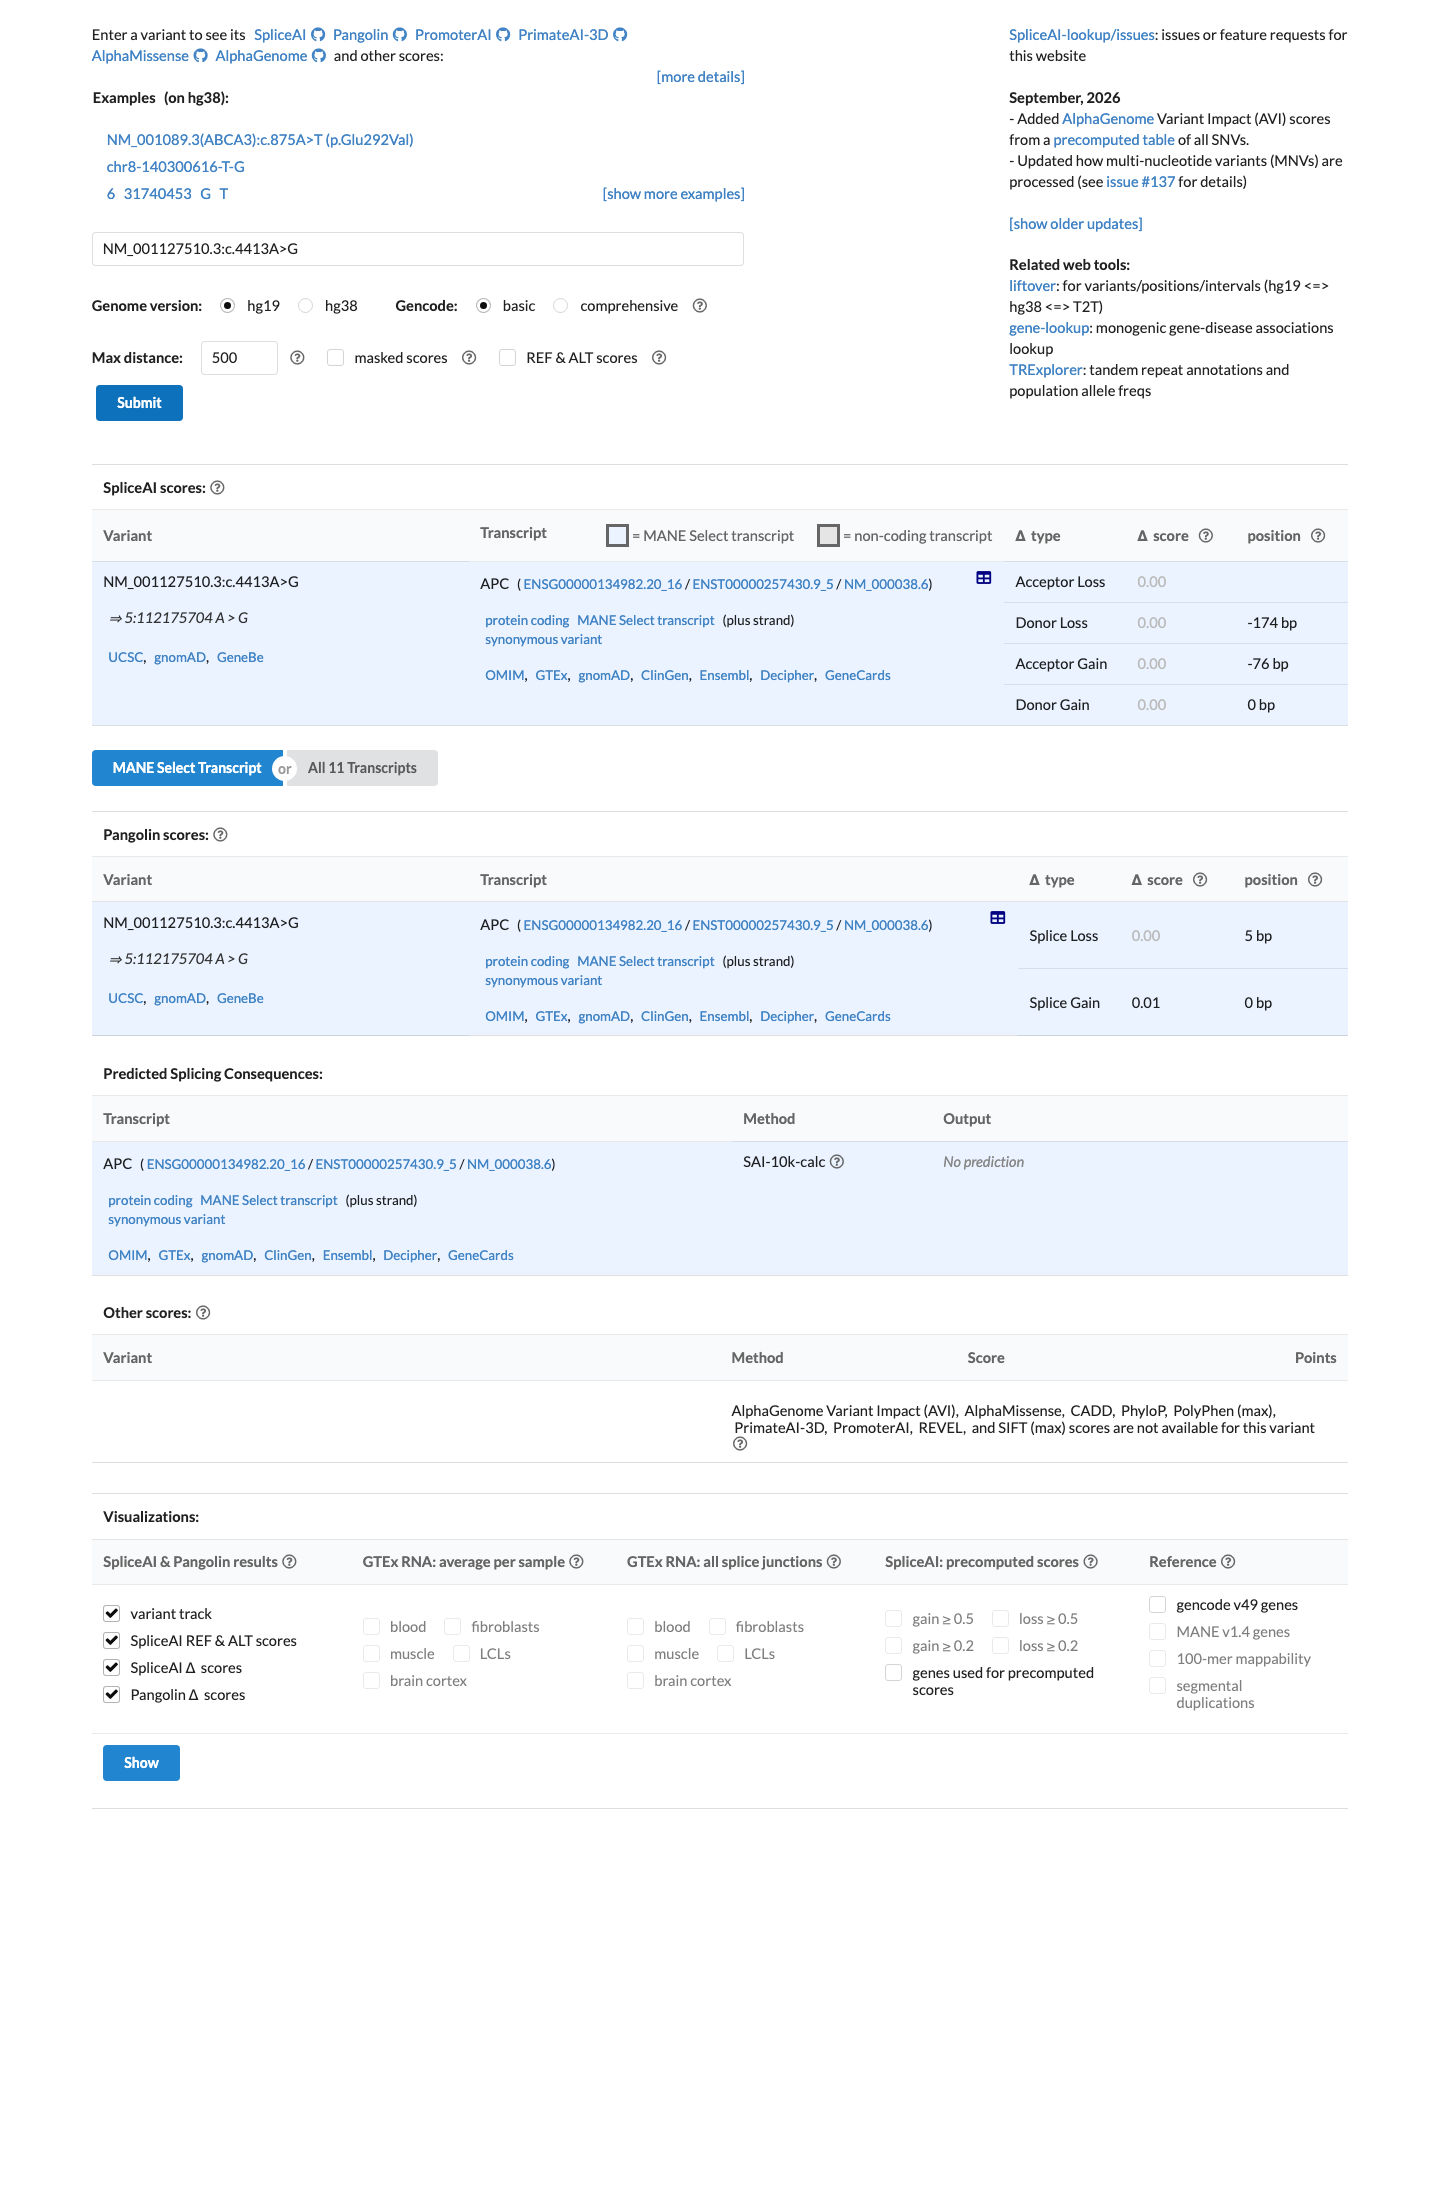
Met at supporting: SpliceAI max delta 0.001 is below the <=0.1 BP4 threshold and predicts no significant splice impact.
The APC VCEP states that BP4 Supporting applies to synonymous or intronic variants when multiple in silico splicing predictors suggest no impact on the gene or gene product.SpliceAI maximum delta is 0.001, below the generic BP4 supporting cutoff of 0.1 from Jaganathan et al. 2019 (PMID:30661751).The available Pangolin outputs are 0.012 and -0.003, concordant with the near-zero SpliceAI result and no predicted splice impact.
Met at supporting: the synonymous variant has concordant near-zero splice predictions, including SpliceAI max delta 0.001.
The APC VCEP BP7 rule covers synonymous variants when multiple splice-prediction algorithms predict no impact to the splice consensus sequence or creation of a new splice site.SpliceAI maximum delta is 0.001, with individual delta scores from 0.000 to 0.001; Pangolin outputs are 0.012 and -0.003, concordant with no predicted splice impact.BP7 is assessed independently as the synonymous-variant benign criterion and does not double-count the same prediction as PP3 or BP4.
Assessed · not applied
· 4 not met · 9 not assessed
Pathogenic
PS2Not assessed: no proband phenotype, parental genotypes, confirmed maternity or paternity, or de novo observation is documented for c.4413A>G.
PS3Not assessed: no variant-specific RNA or protein assay result was identified to meet the APC VCEP PS3 requirements.
PS4Not assessed: no exact-variant phenotype points, case-control enrichment estimate, odds ratio, relative risk, or confidence interval is available for the APC PS4 rules.
PM6Not assessed: no assumed de novo observation, proband phenotype, parental testing, or de novo score is documented for c.4413A>G.
PP1Not assessed: zero affected relatives, phenotype-positive carriers, pedigrees, or informative meioses are documented for c.4413A>G.
PP3Not met: SpliceAI max delta 0.001 is below the 0.2 PP3 supporting threshold for a deleterious splice effect.
Benign
BA1Not met: the variant is absent from gnomAD v2.1.1 non-cancer exomes, below the APC BA1 threshold of 0.001.
BS1Not met: the variant is absent from gnomAD v2.1.1 non-cancer exomes, below the APC BS1 threshold of 0.00001.
BS2Not met: gnomAD v2.1.1 non-cancer exomes show zero homozygous observations, below the APC BS2 requirement of at least 2.
BS3Not assessed: no variant-specific RNA or protein assay demonstrated normal APC function or splicing under the VCEP BS3 requirements.
BS4Not assessed: no affected non-carrier or qualifying phenotype score is documented to meet the APC BS4 threshold of 0.5 or 1 point.
BP2Not assessed: no affected-proband phase data, in-trans pathogenic APC variant, or three qualifying unknown-phase co-occurrences are documented.
BP5Not assessed: no qualifying alternate-gene Pathogenic or Likely pathogenic variant and no documented colorectal polyposis phenotype are available for the APC BP5 rule.
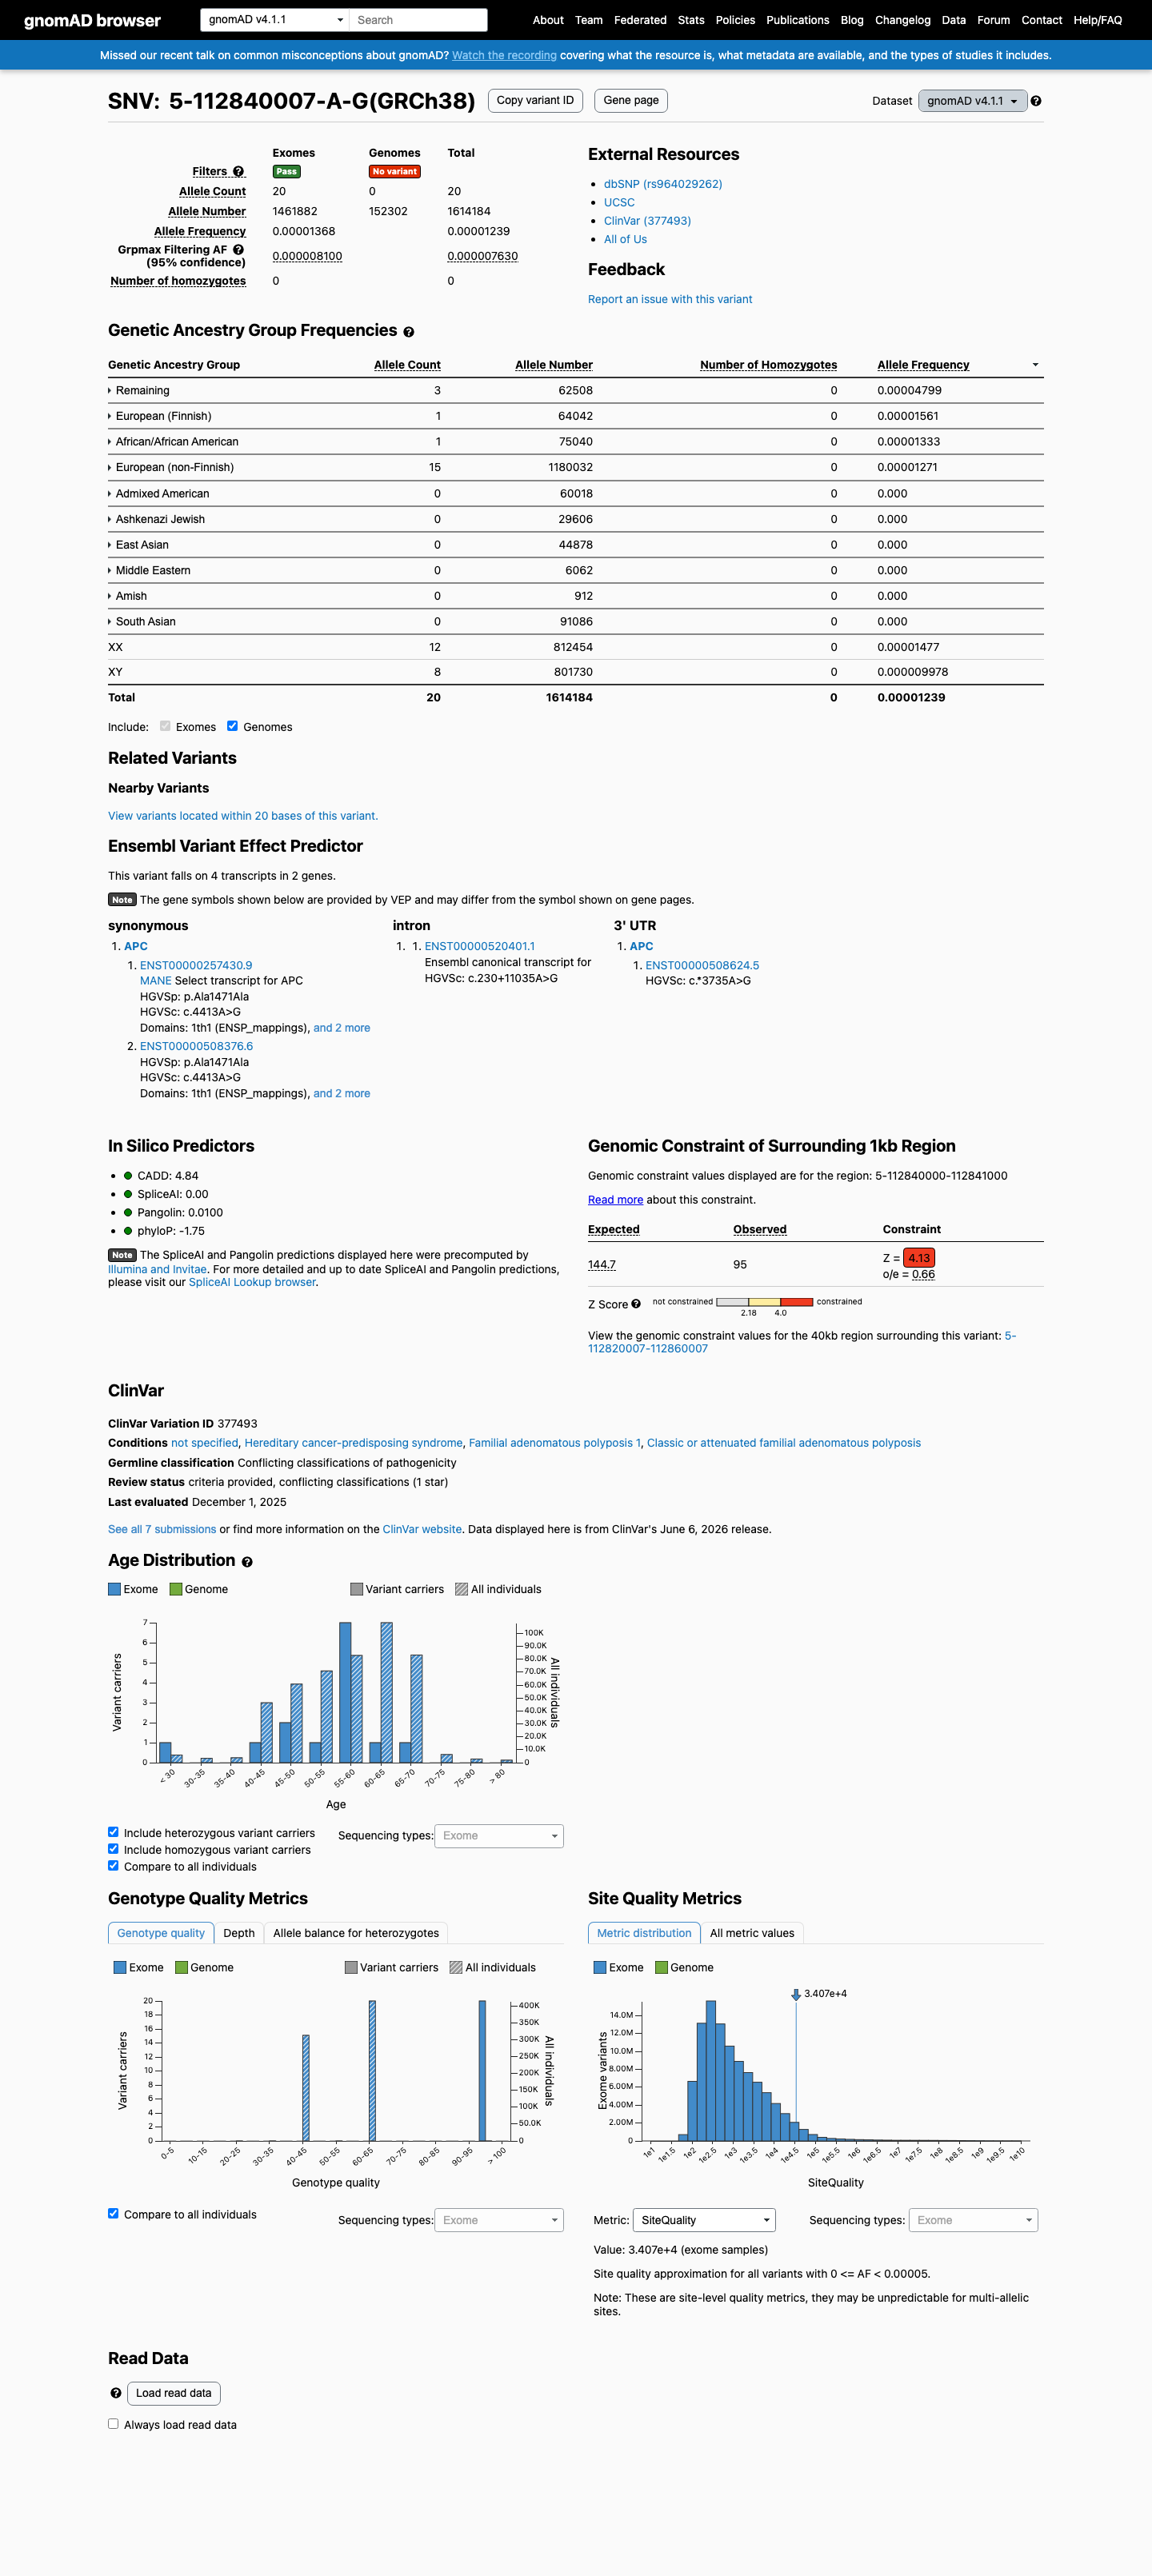
This variant is present in gnomAD v4.1 (AF= 1.23902e-05; MAF= 0.00124%, 20/1614184 alleles, homozygotes = 0) and has highest observed frequency in the Remaining individuals population (AF= 4.79939e-05; MAF= 0.00480%, 3/62508 alleles, homozygotes = 0); grpmax FAF= 7.63e-06.
v2.1
Absent from gnomAD v2.1.
🇨🇦 CA
Absent from gnomAD-Canada v1.0.
Allele frequency by ancestry
three datasets · side by side
gnomAD v4.1
0.0012%
· 20 / 1,614,184
0 hom · FAF 0.00076%
Remaining individuals
3 / 62,508
0.0048%
European (Finnish)
1 / 64,042
0.0016%
African/African American
1 / 75,040
0.0013%
European (non-Finnish)
15 / 1,180,032
0.0013%
+ 6 not observed (Admixed American, Amish, East Asian, Middle Eastern, South Asian, Ashkenazi Jewish)
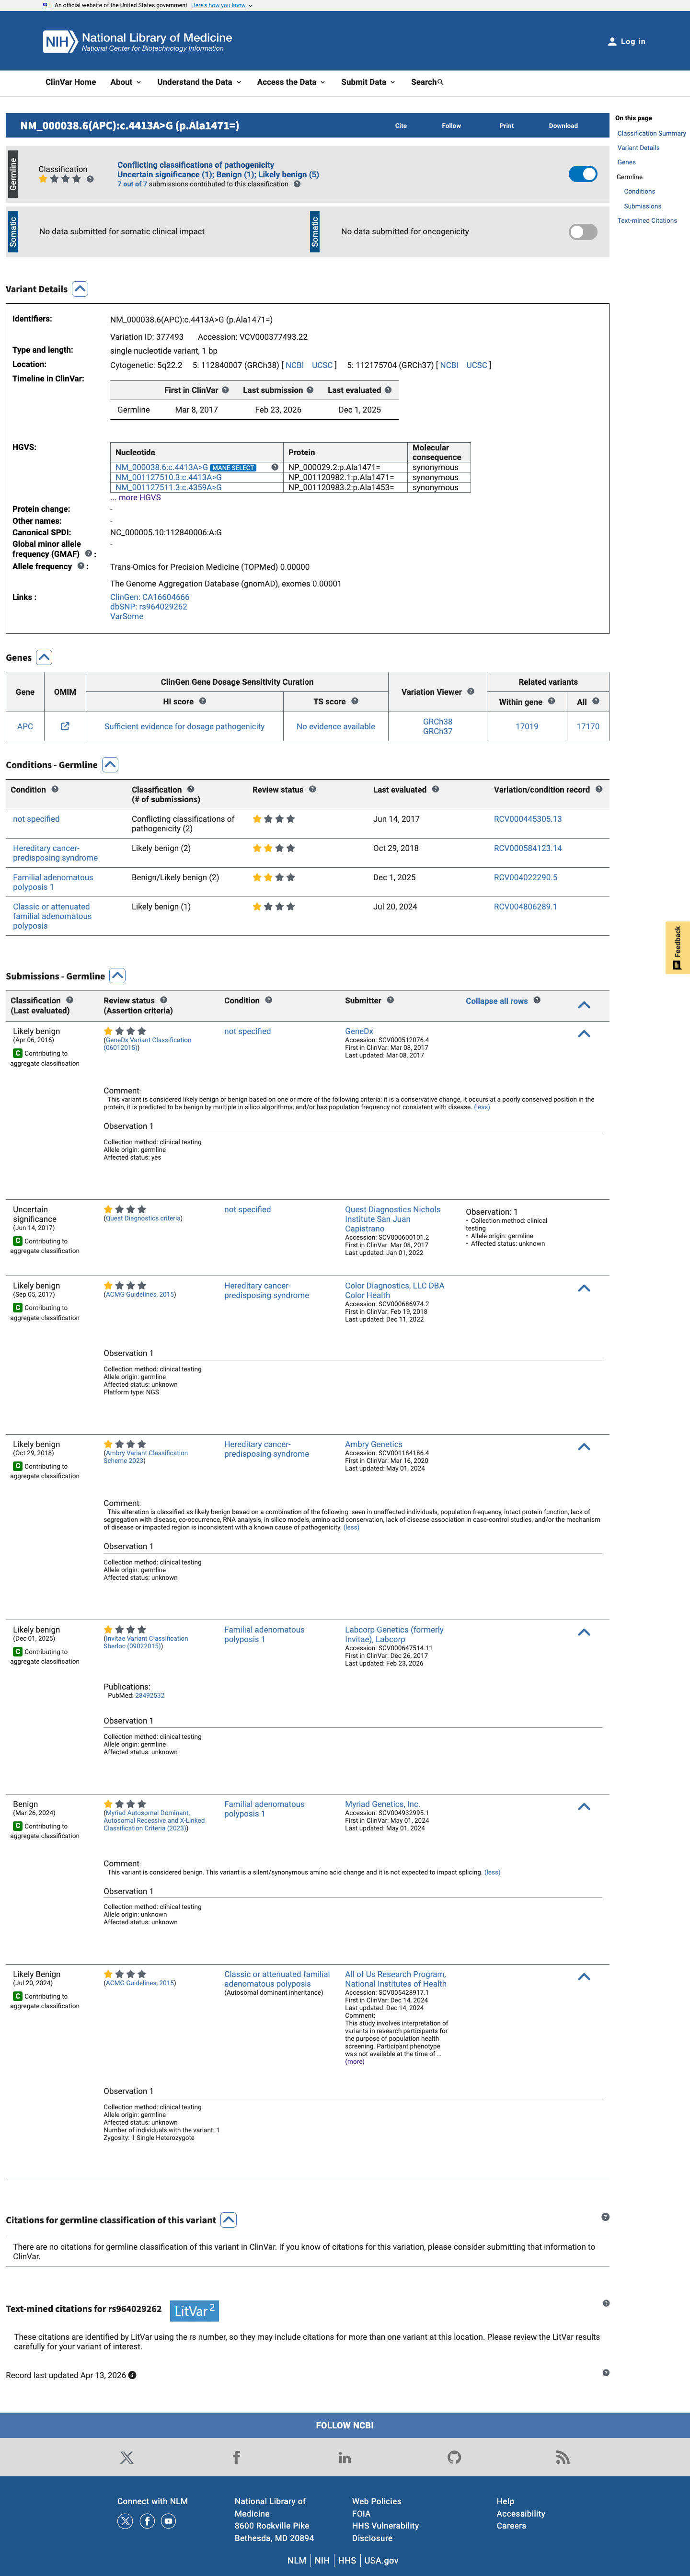
This variant has been reported in ClinVar as Likely benign (4 clinical laboratories) and as Uncertain significance (1 clinical laboratory) and as Benign (1 clinical laboratory) and as Likely Benign (1 clinical laboratory). (ClinVarID = 377493)
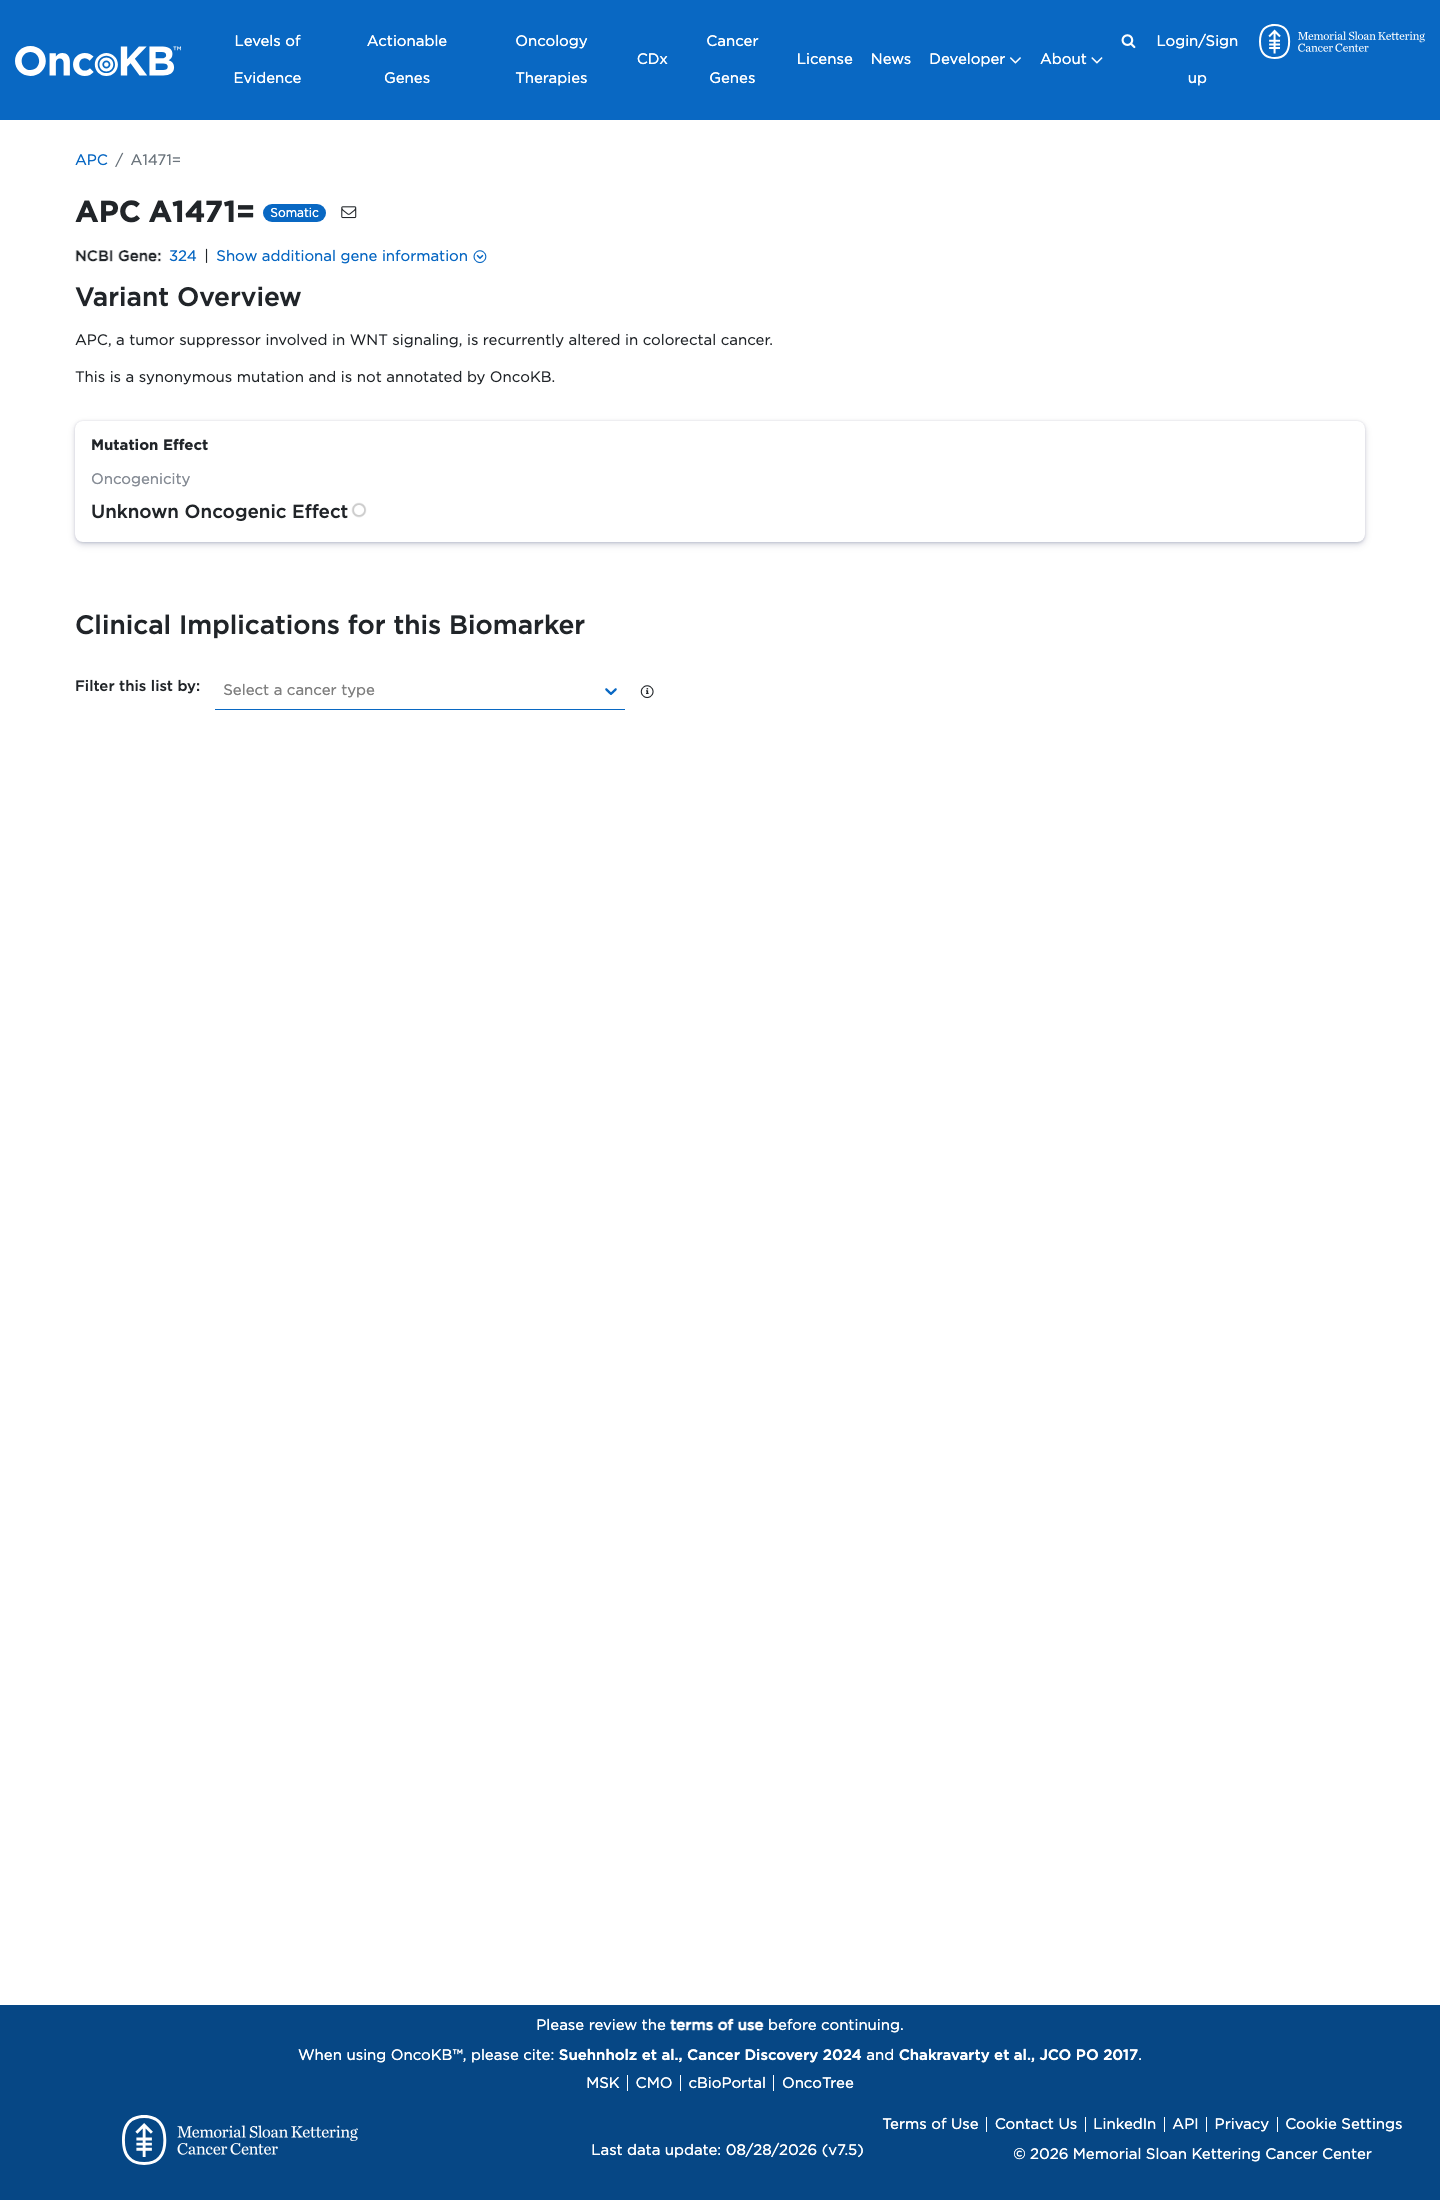
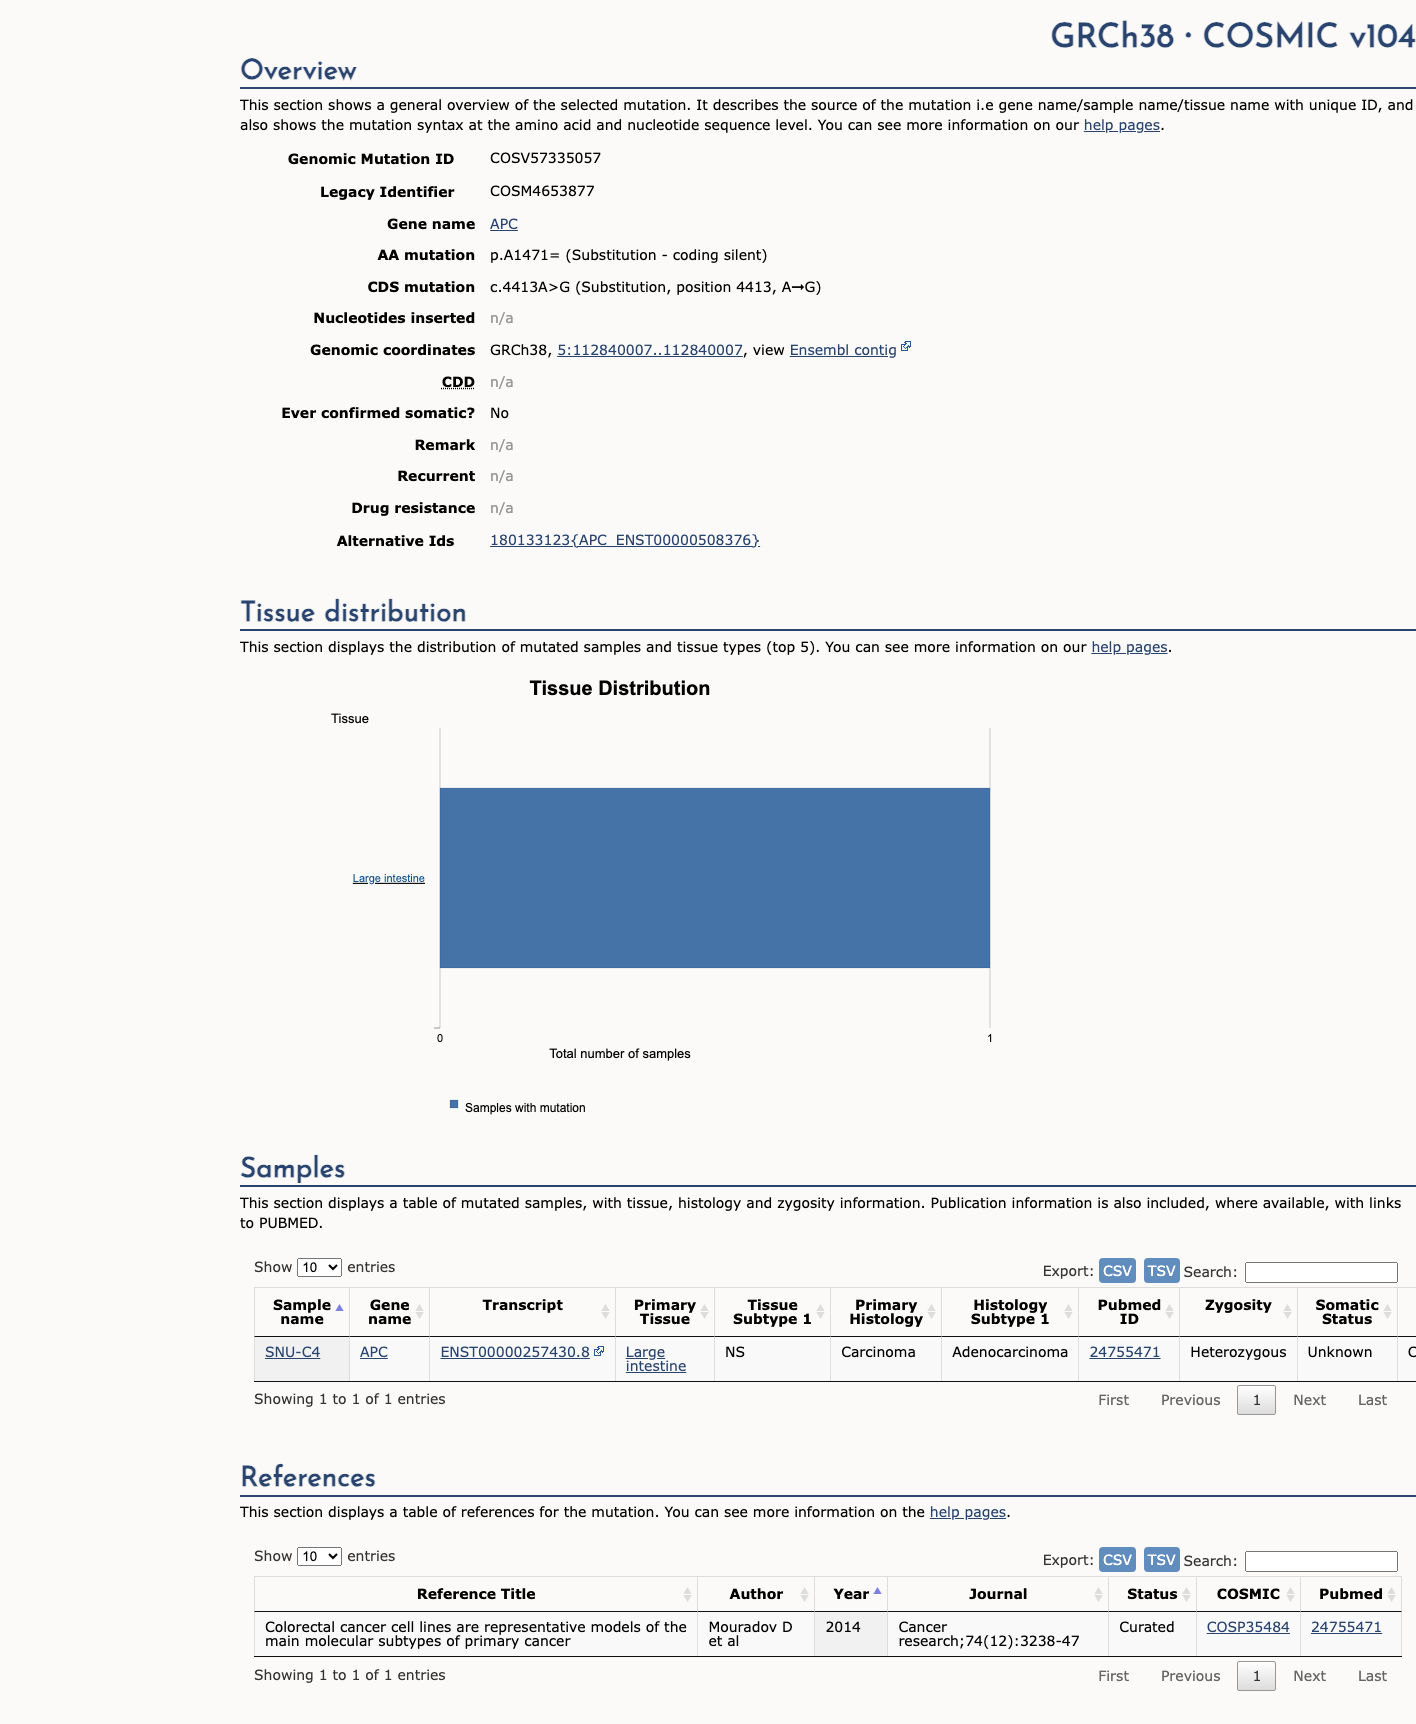
This variant does not lie in a statistically significant hotspot. This variant has previously been reported in somatic cancers (COSMIC; COSV57335057, n = 1 times).
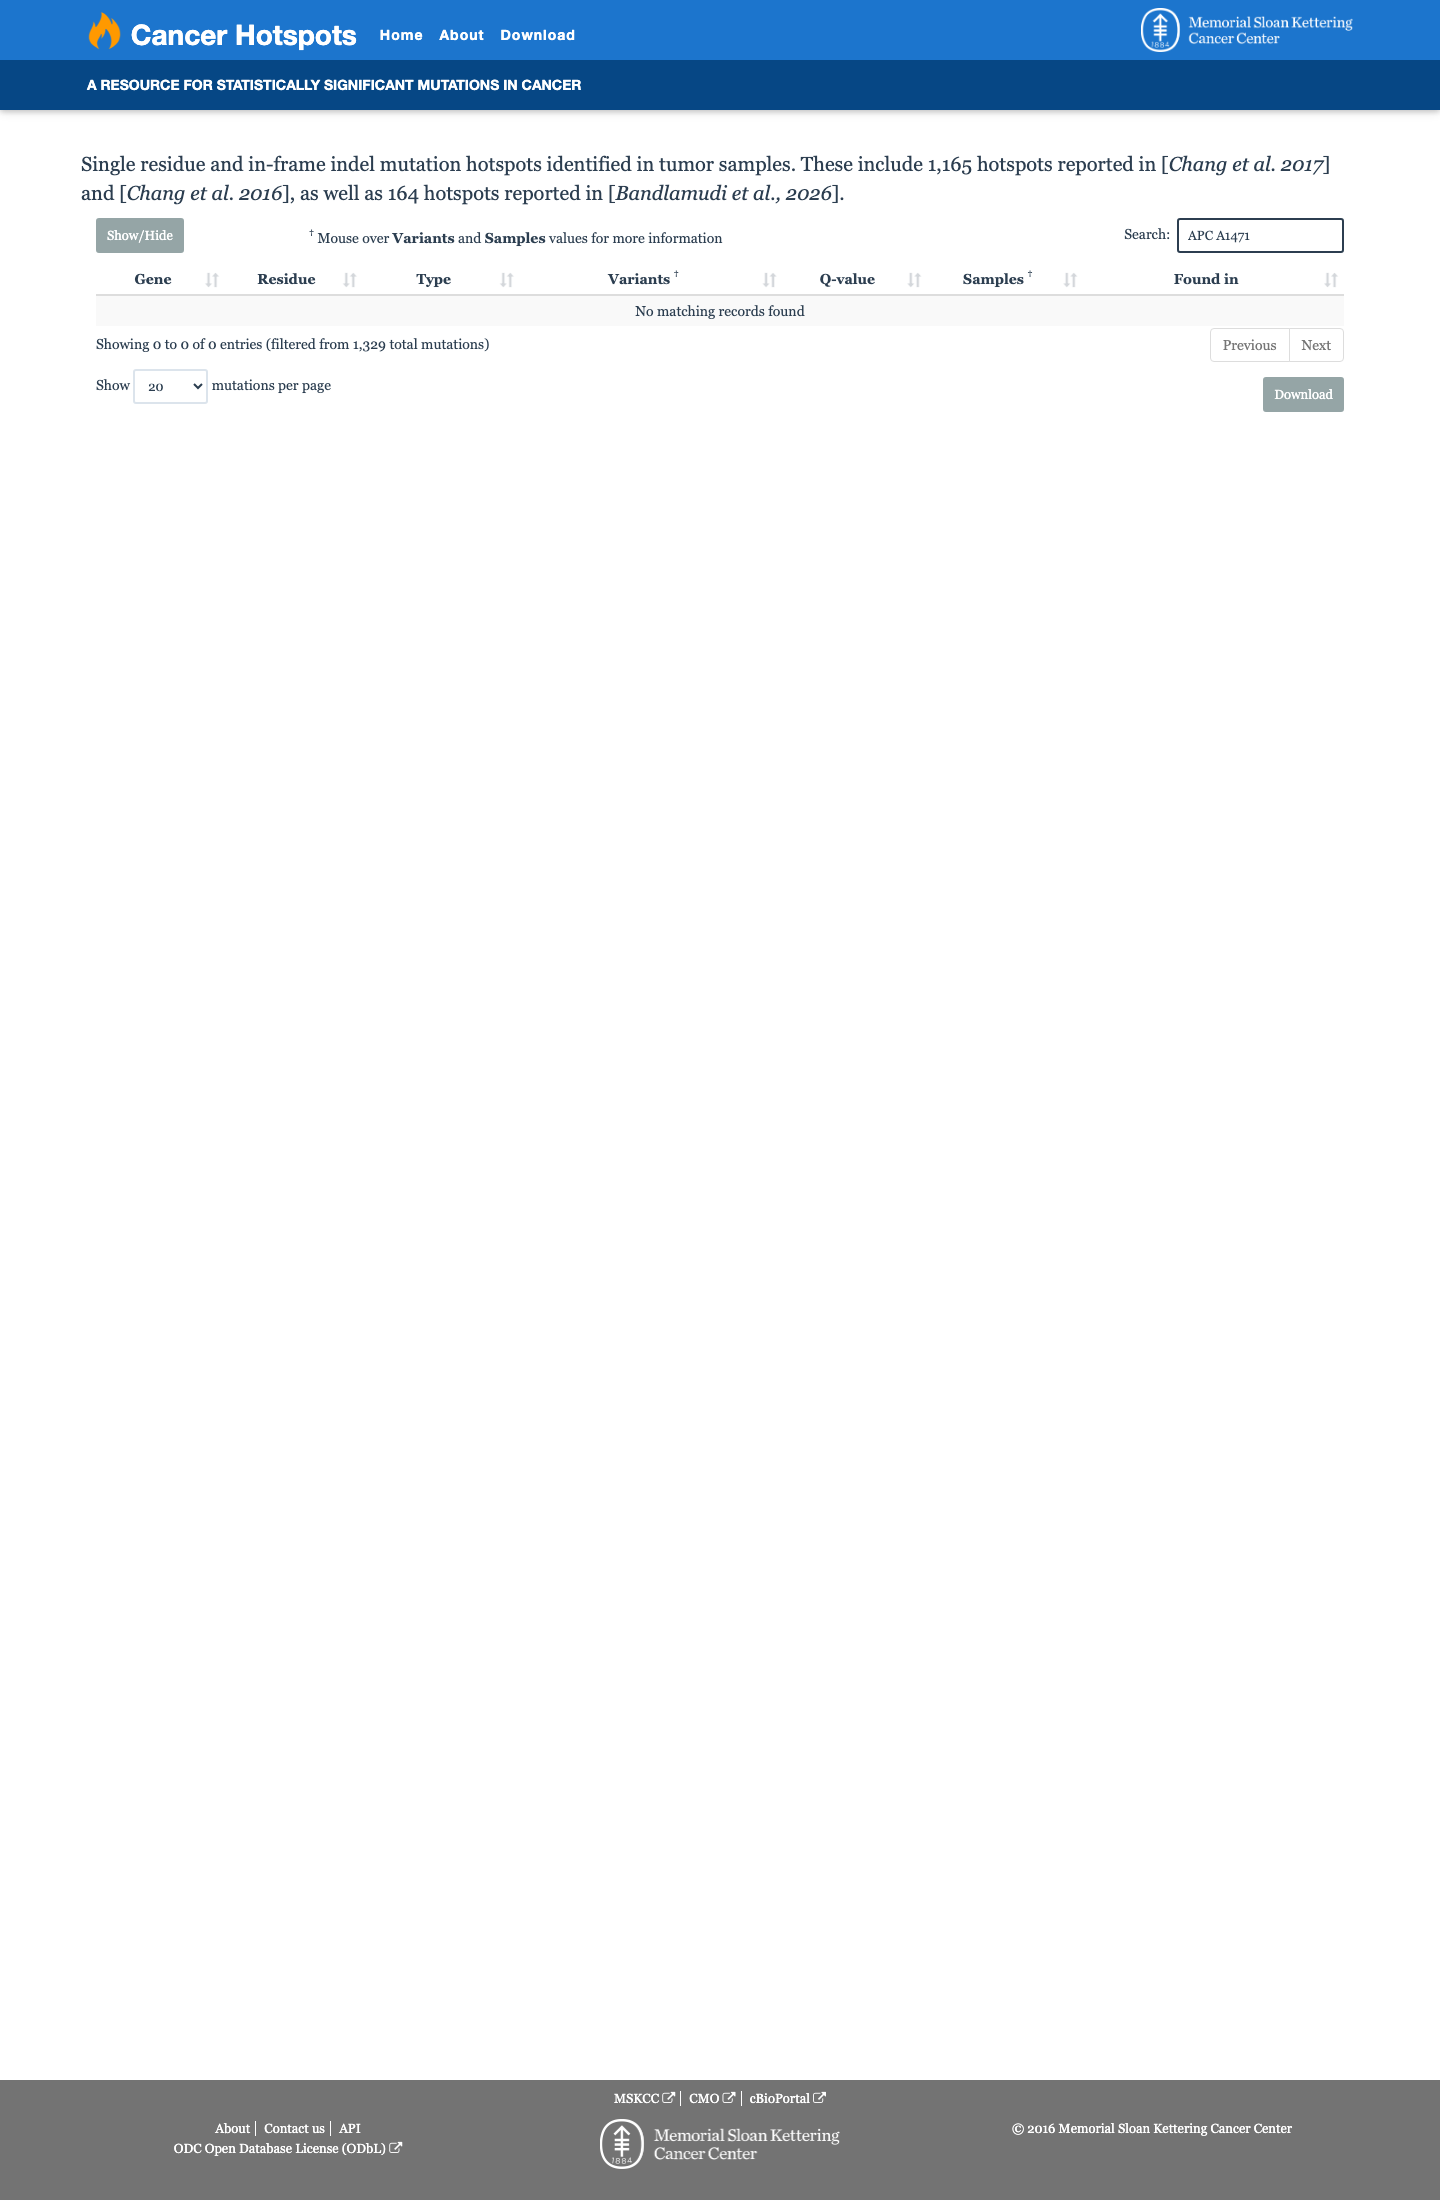
Hotspots
This variant does not lie in a statistically significant hotspot.
Triaged references · 8 PMIDs not cited in assessment
25741868 ↗Standards and guidelines for the interpretation of sequence variants: a joint consensus recommendation of the American College of Medical Genetics and Genomics and the Association for Molecular Pathology.CLINVAR
26467025 ↗A Standardized DNA Variant Scoring System for Pathogenicity Assessments in Mendelian Disorders.CLINVAR
11598466 ↗Practice parameters for the identification and testing of patients at risk for dominantly inherited colorectal cancer--supporting documentation.CLINVAR
24310308 ↗ACMG technical standards and guidelines for genetic testing for inherited colorectal cancer (Lynch syndrome, familial adenomatous polyposis, and MYH-associated polyposis).CLINVAR
25452455 ↗Hereditary colorectal cancer syndromes: American Society of Clinical Oncology Clinical Practice Guideline endorsement of the familial risk-colorectal cancer: European Society for Medical Oncology Clinical Practice Guidelines.CLINVAR
34012068 ↗ACMG SF v3.0 list for reporting of secondary findings in clinical exome and genome sequencing: a policy statement of the American College of Medical Genetics and Genomics (ACMG).CLINVAR
28492532 ↗Sherloc: a comprehensive refinement of the ACMG-AMP variant classification criteria.CLINVAR