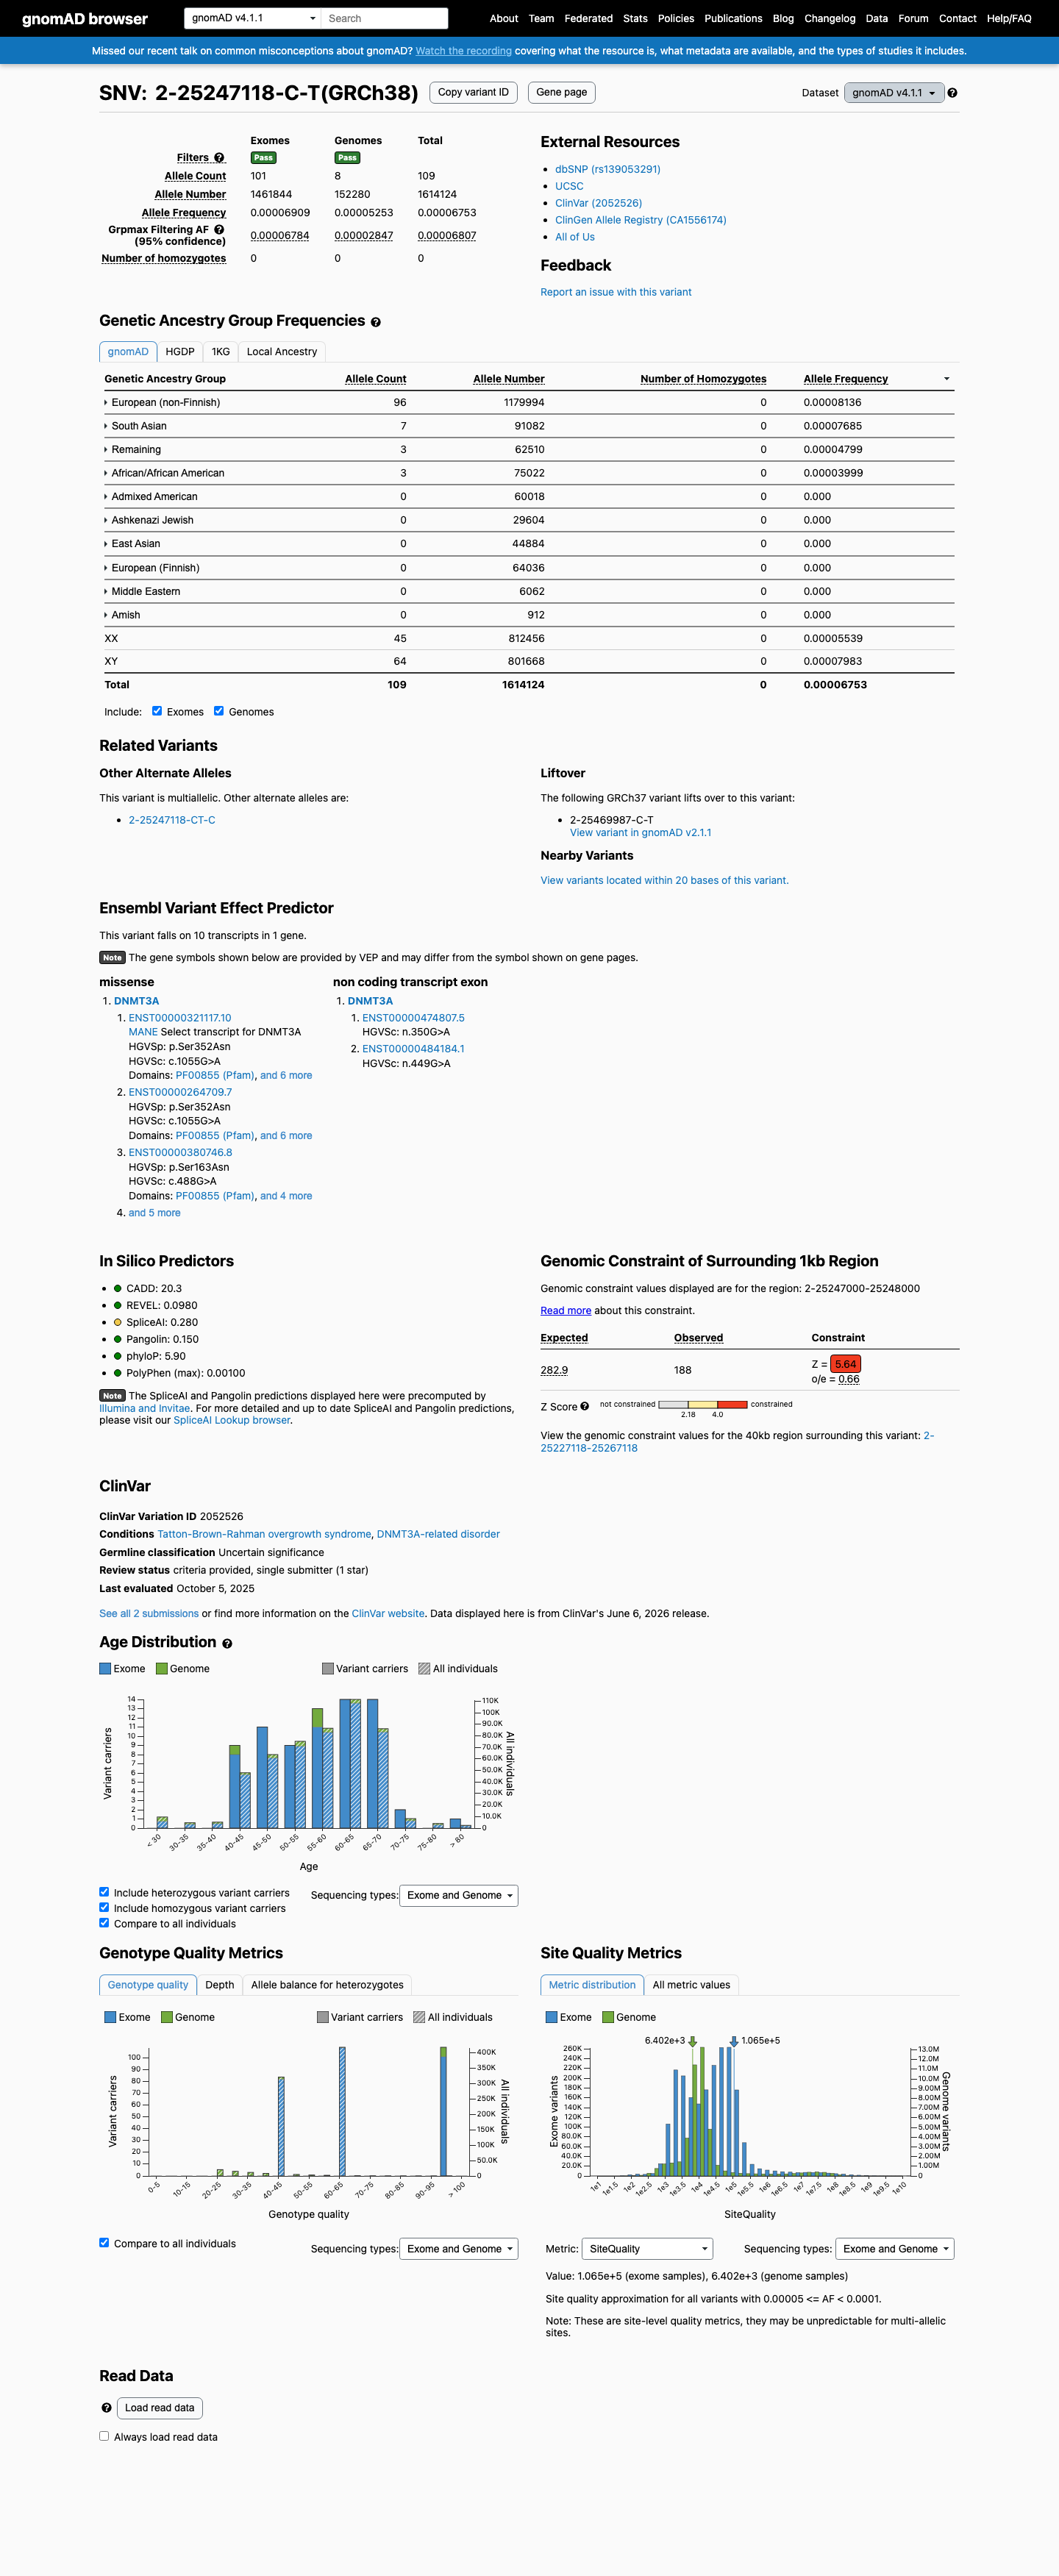
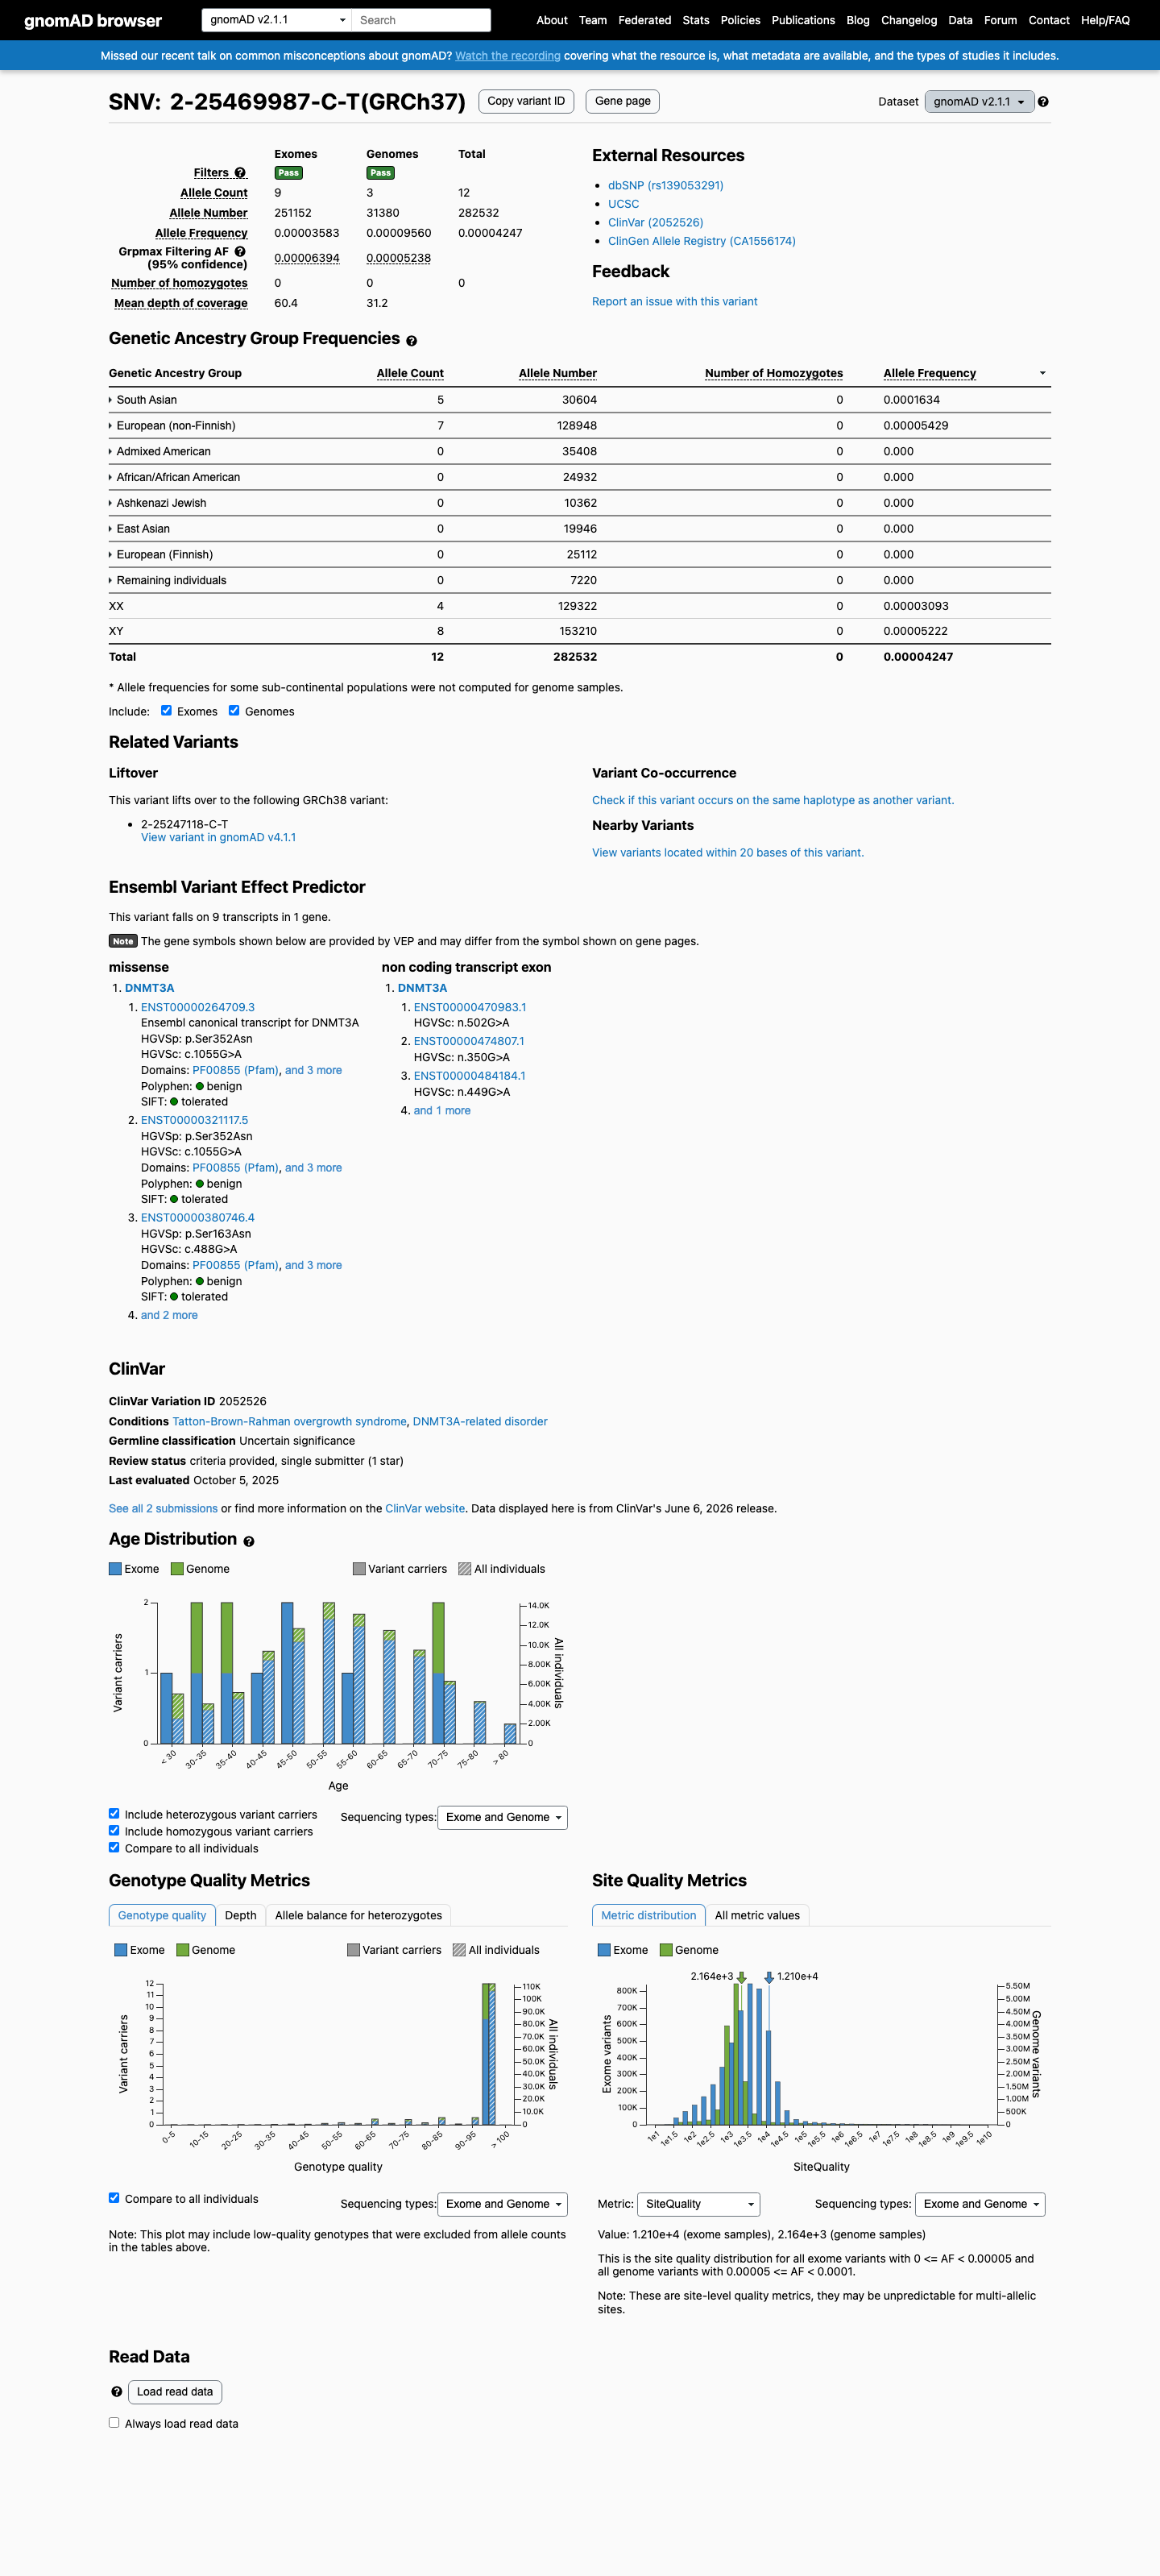
PVS1 does not apply because p.Ser352Asn is a missense substitution rather than a null variant (nonsense, frameshift, or canonical splice site).1 The variant is extremely rare in population databases (gnomAD v2.1 AF 0.00425% and v4.1 AF 0.00675%, no homozygotes), supporting PM2 at supporting strength.2 Computational predictors are concordant for a benign effect (REVEL 0.098, BayesDel -0.52, SpliceAI max delta 0.29 below the high-confidence splice threshold), supporting BP4; PP3 is not met.3 The variant has been observed as a somatic DNMT3A mutation in a therapy-related/secondary AML patient (PMID:21993668) and is curated as Likely Neutral by OncoKB; the somatic observation does not meet germline PS4, and no variant-specific functional data are available (PS3 not met; BS3 not met because no well-established functional studies exist).4 ClinVar classifies the variant as Uncertain significance from two laboratories (1-star, single submitter), so PS5, PP5, and BP6 are not met.5 No de novo, segregation, case-control, or phenotype-specific evidence is available, and no same-codon pathogenic comparator was identified, so PS2, PM6, PM5, PP1, and PP4 are not met.6 Population allele frequencies are far below the BA1 (1%) and BS1 (0.3%) thresholds, so BA1 and BS1 are not met.7 With only PM2 (supporting) and BP4 (supporting) met, no pathogenic or benign combination is reached under the generic ACMG/AMP 2015 rules, consistent with a classification of Uncertain Significance.8
Final classification
VUS
PM2BP4
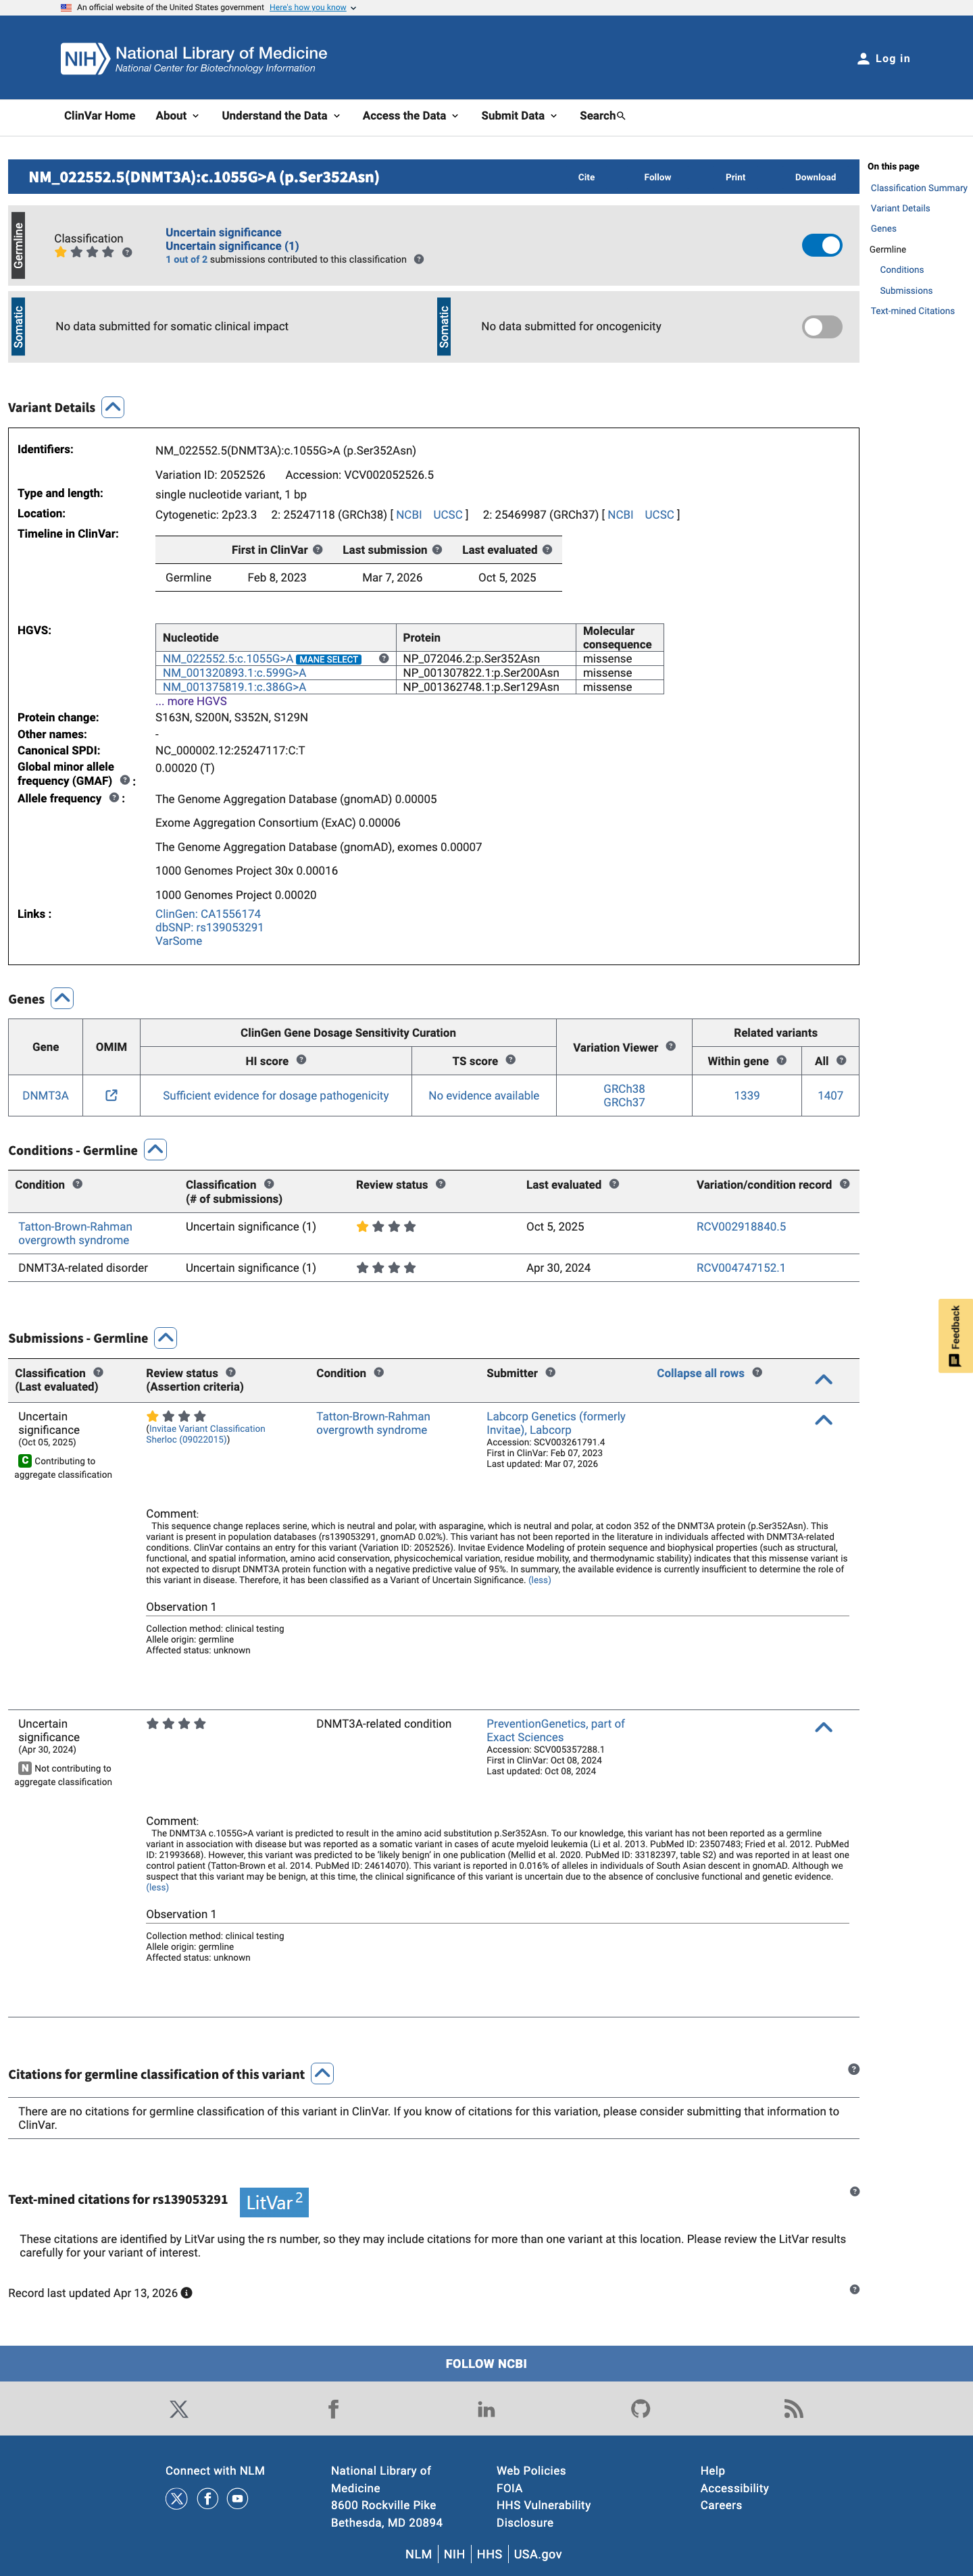
DNMT3A
c.1055G>A
p.Ser352Asn
missense
This variant
PVS1 does not apply because p.Ser352Asn is a missense substitution rather than a null variant (nonsense, frameshift, or canonical splice site).
gene-specific framework lacked a usable explicit final combination framework, so generic ACMG/AMP 2015 final-combination rules were applied as fallback; applied criteria: PM2 supporting, BP4 supporting; combination = 1 supporting + 1 supporting benign, which maps to VUS.
Classification rationale
PM2
BP4
VUS
DNMT3A c.1055G>A
missense
PM2 + BP4
→
VUS
1
pvs1_generic_framework ↗pvs1_variant_assessment
3
revelbayesdelspliceai ↗
6
pm5_candidates
8
generic_acmg_combination_rules
LYFE Sciences is an AI system, and it can make mistakes. Criteria
may be applied incorrectly, sources may be misread, and a confident-looking
classification can still be wrong. Double-check every criterion and
its underlying evidence before relying on any call.
Gene diagram
· NM_022552.4 · variants mapped to exon structure
DNMT3A
NM_022552.4
Fetching transcript structure from UCSC…
Applied criteria · 2 applied · 21 assessed
MetEvidence satisfies this criterion.
Not metEvaluated against available evidence; threshold not reached.
Not assessedApplies in principle, but no evidence was found to evaluate it.
N/ADoesn't apply to this variant type.
Applied · 2
Strength
Supporting
Moderate
Strong
Very strong
PM2
supporting
Pathogenic
The variant is extremely rare in population databases: gnomAD v2.1 AF 0.00425% (12/282,532 alleles, 0 homozygotes, grpmax FAF 6.39e-05) and gnomAD v4.1 AF 0.00675% (109/1,614,124 alleles, 0 homozygotes, grpmax FAF 6.81e-05), both well below the 0.1% PM2 threshold.
gnomAD v2.1: AF 0.00425%12/282532 alleles
BP4
supporting
Benign
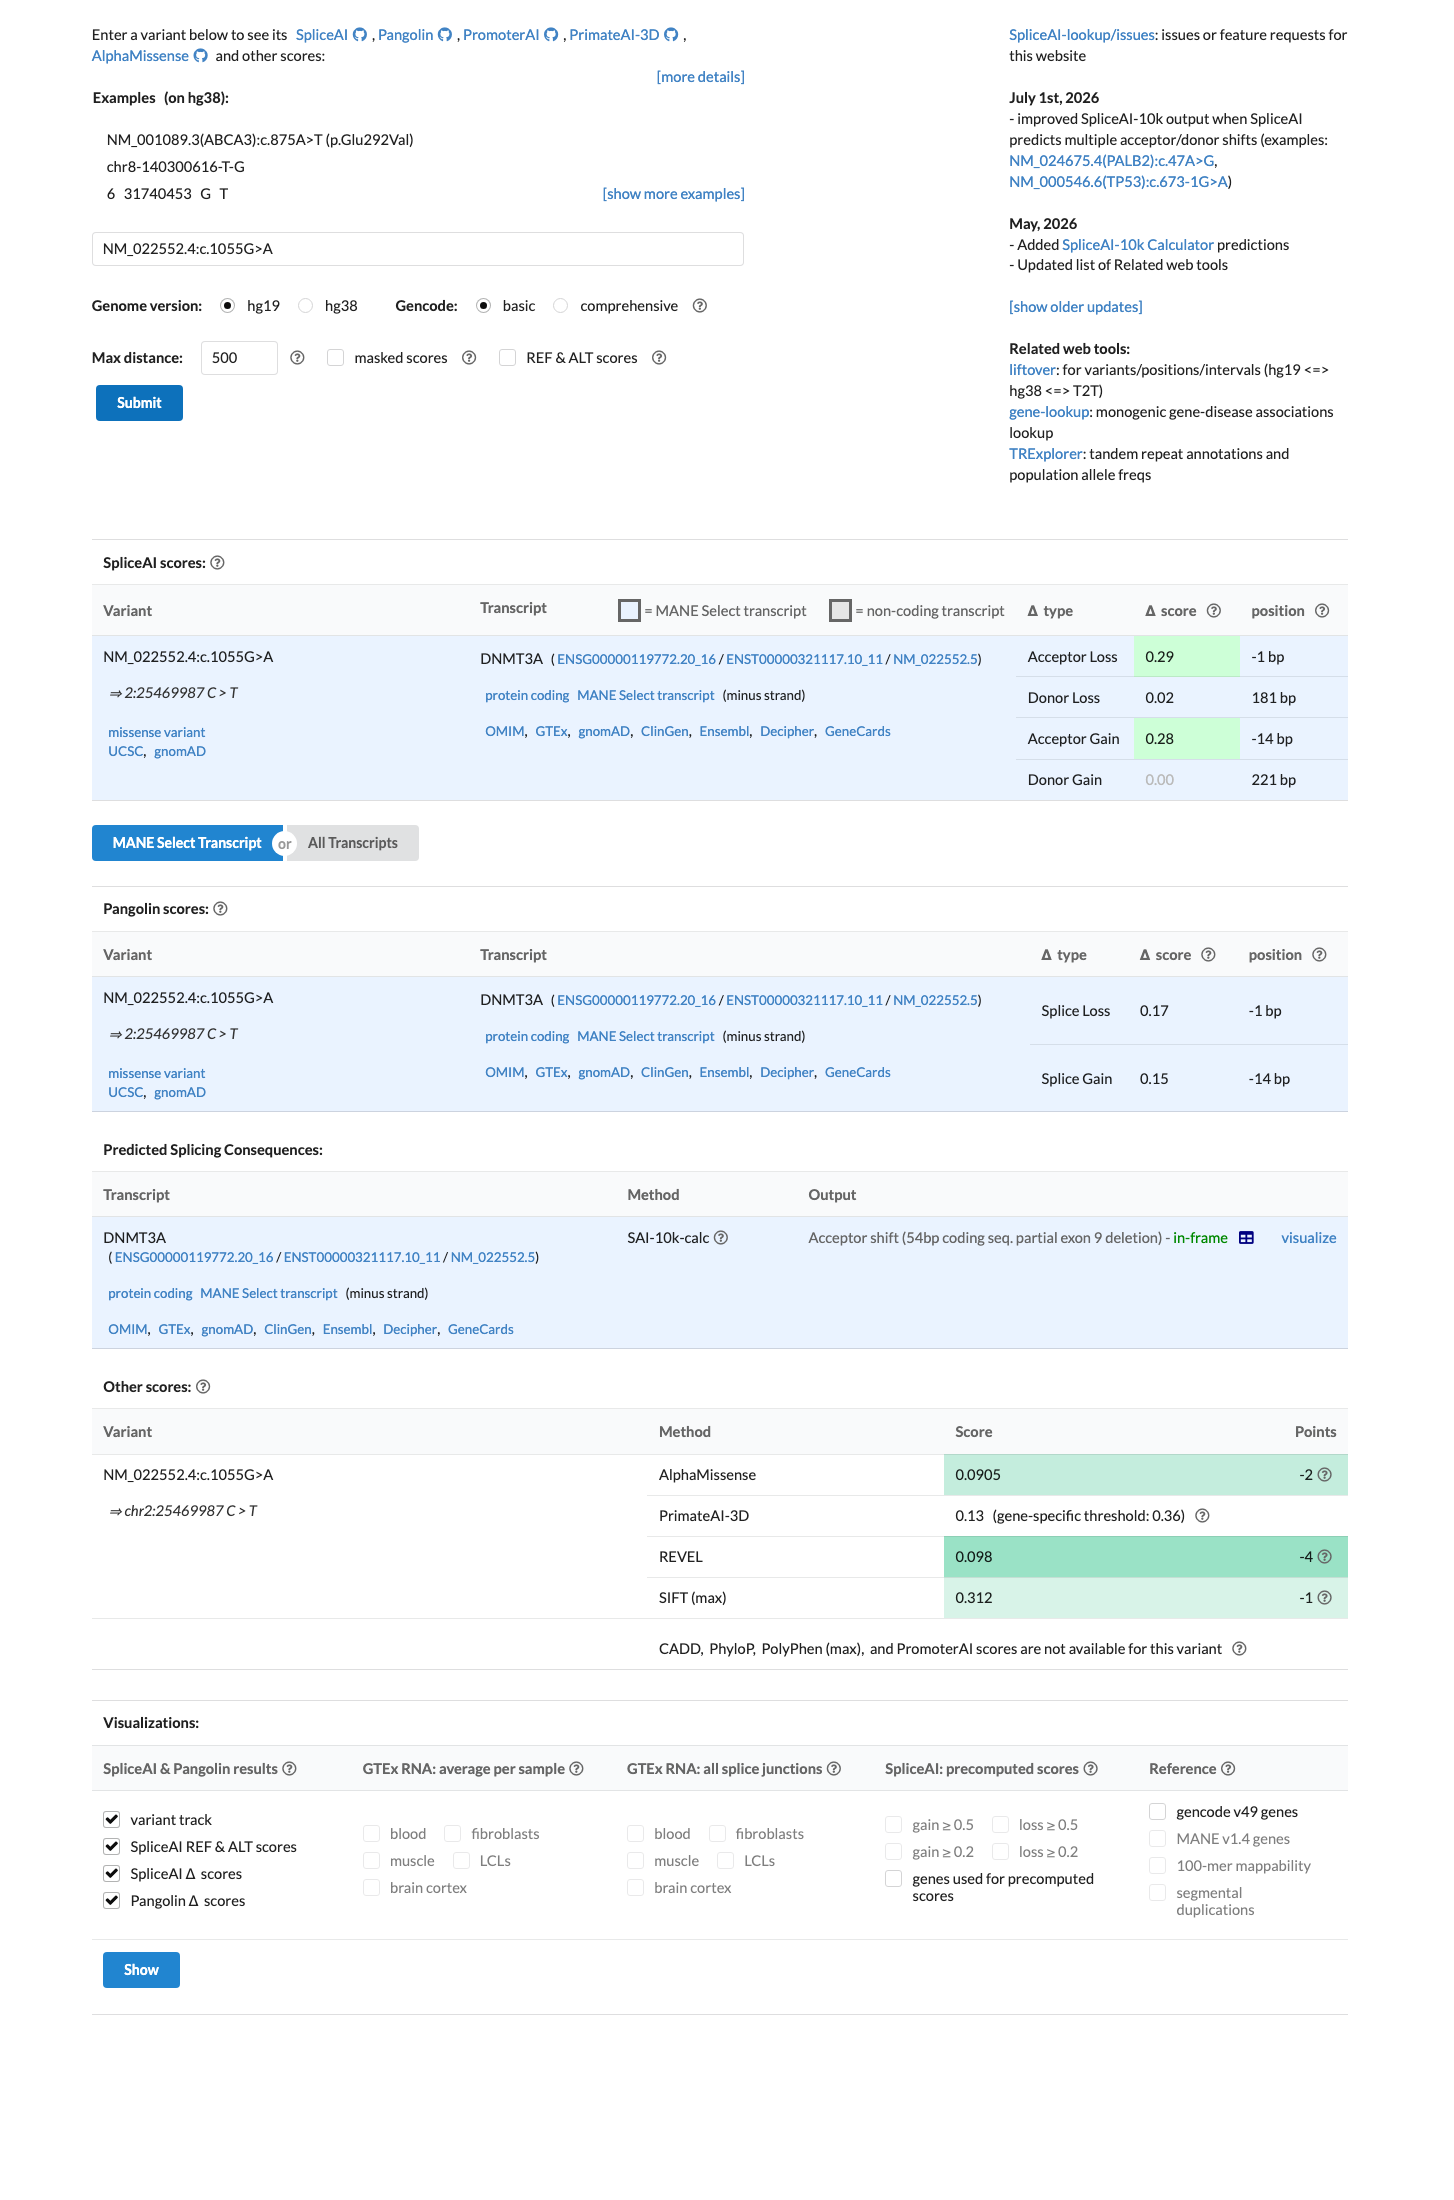
Multiple computational predictors support no impact on protein function or splicing: REVEL 0.098 (well below 0.5), BayesDel -0.5207 (negative, benign-leaning), and SpliceAI max delta 0.29 (below the 0.5 high-confidence splice-altering threshold).
REVEL 0.098 - predicted benign.BayesDel -0.5207 - predicted benign.SpliceAI max delta 0.29 (DS_AL 0.29
Assessed · not applied
· 21 not met · 0 not assessed
Pathogenic
PS1
No pathogenic or likely pathogenic variant producing the same amino acid change (p.Ser352Asn) via a different nucleotide substitution was identified in ClinVar or the reviewed literature.
PS2
No de novo occurrence of p.Ser352Asn with confirmed or assumed parentage was reported in the available evidence.
PS3
No variant-specific functional data exist for p.Ser352Asn.
PS4
No evidence of increased variant prevalence in affected individuals versus controls for germline disease.
PM1
Residue Ser352 lies within the ADD (ATRX-DNMT3A-DNMT3L) domain of DNMT3A (approximately residues 280-430), a well-characterized functional domain; however, p.Ser352Asn is not a statistically significant mutational hotspot, OncoKB curates the substitution as Likely Neutral, and no variant-specific evidence demonstrates disruption of ADD-domain function, so domain-level PM1 is not met.
PM5
No pathogenic or likely pathogenic missense variant at the same codon (Ser352) with a different amino acid substitution was identified; the automated PM5 candidate search returned no comparators, and the S352D change observed in one somatic AML case (PMID:21993668) is not a germline pathogenic classification.
PM6
No de novo observation, with or without confirmed parentage, was reported for p.Ser352Asn.
PP1
No cosegregation data in multiple affected family members are available for p.Ser352Asn.
PP2
Missense variants are a known mechanism of DNMT3A-related Tatton-Brown-Rahman syndrome, but no gene-specific missense constraint metric (e.g., gnomAD missense Z-score) or VCEP-defined PP2 threshold is available in the case materials to formally apply PP2.
PP3
In silico predictors are concordant for a benign effect - REVEL 0.098 (well below 0.5), BayesDel -0.5207 (negative, benign-leaning), and SpliceAI max delta 0.29 (below the 0.5 high-confidence splice-altering threshold, variant deep in exon 9) - so no computational evidence supports a deleterious effect.
PP4
No proband phenotype data are available to establish a phenotype highly specific for DNMT3A-related disease.
PP5
ClinVar classifies p.Ser352Asn as Uncertain significance (2 laboratories; criteria provided, single submitter - 1 star), which does not meet the 3-star expert-panel threshold required for PP5, and the TBRS GeneReviews article (PMID:35771960) provides no variant-specific information in the available materials.
Benign
BA1
The maximum allele frequency is 0.00675% (gnomAD v4.1), far below the 1% BA1 threshold.
BS1
The highest subpopulation allele frequency is 0.01634% (South Asian, gnomAD v2.1), far below the 0.3% BS1 threshold.
BS2
The variant is present at very low frequency in gnomAD with no homozygotes, and no age- or phenotype-stratified healthy-adult cohort data demonstrate observation at a frequency consistent with a fully penetrant benign allele.
BS3
No well-established functional studies demonstrate a lack of damaging effect for p.Ser352Asn.
BS4
No segregation data demonstrating absence of cosegregation with disease in affected families are available.
BP1
DNMT3A-related disease (Tatton-Brown-Rahman syndrome) is caused by both truncating and missense variants, so missense is a known disease mechanism and BP1 does not apply.
BP2
No observation of the variant in trans with a known pathogenic DNMT3A variant in an affected individual is available.
BP5
No alternate molecular basis of disease has been documented in a carrier of this variant.
BP6
ClinVar does not classify p.Ser352Asn as benign or likely benign by an expert panel (VUS, 1-star single submitter), so BP6 does not apply.
N/A · 5
PVS1 · PM3 · PM4 · BP3 · BP7
Research & evidence
Population frequency
gnomAD v4.1
gnomAD v2.1
v4.1
This variant is present in gnomAD v4.1 (AF= 6.75289e-05; MAF= 0.00675%, 109/1614124 alleles, homozygotes = 0) and has highest observed frequency in the European (non-Finnish) population (AF= 8.13563e-05; MAF= 0.00814%, 96/1179994 alleles, homozygotes = 0); grpmax FAF= 6.807e-05.
v2.1
This variant is present in gnomAD v2.1 (AF= 4.24731e-05; MAF= 0.00425%, 12/282532 alleles, homozygotes = 0) and has highest observed frequency in the South Asian population (AF= 0.000163377; MAF= 0.01634%, 5/30604 alleles, homozygotes = 0); grpmax FAF= 6.394e-05.
🇨🇦 CA
Not available in gnomAD-Canada v1.0.
Allele frequency by ancestry
three datasets · side by side
gnomAD v4.1
0.0068%
· 109 / 1,614,124
0 hom · FAF 0.0068%
0 hom · FAF 0.0068%
European (non-Finnish) 96 / 1,179,994 |
0.0081% |
South Asian 7 / 91,082 |
0.0077% |
Remaining individuals 3 / 62,510 |
0.0048% |
African/African American 3 / 75,022 |
0.004% |
+ 6 not observed (Admixed American, European (Finnish), Amish, East Asian, Middle Eastern, Ashkenazi Jewish)
gnomAD v2.1
0.0042%
· 12 / 282,532
0 hom · FAF 0.0064%
0 hom · FAF 0.0064%
South Asian 5 / 30,604 |
0.016% |
European (non-Finnish) 7 / 128,948 |
0.0054% |
+ 6 not observed (African/African American, Admixed American, Ashkenazi Jewish, East Asian, European (Finnish), Remaining individuals)
gnomAD Canada 🇨🇦
Absent
· 0 / ?
0 hom
0 hom
Not observed in any ancestry group.
ClinVar
This variant has been reported in ClinVar as Uncertain significance (2 clinical laboratories). (ClinVarID = 2052526)
In silico
SpliceAI predicts possible splice impact for this variant (max delta score = 0.29). REVEL score = 0.098. BayesDel score = -0.520724.
Functional
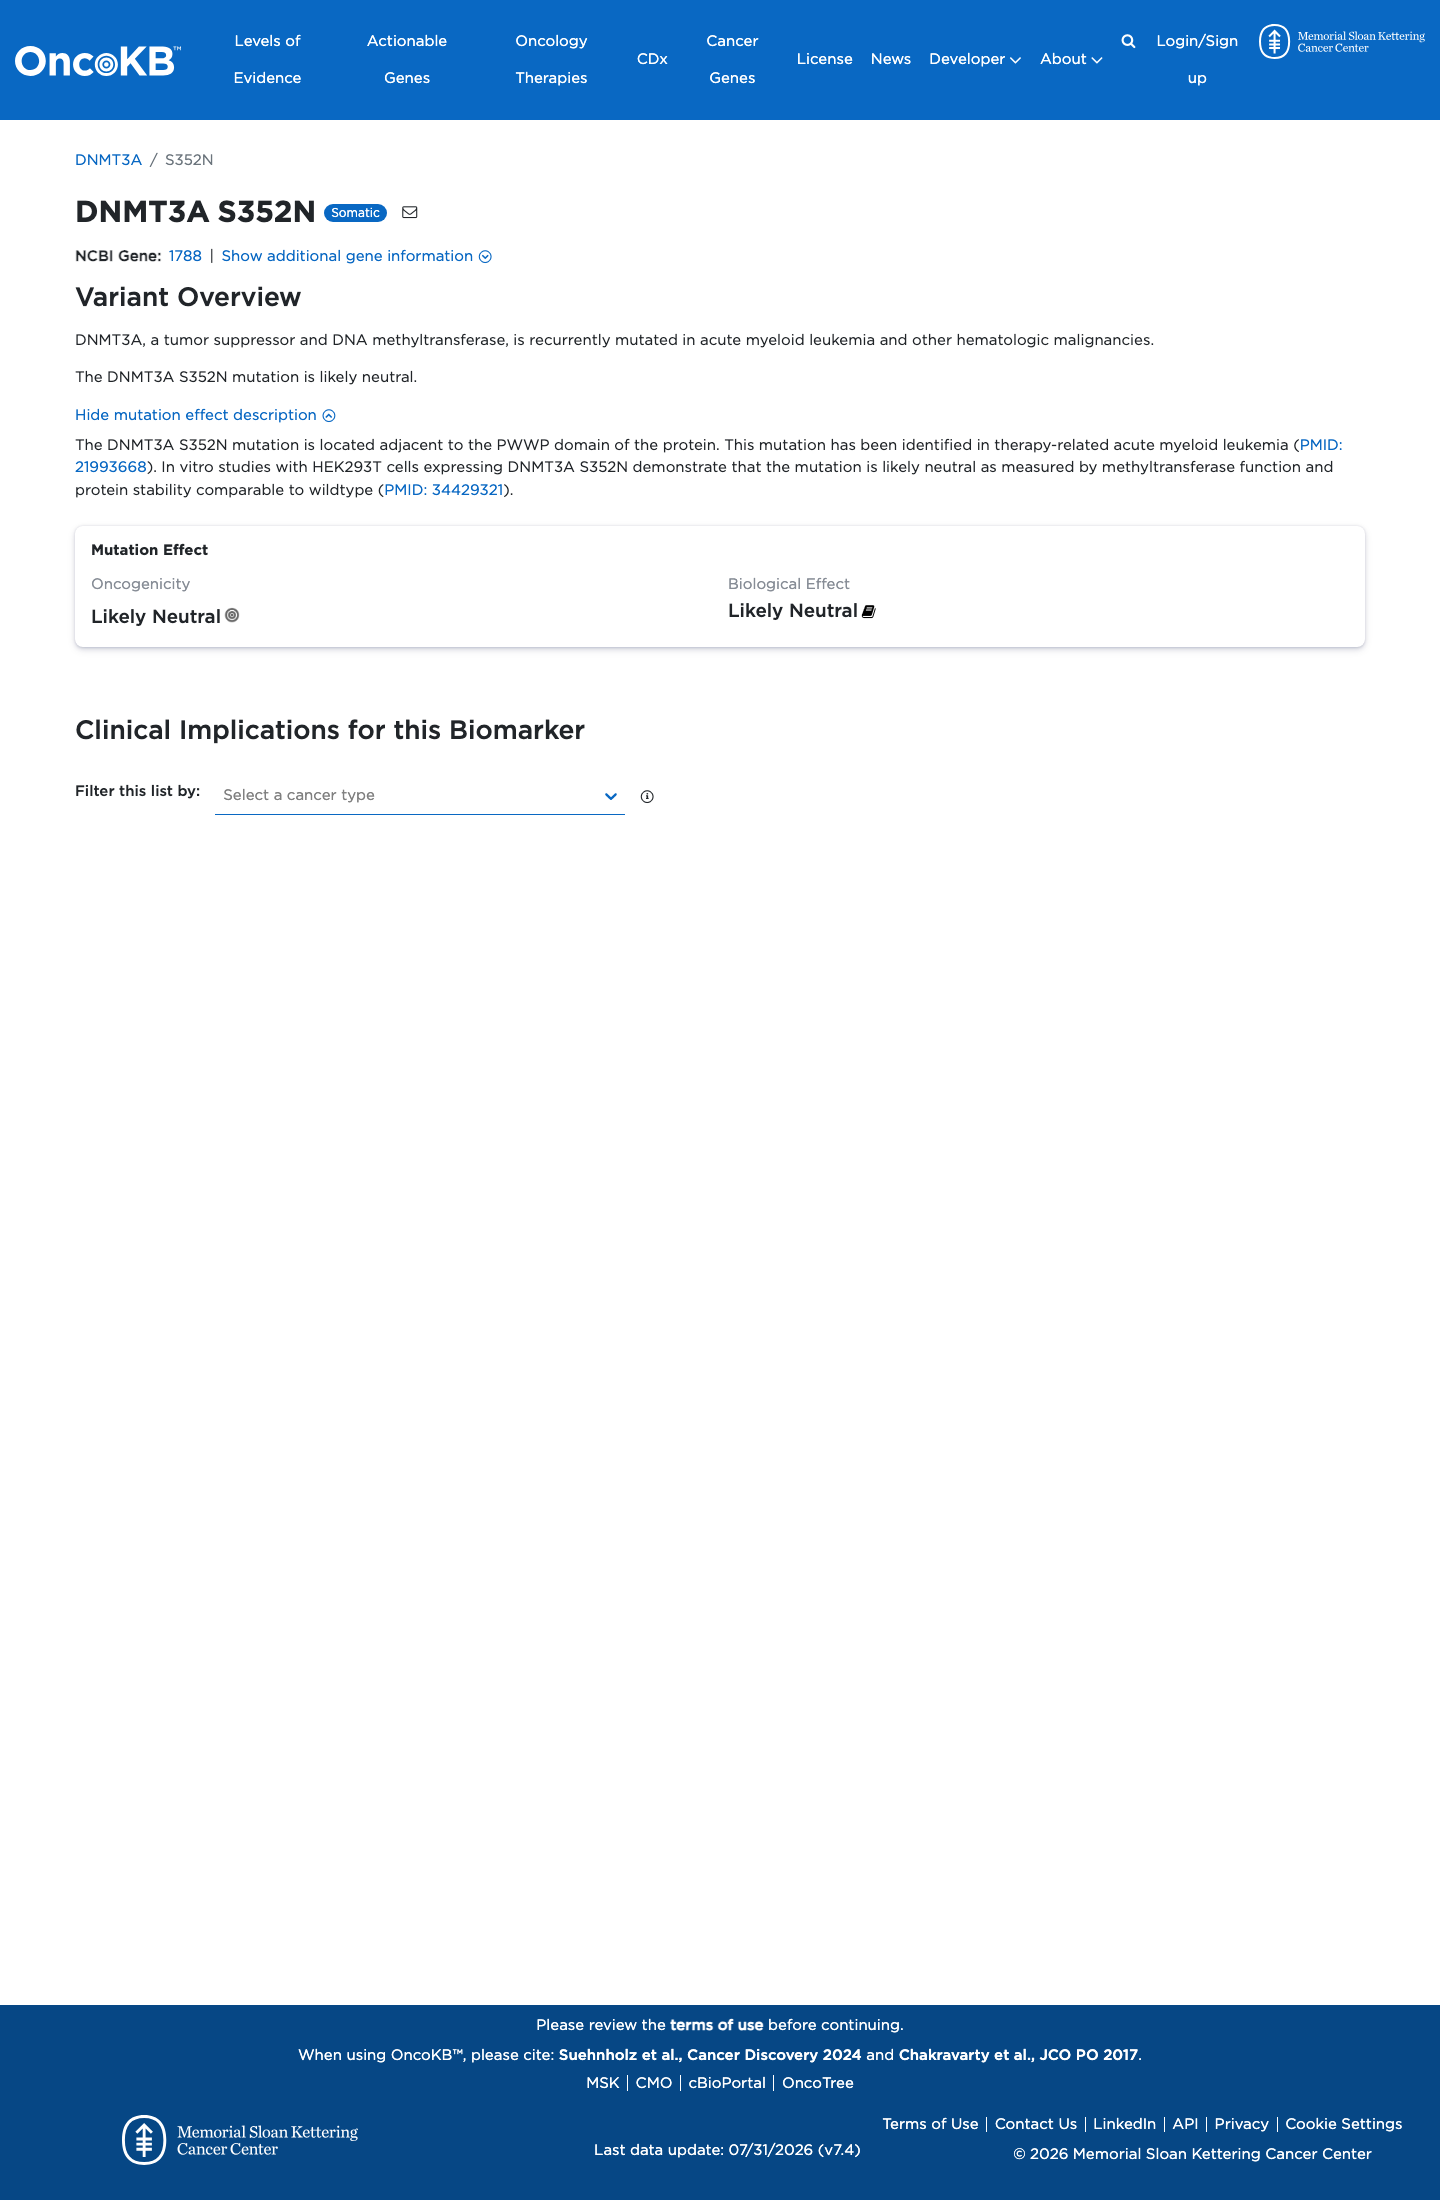
Likely Neutral
OncoKB identified variant-specific curated literature and context relevant to functional review; biological-effect context: Likely Neutral; curated oncogenicity label: Likely Neutral.
COSMIC
Cancer hotspots
Somatic evidence
Not in COSMIC / hotspots
COSMIC
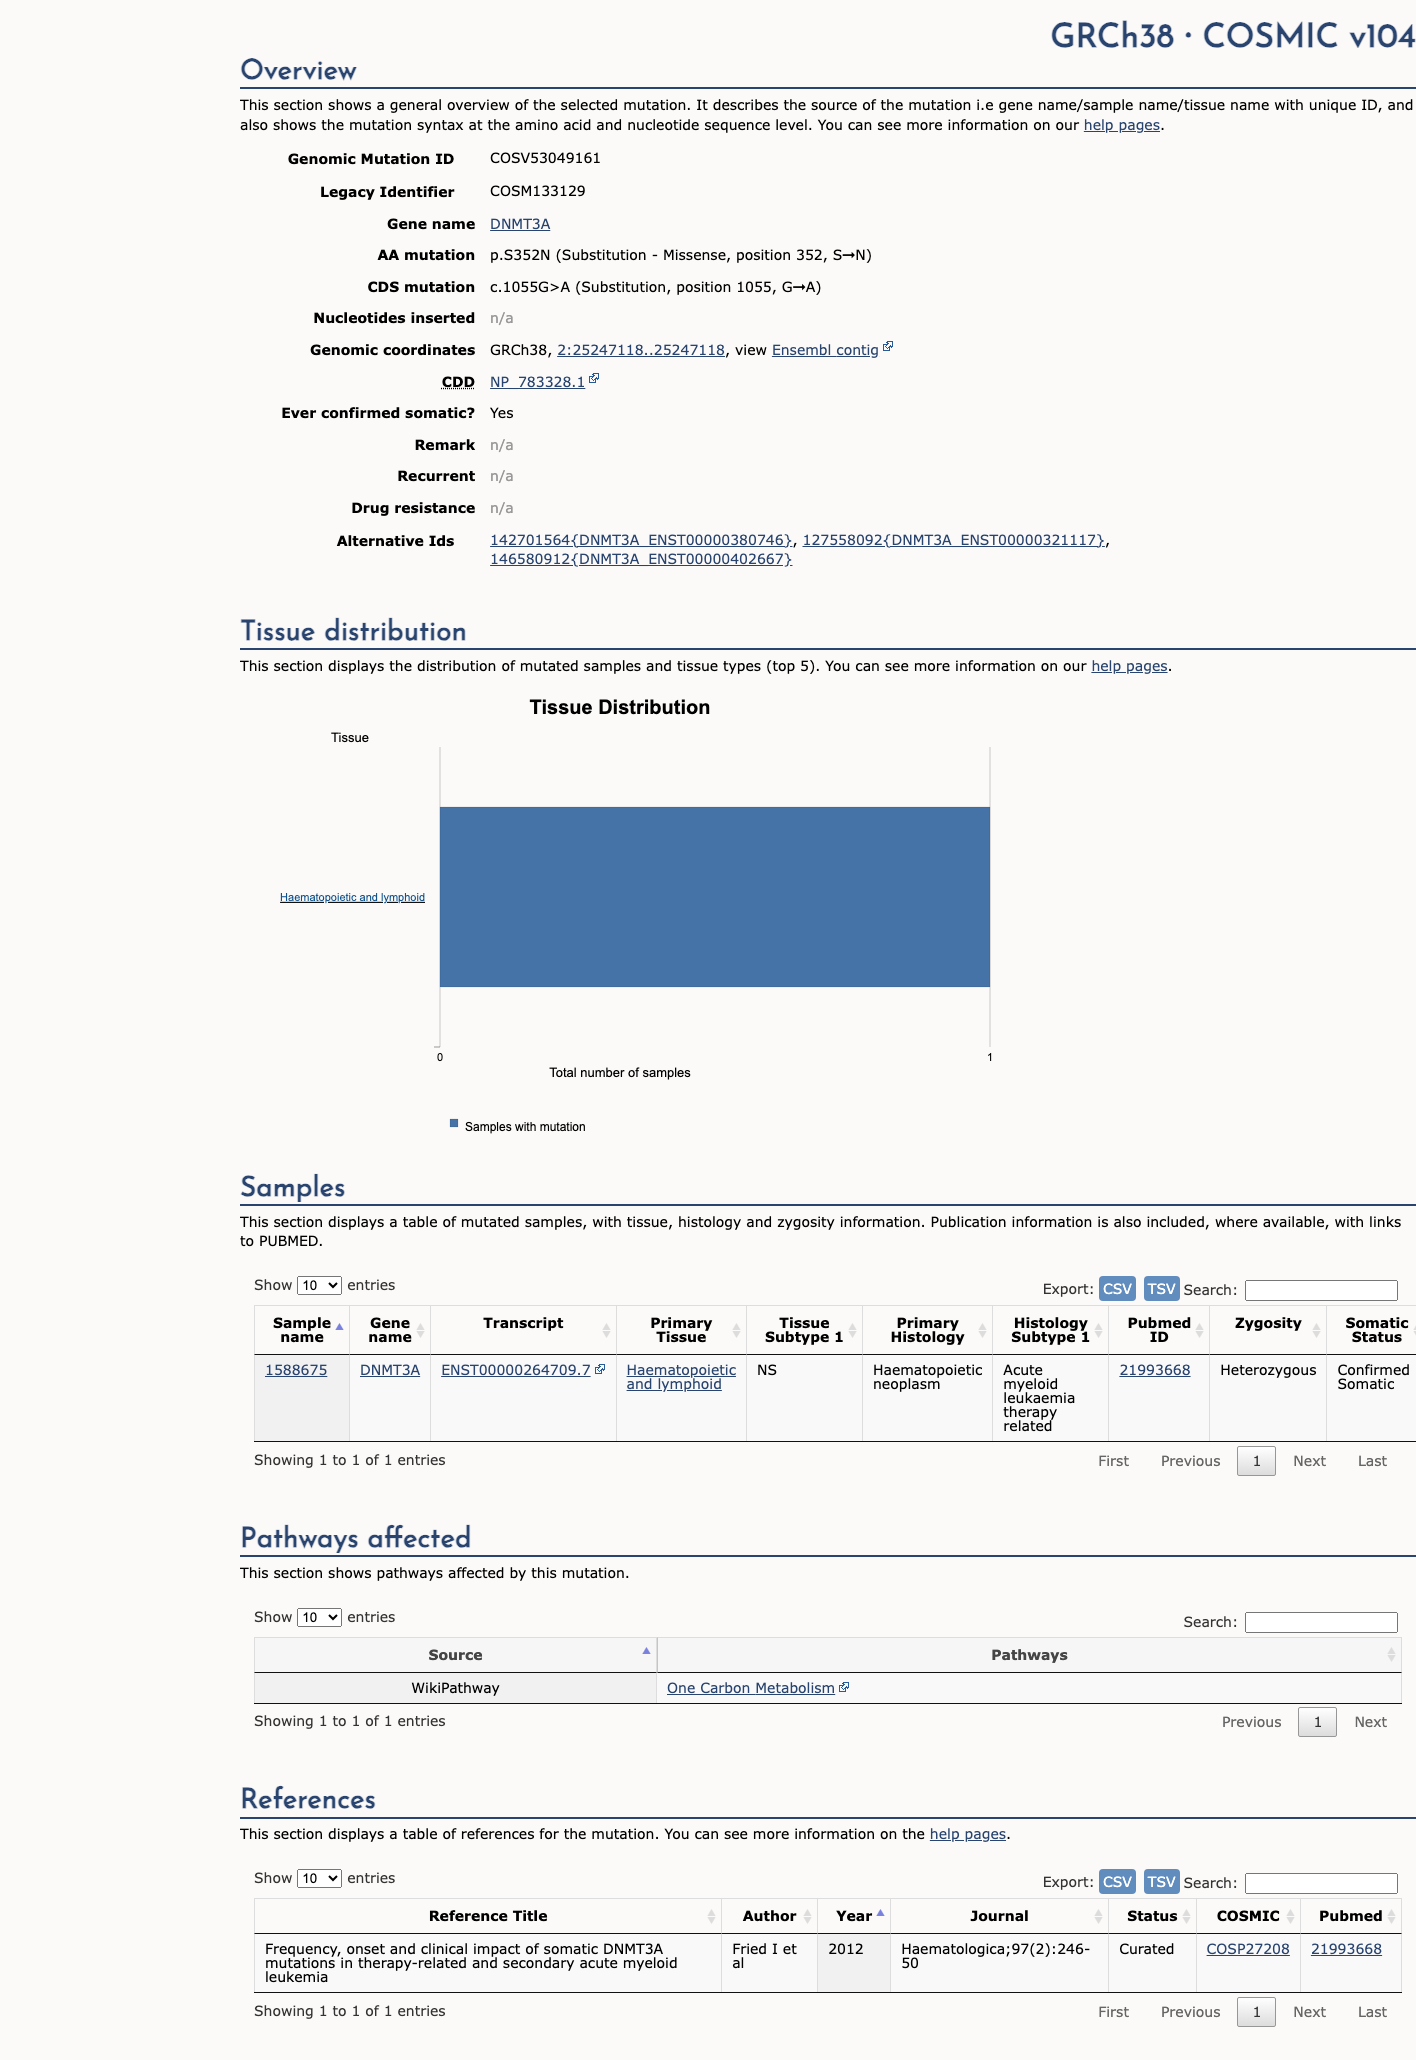
This variant does not lie in a statistically significant hotspot. This variant has previously been reported in somatic cancers (COSMIC; COSV53049161, n = 1 times).
Hotspots
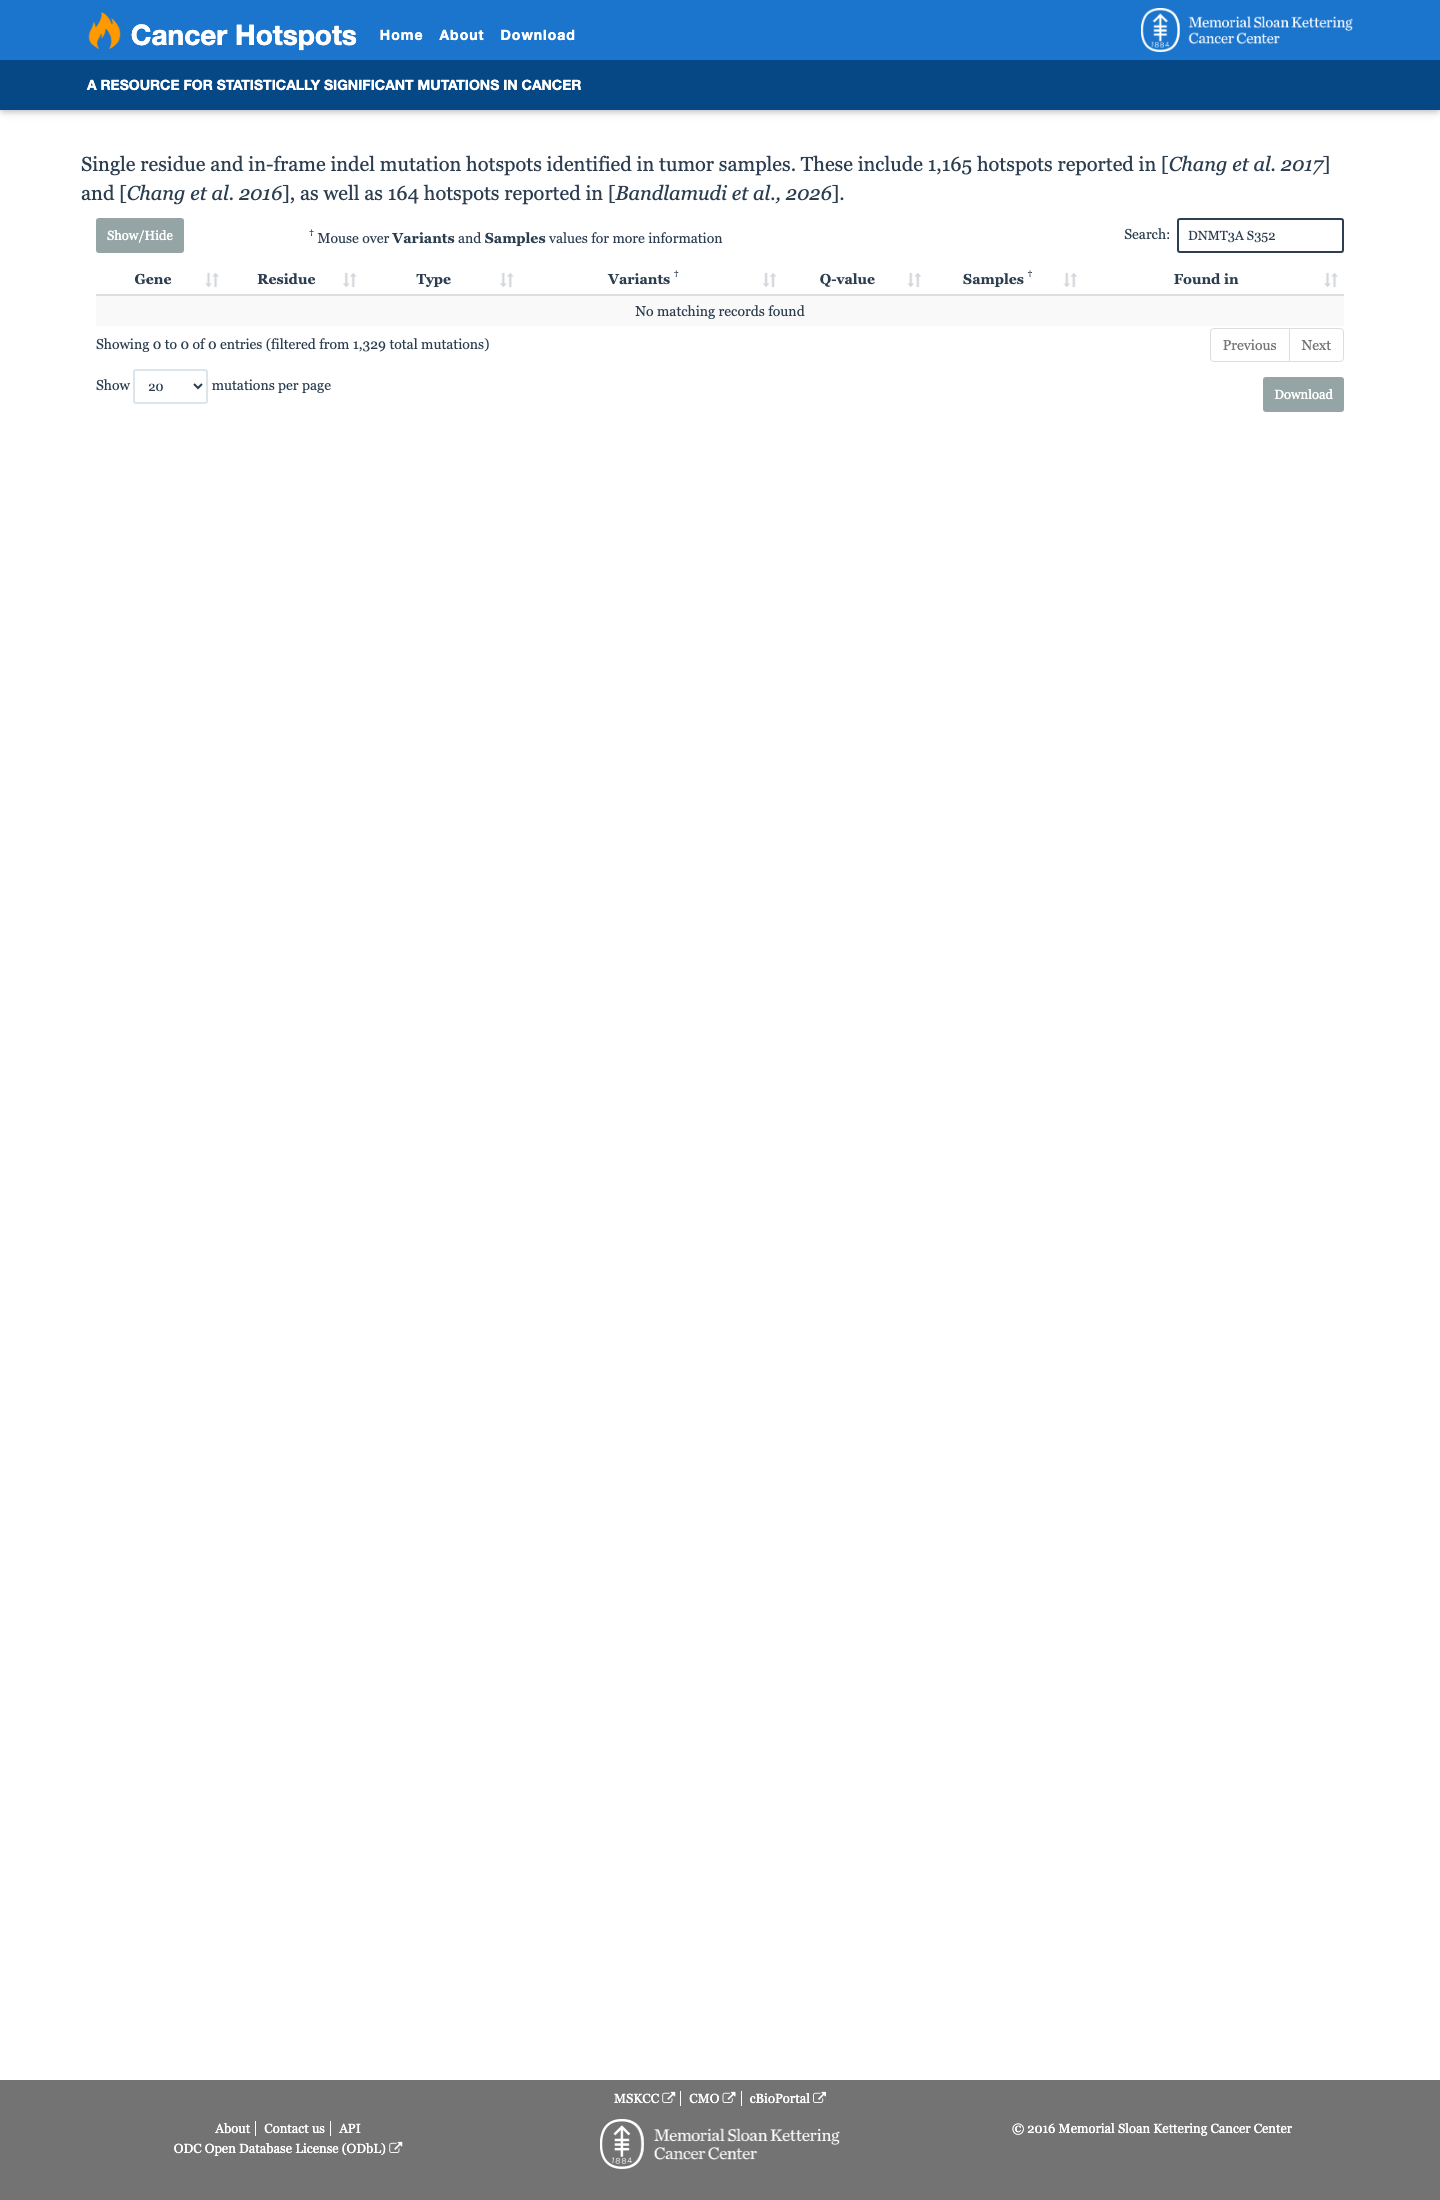
This variant does not lie in a statistically significant hotspot.
Sources & reference links
Triaged references · 3 PMIDs not cited in assessment
21993668 ↗
Frequency, onset and clinical impact of somatic DNMT3A mutations in therapy-related and secondary acute myeloid leukemia.
ONCOKB
34429321 ↗
Systematic Profiling of DNMT3A Variants Reveals Protein Instability Mediated by the DCAF8 E3 Ubiquitin Ligase Adaptor.
ONCOKB